

Validation of the vessel-specific leads (VSLs) for detection of acute ischemia on a dataset with non-ischemic
John J Wang1, Olle Pahlm2, Galen S Wagner3
1Philips Healthcare, Andover, MA, USA.

Insights
New vessel-specific lead (VSL) criteria improve the detection of acute ischemia and specificity for non-ischemic ST deviation compared to existing ST-elevation myocardial infarction (STEMI) criteria.
Area of Science:
- Cardiology
- Medical Diagnostics
- Electrocardiography
Background:
- Existing ST-elevation myocardial infarction (STEMI) criteria (ACC/ESC) show high specificity but low sensitivity for acute ischemia detection via 12-lead ECG.
- Previous studies indicated improved sensitivity (SE) for acute ischemia detection using ST deviation in 3 optimal vessel-specific leads (VSLs) without compromising specificity (SP).
Purpose of the Study:
- To validate the performance of VSL criteria in identifying non-ischemic ST-segment changes.
- To compare the specificity of VSL criteria against existing STEMI criteria in a diverse patient cohort.
Main Methods:
- Evaluated 100 patient ECGs from Skåne University Hospital, representing subgroups with ventricular preexcitation, pericarditis, early repolarization syndrome (ERS), left ventricular hypertrophy (LVH), and left bundle branch block (LBBB).
- Tested both standard STEMI criteria and VSL criteria (with and without an augmented LVH-specific lead).
- Calculated specificity (SP) for each subgroup and overall for performance comparison.
Main Results:
- VSL criteria demonstrated significantly higher overall SP (83%) compared to STEMI criteria (57%) (p<0.001).
- Specific subgroup SP for VSLs varied: 92% (preexcitation), 88% (pericarditis), 100% (ERS), 77% (LVH), 68% (LBBB).
- An augmented LVH-specific lead improved VSL SP to 96% in the LVH subgroup and overall SP to 88%.
Conclusions:
- VSL criteria offer superior specificity for non-ischemic ST deviation compared to current STEMI criteria.
- The VSL method shows promise for more accurate ECG interpretation in differentiating acute ischemia from other cardiac conditions.
- Further validation in larger populations with typical emergency room AMI prevalence is warranted.
Background:
Existing criteria recommended by ACC/ESC for identifying patients with ST elevation myocardial infarction (STEMI) from the 12-lead ECG perform with high specificity (SP) but low sensitivity (SE). In our previous studies, we found that the SE of acute ischemia detection can be markedly improved without any loss of SP by calculating, from the 12-lead ECG, ST deviation in 3 "optimal" vessel-specific leads (VSLs). To further validate the method, we evaluated the SP performance using a dataset with non-ischemic ST-segment changes.
Methods:
12-lead ECGs of 100 patients (75 males/25 females, age range 12-83years, average age 52years) were retrieved from a centralized ECG management system at Skåne University Hospital, Lund, Sweden. These ECGs were chosen to represent five subgroups with various causes of pathological ST deviation, other than acute coronary occlusion: a) ventricular preexcitation (n=12), b) acute pericarditis (n=26), c) early repolarization syndrome (ERS) (n=14), d) left ventricular hypertrophy (LVH) with "strain" (n=26), and e) left bundle branch block (LBBB) (n=22). ECGs with inadequate signal quality, heart rate exceeding 120bpm and/or atrial flutter were not selected for this study population. Both STEMI criteria and VSLs criteria with and without a new augmented LVH-specific derived lead were tested. SP, calculated for each subgroup and combined, was used as the performance measure for comparison.
Results:
SP test results for the STEMI criteria vs. the VSLs method without the augmented LVH lead were 100% vs. 92%, 4% vs. 88%, 29% vs. 100%, 100% vs. 77%, and 64% vs. 68% for the five subgroups with preexcitation, pericarditis, ERS, LVH, and LBBB, respectively. For the whole group, SP was 57% for the STEMI criteria and 83% for the VSLs criteria; this improvement was statistically significant (p<0.001). With the augmented LVH lead, SP for the VSLs improved from 77% to 96% for the LVH subgroup and SP for the other subgroups remained unchanged. For the whole study group, SP improved from 83% to 88%.
Conclusion:
Based on these results, we conclude that the VSLs criteria are not only more sensitive in detecting acute ischemia but also more specific in recognizing patients with non-ischemic ST deviation than the existing STEMI criteria. This finding needs to be further corroborated on a larger patient population with AMI prevalence typical of the population presenting to the emergency room.


Related Concept Videos
 01:19
Acute Coronary Syndrome II: Pathophysiology and Clinical Manifestations
 01:30
Acute Coronary Syndrome III: Diagnostic Studies
 01:30
Acute Coronary Syndrome I: Introduction
 01:28
Electrocardiogram Fundamentals
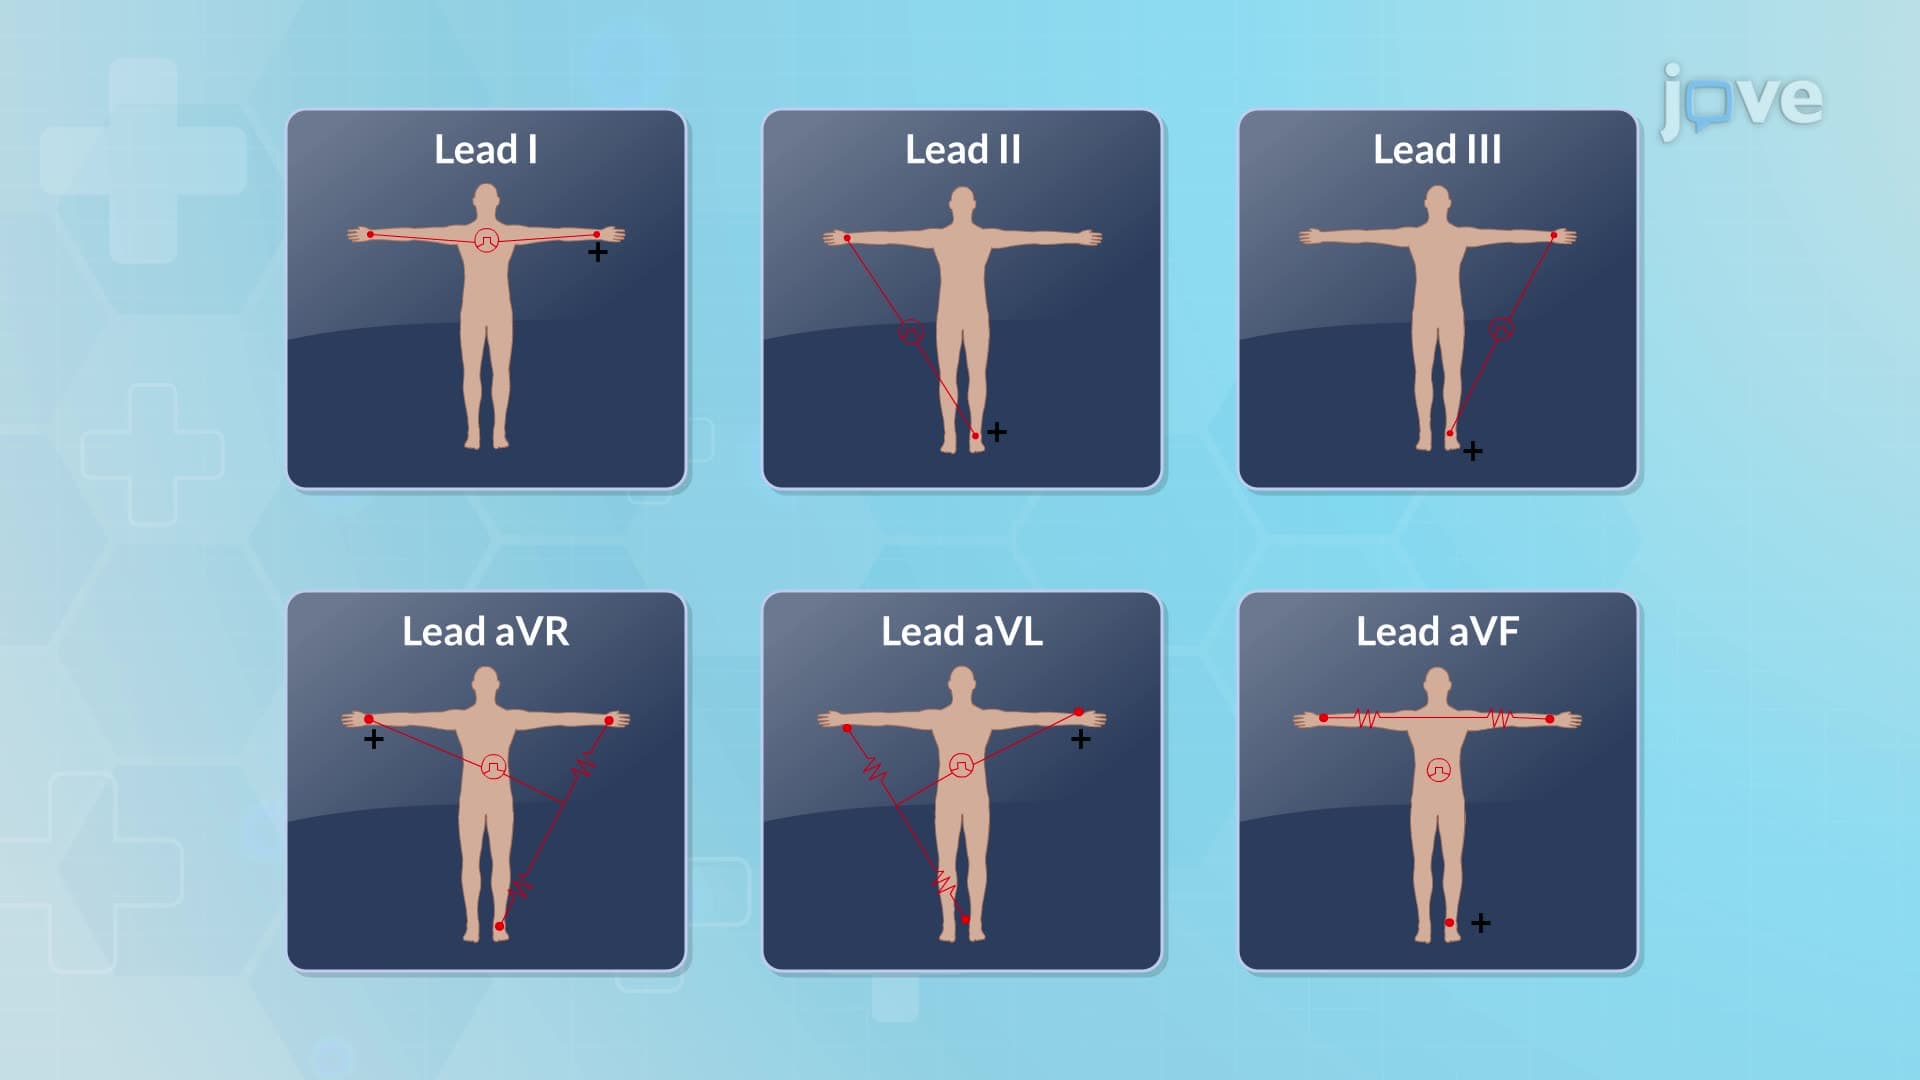
An electrocardiogram (ECG) is a diagnostic tool for identifying cardiac conditions such as arrhythmias, conduction abnormalities, and myocardial ischemia.
Definition
An electrocardiogram (ECG) visualizes the heart's electrical activity by tracing the electrical movement associated with each heartbeat on a graph or monitor. As the heart beats, an electrical wave passes through it, correlating with the cardiac cycle events.
Parts of an ECG
An ECG utilizes electrodes on the skin...