Related Experiment Video
Updated: Mar 14, 2026
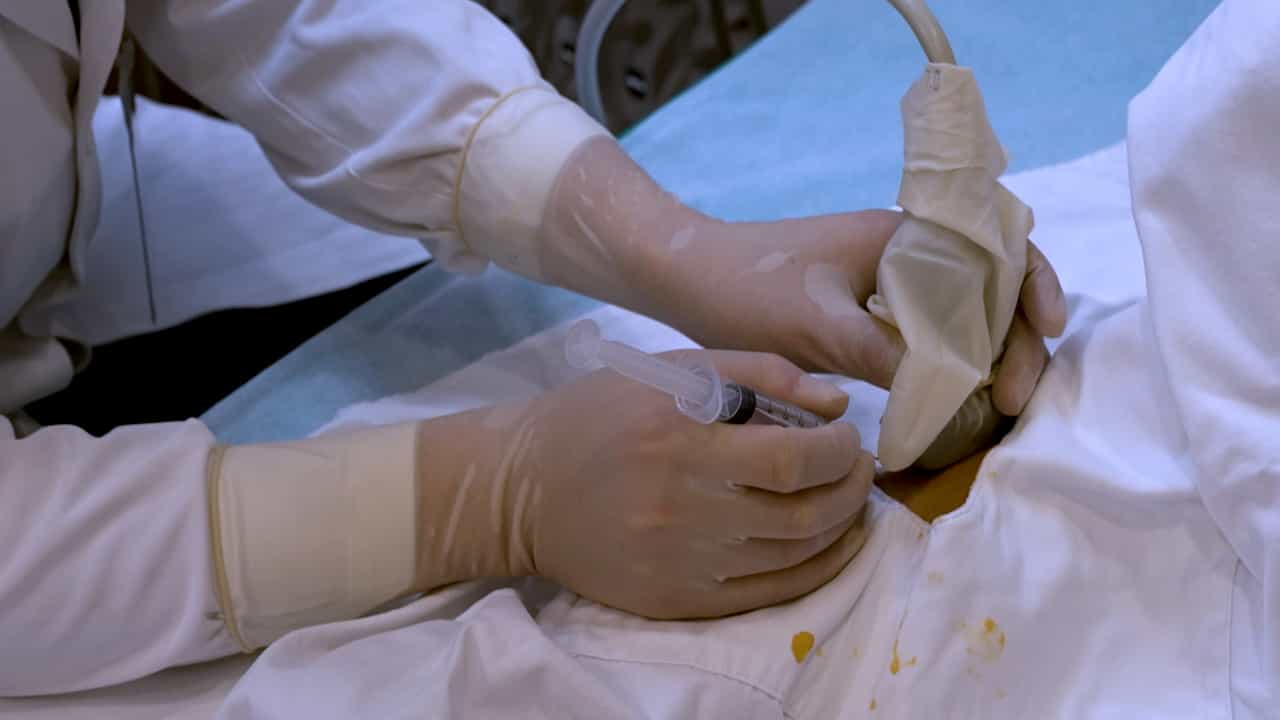

Author Spotlight: Ultrasound-Guided Needle Release Combined with Corticosteroid Injection for the Treatment of Supinator Syndrome
Published on: May 26, 2023
Posterior interosseous neuropathy: Supinator syndrome vs fascicular radial neuropathy
Philipp Bäumer1, Henrich Kele2, Annie Xia2
1From the Departments of Neuroradiology (P.B., A.X., D.S., M.B., M.P.) and Neurology (M.W.), Heidelberg University Hospital; Department of Radiology (P.B.), German Cancer Research Center, Heidelberg; and Center for Peripheral Neurology (H.K.), Hamburg, Germany; and the Department of Neuroradiology, University Clinic Würzburg. p.baeumer@dkfz-heidelberg.de.

Objective:
To investigate the spatial pattern of lesion dispersion in posterior interosseous neuropathy syndrome (PINS) by high-resolution magnetic resonance neurography.
Methods:
This prospective study was approved by the local ethics committee and written informed consent was obtained from all patients. In 19 patients with PINS and 20 healthy controls, a standardized magnetic resonance neurography protocol at 3-tesla was performed with coverage of the upper arm and elbow (T2-weighted fat-saturated: echo time/repetition time 52/7,020 milliseconds, in-plane resolution 0.27 × 0.27 mm2). Lesion classification of the radial nerve trunk and its deep branch (which becomes the posterior interosseous nerve) was performed by visual rating and additional quantitative analysis of normalized T2 signal of radial nerve voxels.
Results:
Of 19 patients with PINS, only 3 (16%) had a focal neuropathy at the entry of the radial nerve deep branch into the supinator muscle at elbow/forearm level. The other 16 (84%) had proximal radial nerve lesions at the upper arm level with a predominant lesion focus 8.3 ± 4.6 cm proximal to the humeroradial joint. Most of these lesions (75%) followed a specific somatotopic pattern, involving only those fascicles that would form the posterior interosseous nerve more distally.
Conclusions:
PINS is not necessarily caused by focal compression at the supinator muscle but is instead frequently a consequence of partial fascicular lesions of the radial nerve trunk at the upper arm level. Neuroimaging should be considered as a complementary diagnostic method in PINS.
More Related Videos
 10:36
Vascularized Composite Hand Allograft Procurement and Preparation for Distal and Proximal Forearm Allotransplantation: A Stepwise Approach
Published on: May 23, 2025
 06:40
Screening of Axonal Degeneration in Carpal Tunnel Syndrome Using Ultrasonography and Nerve Conduction Studies
Published on: January 11, 2019
Related Concept Videos
 01:22
Spinal Nerves: Plexus I
The Cervical Plexus
The cervical plexus, formed by the anterior rami of the first four...
 01:16
Muscles that Move the Forearm
Forearm Flexors
The biceps brachii, brachialis, and brachioradialis are forearm flexors. The biceps brachii is made up of two heads. Its long head originates at the supraglenoid tubercle of the scapula, whereas that of the short head is...
 01:16
Muscles of the Forearm that Move the Hand and Fingers
Anterior Compartment
The anterior compartment muscles originate from the humerus. They primarily function as flexors and are also known as flexor muscles. They typically insert on the carpals, metacarpals, and phalanges. The superficial layer includes the flexor carpi...
 01:21
Peripheral Arterial Disease II: Clinical Manifestations and Diagnostic Evaluation
 01:09
Bones of the Upper Limb: Radius
The radius has a nail-shaped head, and a...
 01:11
Assessment of radial pulse
The radial pulse, located at the wrist, is often the preferred site for assessing peripheral pulse because of its accessibility and dependability. The process of determining the radial pulse involves several steps: