Related Experiment Video
Updated: Mar 12, 2026
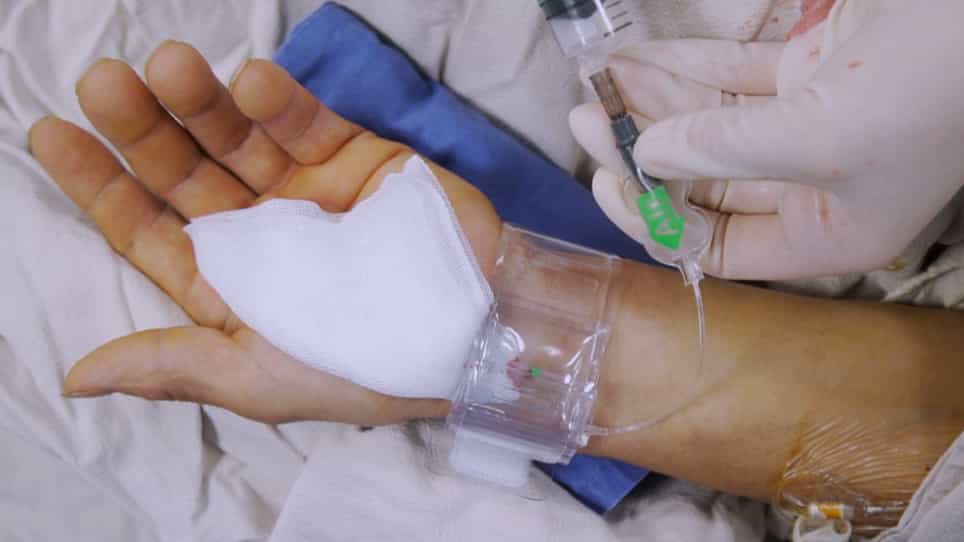
Transradial Access Chemoembolization for Hepatocellular Carcinoma Patients
Published on: September 20, 2020
Comparison of radial, brachial, and femoral accesses using hemostatic devices for percutaneous coronary intervention
Masaya Otsuka1, Nobuo Shiode2, Yasuhisa Nakao2
1Department of Cardiology, Hiroshima City Hiroshima Citizens Hospital, 7-33 Moto-machi, Naka-ku, Hiroshima, 730-8518, Japan. Masaya.Otsuka@ma7.seikyou.ne.jp.

Some studies have suggested that radial access (RA) for percutaneous coronary intervention (PCI) reduces vascular complications and bleeding compared to femoral access (FA). The purpose of this study was to investigate the routine use of hemostatic devices and bleeding complications among RA, brachial access (BA), and FA. Between January 2015 and December 2015, 298 patients treated for PCI with RA were compared with 158 patients using BA and 206 patients using FA. The radial sheath was routinely removed with ADAPTY, the brachial sheath with BLEED SAFE, and the femoral sheath with Perclose ProGlide. In-hospital bleeding complications were investigated. Cardiogenic shock was most frequent in patients in the femoral group (RA 1.3%, BA 2.5%, FA 9.2%, p < 0.0001). The rate of major bleeding was highest in the femoral group (RA 1.0%, BA 2.5%, FA 5.3%, p = 0.01). Blood transfusion rates were highest in the femoral group (RA 0.7%, BA 1.3%, FA 4.4%, p = 0.01). Retroperitoneal bleeding was observed in 1.9% of patients in the femoral group. Patients in the brachial group had large hematomas (RA 0.7%, BA 4.4%, FA 1.5%, p = 0.01). Pseudoaneurysm formation needing intervention occurred most frequently in the brachial group (RA 0%, BA 1.3%, FA 0%, p = 0.04). In conclusion, compared to the brachial and femoral approaches, the radial approach appears to be the safest technique to avoid local vascular bleeding complications. The brachial approach has the highest risk of large hematoma and pseudoaneurysm formation among the three groups.
Some studies have suggested that radial access (RA) for percutaneous coronary intervention (PCI) reduces vascular complications and bleeding compared to femoral access (FA). The purpose of this study was to investigate the routine use of hemostatic devices and bleeding complications among RA, brachial access (BA), and FA. Between January 2015 and December 2015, 298 patients treated for PCI with RA were compared with 158 patients using BA and 206 patients using FA. The radial sheath was routinely removed with ADAPTY, the brachial sheath with BLEED SAFE, and the femoral sheath with Perclose ProGlide. In-hospital bleeding complications were investigated. Cardiogenic shock was most frequent in patients in the femoral group (RA 1.3%, BA 2.5%, FA 9.2%, p < 0.0001). The rate of major bleeding was highest in the femoral group (RA 1.0%, BA 2.5%, FA 5.3%, p = 0.01). Blood transfusion rates were highest in the femoral group (RA 0.7%, BA 1.3%, FA 4.4%, p = 0.01). Retroperitoneal bleeding was observed in 1.9% of patients in the femoral group. Patients in the brachial group had large hematomas (RA 0.7%, BA 4.4%, FA 1.5%, p = 0.01). Pseudoaneurysm formation needing intervention occurred most frequently in the brachial group (RA 0%, BA 1.3%, FA 0%, p = 0.04). In conclusion, compared to the brachial and femoral approaches, the radial approach appears to be the safest technique to avoid local vascular bleeding complications. The brachial approach has the highest risk of large hematoma and pseudoaneurysm formation among the three groups.

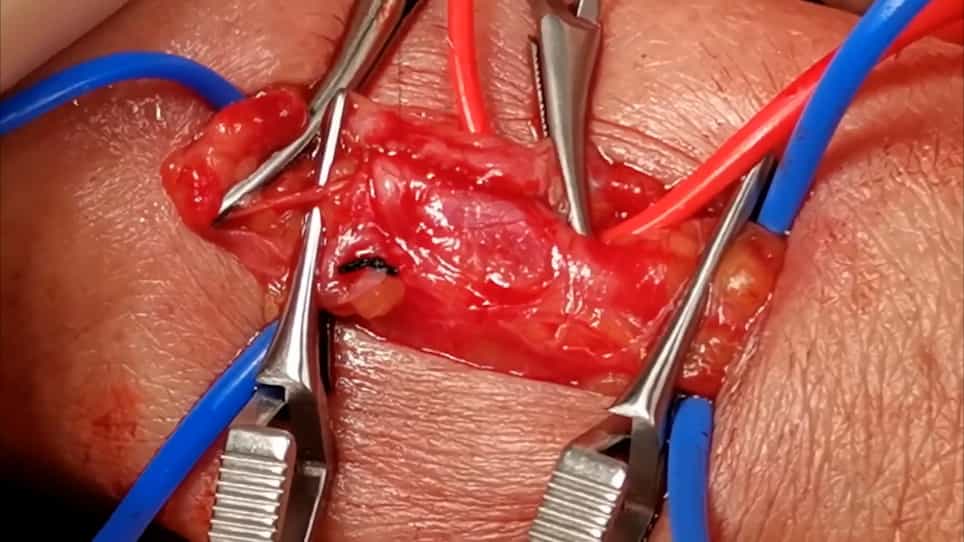
Related Concept Videos
 01:11
Assessment of radial pulse
The radial pulse, located at the wrist, is often the preferred site for assessing peripheral pulse because of its accessibility and dependability. The process of determining the radial pulse involves several steps:
 01:21
Sites for measuring blood pressure
The Brachial Artery: Primary Site for Blood Pressure Measurement
 01:21
Cardiac Catheterization II: Right Heart Catheterization
 01:25
Assessment of apical radial pulse
The A-R pulse assessment involves simultaneous evaluation of the apical and radial pulses. When the apical and radial pulse rates vary, this assessment helps identify a pulse deficit.
Pre-Procedural Preparation
 01:24
Cardiac Catheterization III: Left Heart Catheterization
 01:28
Cardiac Catheterization I: Pre-Procedure Overview