Related Experiment Video
Updated: Mar 12, 2026
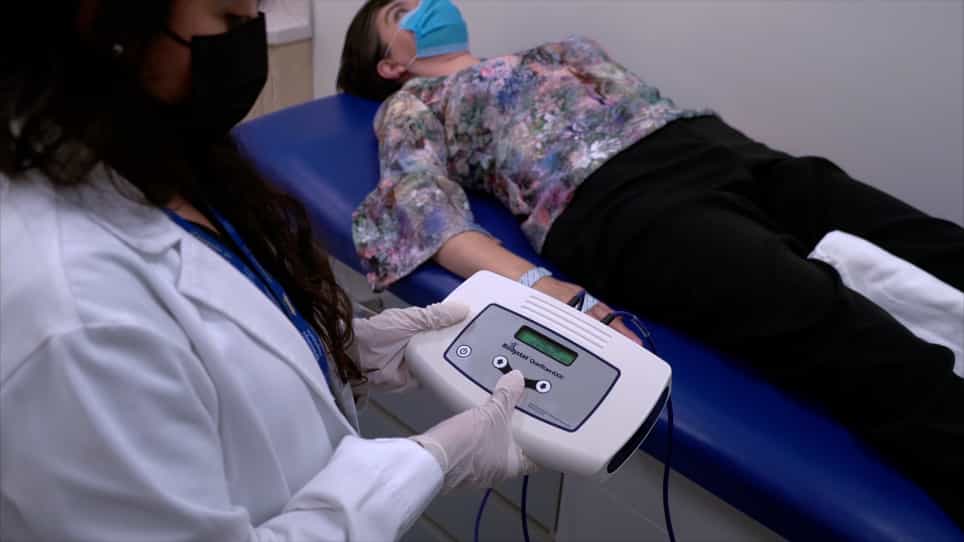

Evaluation of Fluid Overload by Bioelectrical Impedance Vectorial Analysis
Published on: August 17, 2022
Identification of volume overload hospitalizations among hemodialysis patients using administrative claims: a
Magdalene M Assimon1,2, Thuy Nguyen3, Suzanne L Katsanos1
1Division of Nephrology and Hypertension, Department of Medicine, University of North Carolina Kidney Center, UNC School of Medicine, 7024 Burnett-Womack CB #7155, Chapel Hill, NC, 27599-7155, USA.

Background:
High rates of volume overload hospitalizations may indicate inadequate dialysis facility fluid management. Administrative claims databases are often used to study such outcomes, but these data are generated for billing purposes and may not capture clinical nuance. It is unknown if volume overload admissions can be correctly identified in administrative data and if a single claims-based definition for volume overload can be used across epidemiologic surveillance studies, observational studies of exposure-outcome associations and quality assessments. We conducted a validation study to assess the accuracy of claims-based definitions for volume overload hospitalizations among hemodialysis patients.
Methods:
Data were taken from a random sample of 315 adult hemodialysis patients admitted to University of North Carolina Hospitals from January 2010 through June 2013. Standardized chart reviews were conducted to clinically adjudicate the presence or absence of volume overload at hospital admission. Claims-based definitions were constructed from varying combinations of fluid-related ICD-9 discharge diagnosis codes including fluid overload, pulmonary edema, pleural effusion, and heart failure. Using clinically adjudicated volume overload hospitalizations as the reference standard, validity metrics and their 95 % confidence intervals (CIs) were estimated for each definition.
Results:
Of the 315 hospital admissions, 77 (24.4 %) were clinically adjudicated as volume overload hospitalizations. The prevalence of claims-identified volume overload admissions varied across definitions, ranging from 1.6 to 37.1 %. When definitions were constructed with discharge diagnosis codes present in any billing position, volume overload hospitalizations defined by fluid overload, pleural effusion or heart failure diagnosis codes had the highest sensitivity, 81.8 % (95 % CI: 71.4 %, 89.7 %). Volume overload hospitalizations defined by pulmonary edema diagnosis codes had the highest specificity, 98.3 % (95 % CI: 95.8 %, 99.5 %). Definitions constructed with discharge diagnosis codes present in any billing position (versus the primary position) captured more false positive events.
Conclusions:
Prevalence and validity estimates of volume overload hospitalizations vary across claims-based definitions. A universal claims-based definition for volume overload hospitalizations may not apply to all clinical and research scenarios. Investigators and regulators need to consider the implications of misclassifying events when evaluating and monitoring hemodialysis patient volume overload admissions with administrative data. Claims-based definitions should be selected accordingly.
More Related Videos
Related Concept Videos
 01:24
Hemodialysis II: Procedure and Complications
 01:25
Hemodialysis III: Nursing Management
 01:25
Hemodialysis I: Introduction
 01:30
Continuous Renal Replacement Therapy
 01:25
Peritoneal Dialysis II: Peritoneal Dialysis Systems and Complications
 01:22
Heart Failure Drugs: Diuretics