Related Experiment Video
Updated: Mar 12, 2026


Scanning Skeletal Remains for Bone Mineral Density in Forensic Contexts
Published on: January 29, 2018
Diverging results of areal and volumetric bone mineral density in Down syndrome
M García-Hoyos1, M T García-Unzueta1, D de Luis2
1Department of Internal Medicine, University Hospital Marqués de Valdecilla, University of Cantabria, RETICEF, IDIVAL, Santander, Spain.

Abstract:
Population with Down syndrome (DS) has lower areal BMD, in association with their smaller skeletal size. However, volumetric BMD and other indices of bone microarchitecture, such as trabecular bone score (TBS) and calcaneal ultrasound (QUS), were normal.
Introduction:
Patients with DS have a number of risk factors that could predispose them to osteoporosis. Several studies reported that people with DS also have lower areal bone mineral density, but differences in the skeletal size could bias the analysis.
Methods:
Seventy-five patients with DS and 76 controls without intellectual disability were recruited. Controls were matched for age and sex. Bone mineral density (BMD) was measure by Dual-energy X-ray Absorptiometry (DXA), and volumetric bone mineral density (vBMD) was calculated by published formulas. Body composition was also measured by DXA. Microarchitecture was measured by TBS and QUS. Serum 25-hidroxyvitamin D (25OHD), parathyroid hormone (PTH), aminoterminal propeptide of type collagen (P1NP), and C-terminal telopeptide of type I collagen (CTX) were also determined. Physical activity was assessed by the International Physical Activity Questionnaires (IPAQ-short form). To evaluate nutritional intake, we recorded three consecutive days of food.
Results:
DS individuals had lower height (151 ± 11 vs. 169 ± 9 cm). BMD was higher in the controls (lumbar spine (LS) 0.903 ± 0.124 g/cm2 in patients and 0.997 ± 0.115 g/cm2 in the controls; femoral neck (FN) 0.761 ± .126 g/cm2 and 0.838 ± 0.115 g/cm2, respectively). vBMD was similar in the DS group (LS 0.244 ± 0.124 g/cm3; FN 0.325 ± .0.073 g/cm3) and the controls (LS 0.255 ± 0.033 g/cm3; FN 0.309 ± 0.043 g/cm3). Microarchitecture measured by QUS was slightly better in DS, and TBS measures were similar in both groups. 25OHD, PTH, and CTX were similar in both groups. P1NP was higher in the DS group. Time spent on exercise was similar in both groups, but intensity was higher in the control group. Population with DS has correct nutrition.
Conclusions:
Areal BMD is reduced in DS, but it seems to be related to the smaller body and skeletal size. In fact, the estimated volumetric BMD is similar in patients with DS and in control individuals. Furthermore, people with DS have normal bone microarchitecture.
More Related Videos
 07:12
Semiautomated Longitudinal Microcomputed Tomography-based Quantitative Structural Analysis of a Nude Rat Osteoporosis-related Vertebral Fracture Model
Published on: September 28, 2017
 09:02
Cortical Bone Assessment Using Ultrasonic Guided Waves: A Reproducibility Study in a Healthy Population
Published on: January 31, 2025
Related Concept Videos
 01:29
Bone Disorders
Bone deposition is also affected by the levels of sex hormones like estrogen and testosterone that promote osteoblast activity and bone matrix synthesis. When the level of these hormones decreases due to aging, it causes a reduction in bone deposition. As a result, bone resorption by osteoclasts...
 01:09
Changes in the Appendicular Skeleton with Age
Initially, the limb buds consist of a core of mesenchyme covered by a layer of ectoderm. The ectoderm at the end of the limb bud thickens to form a narrow crest called the apical ectodermal ridge. This ridge stimulates the underlying...
 01:09
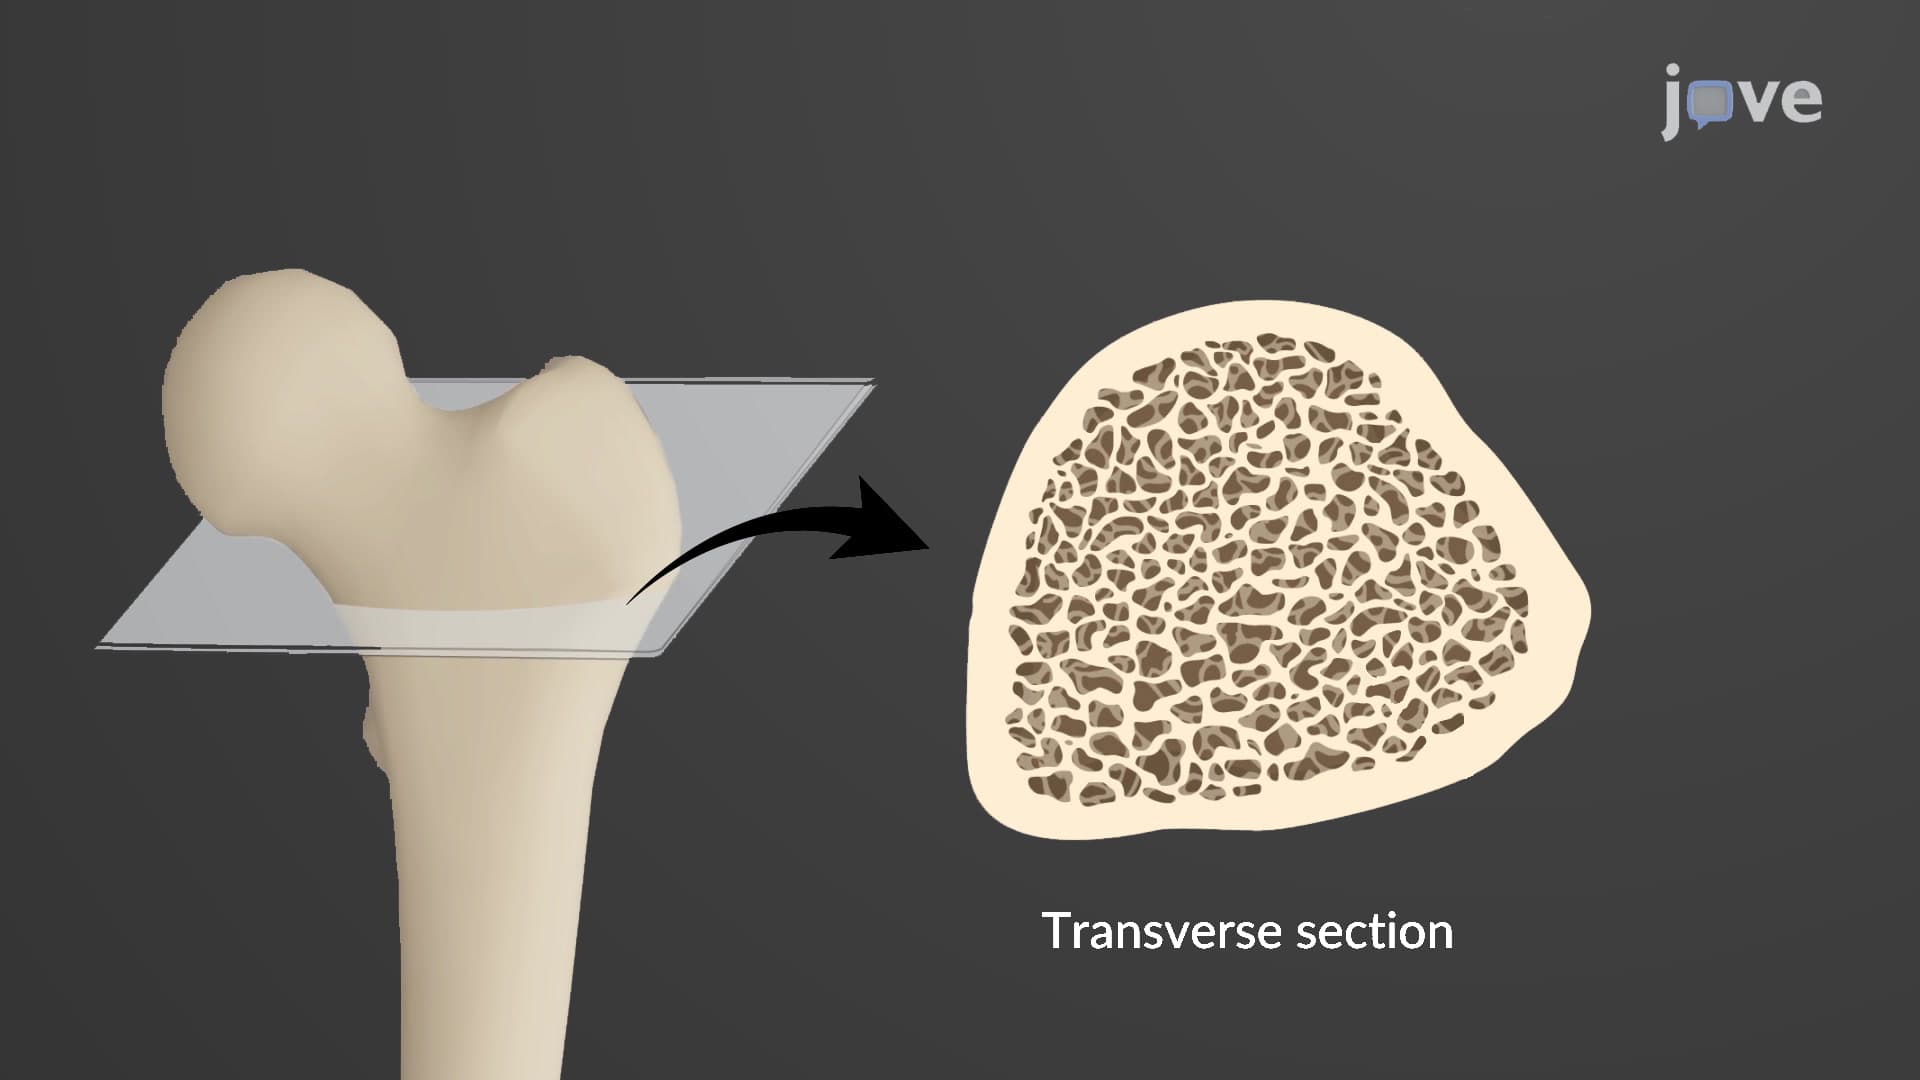
Spongy Bone
Spongy bone is more porous, and less dense compared to compact bone. It is composed of concentric lamellae that are arranged irregularly to form the trabecular network. In some bones, the spaces between trabeculae contain red marrow, where...