Related Experiment Video
Updated: Mar 11, 2026

A High-Fidelity Porcine Model of Orthotopic Heart Transplantation Following Donation after Circulatory Death
Published on: June 6, 2025
Pathophysiological Trends During Withdrawal of Life Support: Implications for Organ Donation After Circulatory Death
Arjun Iyer1, Hong Chee Chew, Ling Gao
11 The Victor Chang Cardiac Research Institute, Sydney, Australia. 2 Heart & Lung Transplant Unit, St Vincent's Hospital, Darlinghurst, Australia. 3 Department of Cardiothoracic Surgery, St Vincent's Hospital, Darlinghurst, Australia. 4 Department of Clinical Pharmacology, St Vincent's Hospital, Darlinghurst, Australia. 5 Department of Physiology and Pharmacology, University of New South Wales, Randwick, Australia. 6 Department of Cardiology, St Vincent's Hospital, Darlinghurst, Australia. 7 St. Vincent's Clinical School, Faculty of Medicine, University of New South Wales, Kensington, Australia. 8 School of Biotechnology and Biomolecular Science, Faculty of Science, University of New South Wales, Kensington, Australia.

Insights
Donation after circulatory death (DCD) heart viability is limited by rapid pathophysiological changes during withdrawal of life support (WLS). Understanding these events is crucial for improving DCD heart transplantation outcomes.
Area of Science:
- Cardiovascular Physiology
- Transplantation Medicine
- Organ Viability
Background:
- Donation after circulatory death (DCD) offers an alternative deceased organ source.
- DCD heart transplantation is emerging, but donor heart viability remains a concern.
- Understanding pathophysiological changes during withdrawal of life support (WLS) is key.
Purpose of the Study:
- To document cardiac and circulatory changes during WLS in a porcine model.
- To assess the time course of these detrimental events.
Main Methods:
- Utilized a porcine asphyxia model to simulate WLS.
- Monitored hemodynamic, volumetric, metabolic, biochemical, and endocrine parameters.
- Recorded times to circulatory arrest and electrical asystole.
Main Results:
- Rapid hypoxemia led to pulmonary hypertension and right ventricular distension.
- Systemic hypotension occurred with decreased left atrial pressure.
- Biochemical markers indicated myocardial injury and stress (lactate, troponin-T, potassium, catecholamines).
Conclusions:
- WLS rapidly induces damaging cardiac events, particularly in the right ventricle.
- These findings highlight a narrow window for interventions to preserve DCD heart viability.
- Informed strategies for improving DCD heart transplantation are needed.
Background:
Donation after circulatory death (DCD) provides an alternative pathway to deceased organ transplantation. Although clinical DCD lung, liver, and kidney transplantation are well established, transplantation of hearts retrieved from DCD donors has reached clinical translation only recently. Progress has been limited by concern regarding the viability of DCD hearts. The aim of this study was to document the pathophysiological changes that occur in the heart and circulation during withdrawal of life (WLS) support.
Methods:
In a porcine asphyxia model, we characterized the hemodynamic, volumetric, metabolic, biochemical, and endocrine changes after WLS for up to 40 minutes. Times to circulatory arrest and electrical asystole were recorded.
Results:
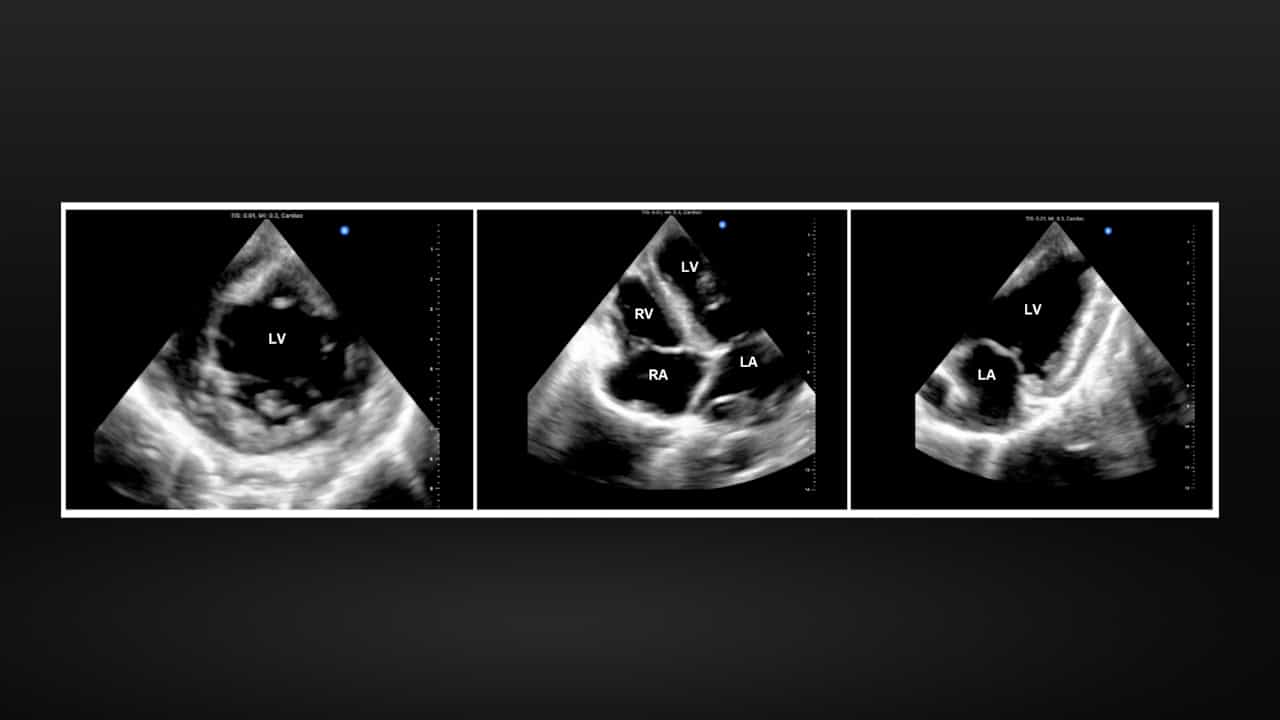
After WLS, there was rapid onset of profound hypoxemia resulting in acute pulmonary hypertension and right ventricular distension. Concurrently, progressive systemic hypotension occurred with a fall in left atrial pressure and little change in left ventricular volume. Mean times to circulatory arrest and electrical asystole were 8 ± 1 and 16 ± 2 minutes, respectively. Hemodynamic changes were accompanied by a rapid fall in pH, and rise in blood lactate, troponin-T, and potassium. Plasma noradrenaline and adrenaline levels rose rapidly with dramatic increases in coronary sinus levels indicative of myocardial release.
Conclusions:
These findings provide insight into the nature and tempo of the damaging events that occur in the heart and in particular the right ventricle during WLS, and give an indication of the limited timeframe for the implementation of potential postmortem interventions that could be applied to improve organ viability.

Related Concept Videos
 01:28
Kidney Transplant I: Introduction
 01:24
Tissue Transplantation
The Biology of Tissue Transplantation
The biology of tissue transplantation hinges on the Major Histocompatibility Complex (MHC) molecules. These molecules...