Related Experiment Video
Updated: Mar 11, 2026
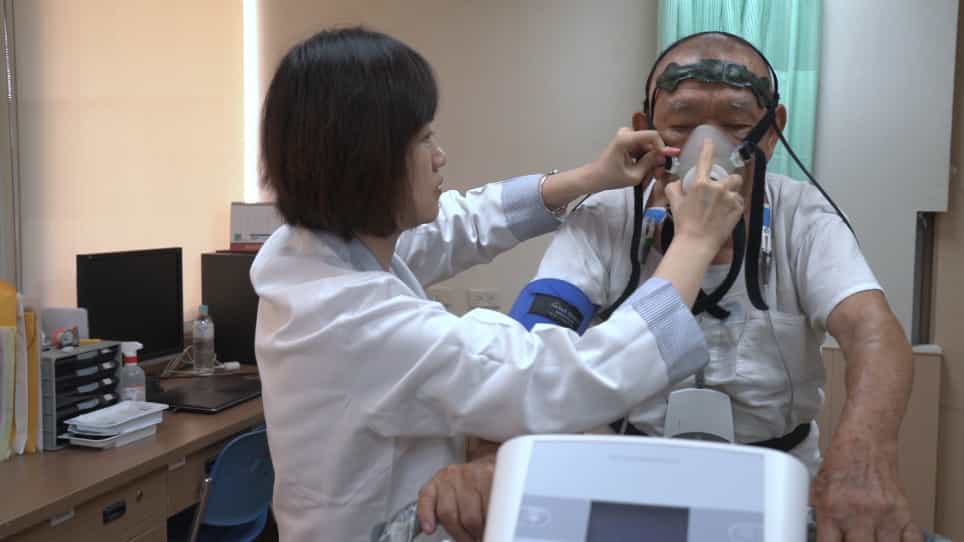

Integration of Brain Tissue Saturation Monitoring in Cardiopulmonary Exercise Testing in Patients with Heart Failure
Published on: October 1, 2019
[Comparison of peak oxygen uptake and VE/VCO2 slope, between children with and without heart failure]
Hermes Ilarraza-Lomelí1, Irma Miranda Chávez2, Javier Castañeda-López1
1Servicio de Rehabilitación Cardiaca y Medicina Física, Instituto Nacional de Cardiología Ignacio Chávez, Ciudad de México, México.

Abstract:
Heart failure is a health problem associated with disability and mortality. Physicians may stratify the risk of adult patients with heart failure using a cardiopulmonary exercise testing. Until now, in childhood this evaluation has been poorly used. The purpose of this study is to compare the peak oxygen uptake and minute ventilation/carbon dioxide production slope among children with heart failure versus children without heart disease (control).
Methods:
Thirty-eight children with heart failure were compared with 194 children without heart disease. All of them performed cardiopulmonary exercise testing using a symptom-limited ramp protocol. Differences between groups were compared using Chi-squared test, Student's t test, or ANOVA. Any value of p < 0.05 was considered significant.
Results:
Children with heart failure were older, taller, and with a higher prevalence of male gender. This group had also a lower peak oxygen uptake (27 ± 10 ml O2/kg/min) compared to the control group (37 ± 10 ml O2/kg/min); p < 0.001. The minute ventilation/carbon dioxide production was higher in the heart failure group (31 ± 4) than in controls (28 ± 6); p < 0.001.
Conclusion:
Children with heart failure showed lower peak oxygen uptake and higher minute ventilation/carbon dioxide production slope than the control group.
More Related Videos
 07:09
Assessment of Pulmonary Capillary Blood Volume, Membrane Diffusing Capacity, and Intrapulmonary Arteriovenous Anastomoses During Exercise
Published on: February 20, 2017
 08:44
Author Spotlight: Integrating Alveolar-Capillary Reserve Measurements in Exercise Adaptation and Therapeutic Strategies
Published on: February 2, 2024
Related Concept Videos
 01:17
Assessment of Diffusion and Perfusion
The Role of Diffusion in Respiration
Diffusion is the process by which molecules move from an area of higher concentration to an area of lower concentration. In the respiratory system, this...
 01:20
Assessment of Ventilation I: Respiratory Rate
A Ventilation assessment is critical for monitoring a patient's health status. Respiration, one of the most accessible vital signs, provides insights into the function of numerous body systems and can indicate serious health issues, such as brainstem injuries from head trauma.
Critical Guidelines for Assessing Ventilation:
 01:29
Assessment of Ventilation II: Respiratory Depth and Rhythm
Respiratory depth measures the volume of air inhaled or exhaled during a breath. It can vary from shallow to deep and typically remains consistent when a person is at rest or asleep. Occasionally, individuals will automatically inhale deeply, known as sighing, which inflates the lungs with more air than normal breathing.
To assess respiratory depth, observe the degree of chest excursion or movement:
 01:24
Respiratory Capacities
One key metric is the Inspiratory Capacity (IC), which represents the maximum amount of air that can be inhaled with full effort. IC is calculated by summing the tidal volume and inspiratory reserve volume, typically ranging from 2.4 to 3.6 liters.
The Functional Residual Capacity (FRC) represents the air in the...
 01:19
Factors Affecting Pulmonary Ventilation
Alveolar Surface Tension
The alveolar fluid lines the luminal surface of the alveoli and exerts a force called surface tension. This force is caused by the polar water molecules in the liquid being more strongly attracted to each...
 01:22
Respiratory Volumes and Capacities