
Uric Acid Crystals Induce Placental Inflammation and Alter Trophoblast Function via an IL-1-Dependent Pathway:
Marie-Eve Brien1,2,3, Cyntia Duval1,2, Julia Palacios1,2
1Ste-Justine Hospital Research Centre, Feto-Maternal and Neonatal Pathologies Research Axis, University of Montreal, Montreal, Quebec H3T 1C5, Canada.

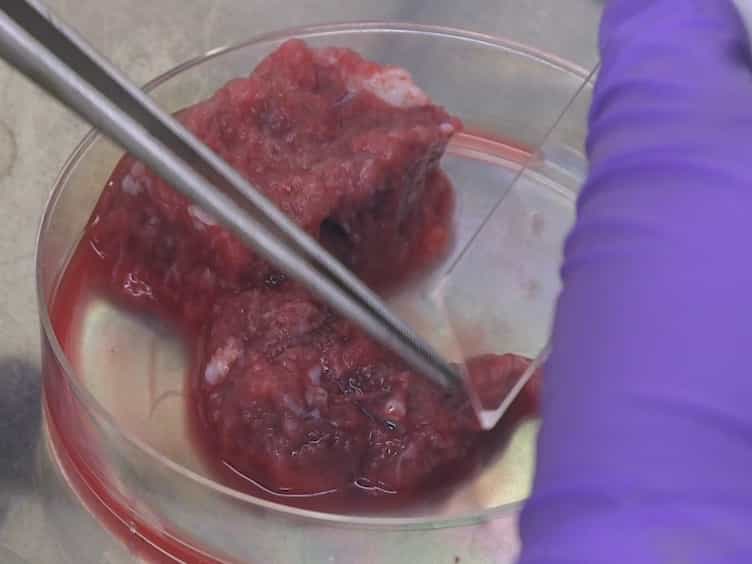
Excessive placental inflammation is associated with several pathological conditions, including stillbirth and fetal growth restriction. Although infection is a known cause of inflammation, a significant proportion of pregnancies have evidence of inflammation without any detectable infection. Inflammation can also be triggered by endogenous mediators, called damage associated molecular patterns or alarmins. One of these damage-associated molecular patterns, uric acid, is increased in the maternal circulation in pathological pregnancies and is a known agonist of the Nlrp3 inflammasome and inducer of inflammation. However, its effects within the placenta and on pregnancy outcomes remain largely unknown. We found that uric acid (monosodium urate [MSU]) crystals induce a proinflammatory profile in isolated human term cytotrophoblast cells, with a predominant secretion of IL-1β and IL-6, a result confirmed in human term placental explants. The proinflammatory effects of MSU crystals were shown to be IL-1-dependent using a caspase-1 inhibitor (inhibits IL-1 maturation) and IL-1Ra (inhibits IL-1 signaling). The proinflammatory effect of MSU crystals was accompanied by trophoblast apoptosis and decreased syncytialization. Correspondingly, administration of MSU crystals to rats during late gestation induced placental inflammation and was associated with fetal growth restriction. These results make a strong case for an active proinflammatory role of MSU crystals at the maternal-fetal interface in pathological pregnancies, and highlight a key mediating role of IL-1. Furthermore, our study describes a novel in vivo animal model of noninfectious inflammation during pregnancy, which is triggered by MSU crystals and leads to reduced fetal growth.
Excessive placental inflammation is associated with several pathological conditions, including stillbirth and fetal growth restriction. Although infection is a known cause of inflammation, a significant proportion of pregnancies have evidence of inflammation without any detectable infection. Inflammation can also be triggered by endogenous mediators, called damage associated molecular patterns or alarmins. One of these damage-associated molecular patterns, uric acid, is increased in the maternal circulation in pathological pregnancies and is a known agonist of the Nlrp3 inflammasome and inducer of inflammation. However, its effects within the placenta and on pregnancy outcomes remain largely unknown. We found that uric acid (monosodium urate [MSU]) crystals induce a proinflammatory profile in isolated human term cytotrophoblast cells, with a predominant secretion of IL-1β and IL-6, a result confirmed in human term placental explants. The proinflammatory effects of MSU crystals were shown to be IL-1-dependent using a caspase-1 inhibitor (inhibits IL-1 maturation) and IL-1Ra (inhibits IL-1 signaling). The proinflammatory effect of MSU crystals was accompanied by trophoblast apoptosis and decreased syncytialization. Correspondingly, administration of MSU crystals to rats during late gestation induced placental inflammation and was associated with fetal growth restriction. These results make a strong case for an active proinflammatory role of MSU crystals at the maternal-fetal interface in pathological pregnancies, and highlight a key mediating role of IL-1. Furthermore, our study describes a novel in vivo animal model of noninfectious inflammation during pregnancy, which is triggered by MSU crystals and leads to reduced fetal growth.
More Related Videos
 05:31
Author Spotlight: Modeling an Aspect of Preeclampsia in Female Mice Using Hypoxic Human Placenta-Derived Small Extracellular Vesicles
Published on: January 26, 2024
 12:02
Human Primary Trophoblast Cell Culture Model to Study the Protective Effects of Melatonin Against Hypoxia/reoxygenation-induced Disruption
Published on: July 30, 2016
Related Concept Videos
 01:07
Teratogenicity
 01:15
Transcytosis of IgG
IgG molecules from a mother undergo transcytosis starting around 13 weeks of gestation. The amount of IgG transferred and entering the fetal blood circulation increases with...
 01:17
Gastritis-II: Pathophysiology
In acute gastritis, the gastric mucosa becomes swollen and red and undergoes superficial erosion. Superficial ulceration may lead to bleeding.
In chronic gastritis, persistent or repeated insults lead to chronic inflammatory changes and, eventually, thinning or atrophy of the gastric tissue.
Gastritis can stem from various causes, each...