Related Experiment Video
Updated: Mar 9, 2026
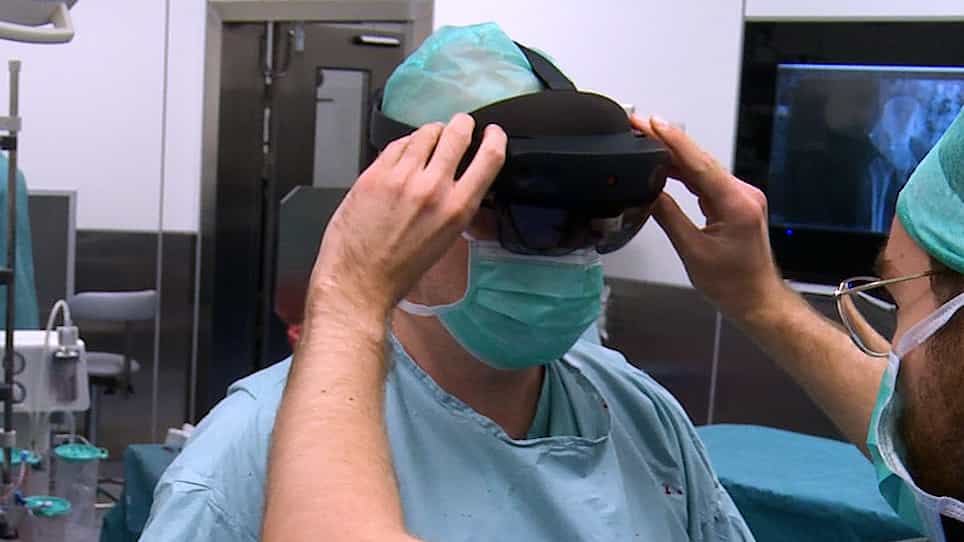
The Use of Mixed Reality in Custom-Made Revision Hip Arthroplasty: A First Case Report
Published on: August 4, 2022
Acetabular revision with bone grafting and cementation for aseptic loosening after primary Charnley low-friction hip
Riazuddin Mohammed1, Efstathios Drampalos, Paul Siney
1Centre for Hip Surgery, Wrightington Hospital, Appley Bridge, United Kingdom.

Purpose:
To review the outcome of acetabular revision with bone grafting and cementation for aseptic loosening after primary Charnley low-friction hip arthroplasty with structural bulk autografts in 15 patients.
Methods:
Records were reviewed for 3 men and 12 women aged 31 to 72 (mean, 53) years who underwent acetabular revision with bone grafting and cementation for aseptic loosening at a mean of 12.4 (range, 6.6-20.3) years after primary Charnley low-friction hip arthroplasty with superolateral structural bulk autografts from the femoral head for dysplastic hip (n=14) or bone loss secondary to acetabular fracture (n=1).
Results:
After a mean follow-up of 6.7 (range, 1.1-14.5) years, the mean Merle d'Aubigné and Postel score improved from 8.55 to 16.5. Bridging trabeculae was noted in 10 hips and graft remodelling in 5 hips. Five hips had ectopic ossification of Brooker grade 1 to 2. The mean hip centre of rotation was 21.6 (range, 16.2-30.6) mm. Two women required re-revision for aseptic loosening of the acetabulum after 8.5 and 6.6 years. The first one underwent re-revision with solid allograft for superolateral deficiency of the acetabulum. The second one underwent re-revision with solid and morselised bone allografts for loosened acetabulum. One patient had superior migrationof the acetabulum for 9 mm at year 2, but it was asymptomatic. One patient had a dislocation that was reduced with manipulation under anaesthesia. Threepatients had trochanteric non-union and presented with lateral thigh pain and tenderness, but no further surgery was performed.
Conclusion:
The medium-term outcome of acetabular revision with bone grafting and cementation is satisfactory. Repeat bone grafting is required to restore the anatomic acetabular position and bone loss secondary to acetabular loosening.
