Osseous metastases of chordoma: imaging and clinical findings
Connie Chang1, Ivan Chebib2, Martin Torriani3
1Division of Musculoskeletal Imaging and Intervention, Department of Radiology, Massachusetts General Hospital, 55 Fruit Street Yawkey 6E, Boston, MA, 02114, USA. cychang@mgh.harvard.edu.

Purpose:
To describe the imaging and clinical characteristics of chordoma osseous metastases (COM).
Materials And Methods:
Our study was IRB approved and HIPAA compliant. A retrospective search of our pathology database for pathology-proven COM yielded 15 patients who had undergone MRI, CT, bone scan, and/or FDG-PET/CT. The imaging and clinical features of the COMs were recorded. A control group of age and gender matched chordoma patients without osseous metastasis was evaluated.
Results:
The COM mean maximal dimension was 6.4 ± 4.0 cm. The majority (60%) of patients had one lesion. Extra-osseous soft tissue component was present in 85% and was larger than intra-osseous component in 76%. On MRI the lesions were heterogeneous but predominantly T2 hyperintense with hypointense septae, and with variable enhancement. On CT the lesions were typically destructive or permeative; calcifications were rare. The extent of the soft tissue component was isodense to muscle on CT and therefore better evaluated on MRI. COM was in a body part contiguous to the site of the primary tumor. Compared to the controls, COM patients were more likely to have local recurrence (P = 0.0009) and positive resection margins (P = 0.002). At 1 year, 33% of COM patients were deceased and 13% had progressive metastases.
Conclusion:
COM are associated with large extra-osseous soft tissue components, which are better visualized by MRI. They are often located in a body part contiguous to the site of the primary tumor, portend poor prognosis, and are associated with positive resection margins and local recurrence.

Related Concept Videos
 01:21
Aneurysm II: Clinical Manifestations and Diagnostic Studies
 01:29
Bone Disorders
Bone deposition is also affected by the levels of sex hormones like estrogen and testosterone that promote osteoblast activity and bone matrix synthesis. When the level of these hormones decreases due to aging, it causes a reduction in bone deposition. As a result, bone resorption by osteoclasts...
 01:17
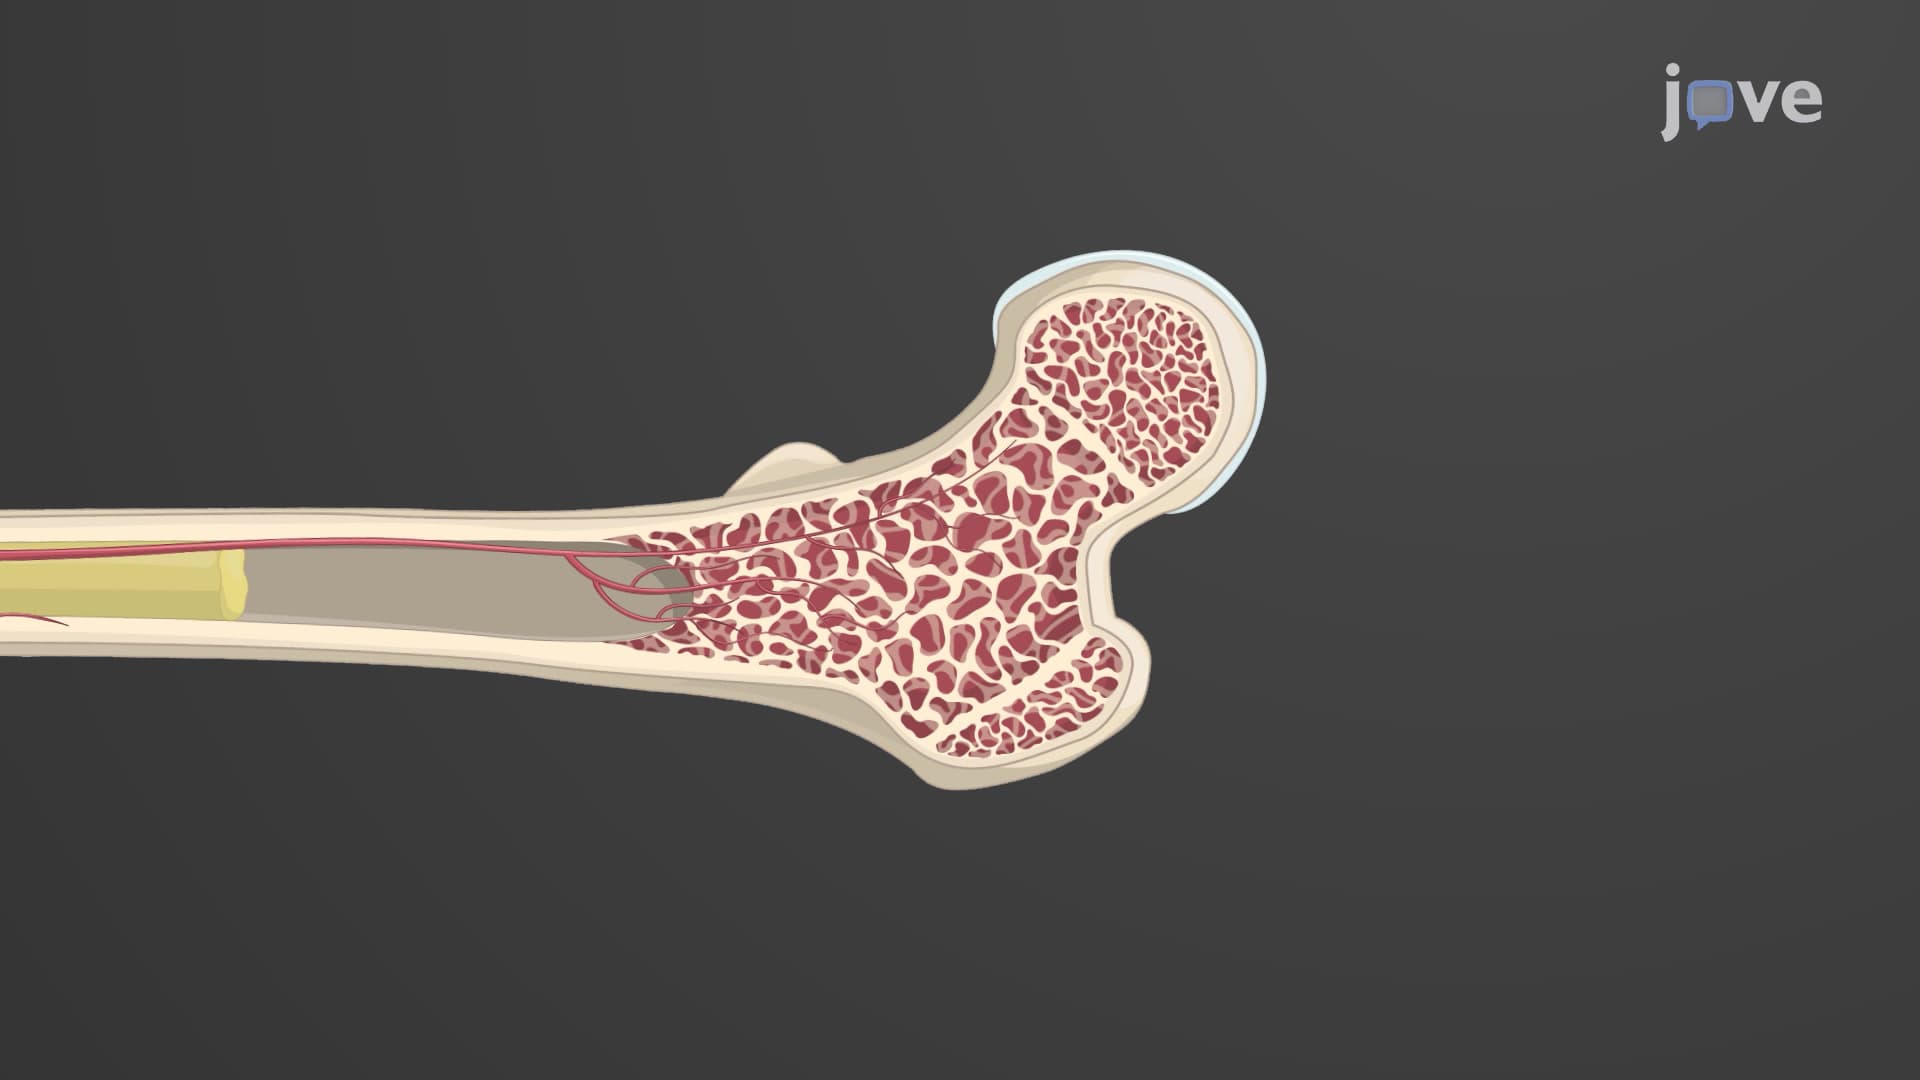
Gross Anatomy of Bone
The diaphysis is the tubular shaft that runs between the proximal and distal ends of the bone. The walls of the diaphysis are composed of dense and hard compact bone made of numerous osteons — the functional unit of the compact bone. The hollow region in the diaphysis is called the medullary cavity, which harbors the bone marrow. In infants and children, this marrow cavity is filled with red marrow, whereas in...
 01:24
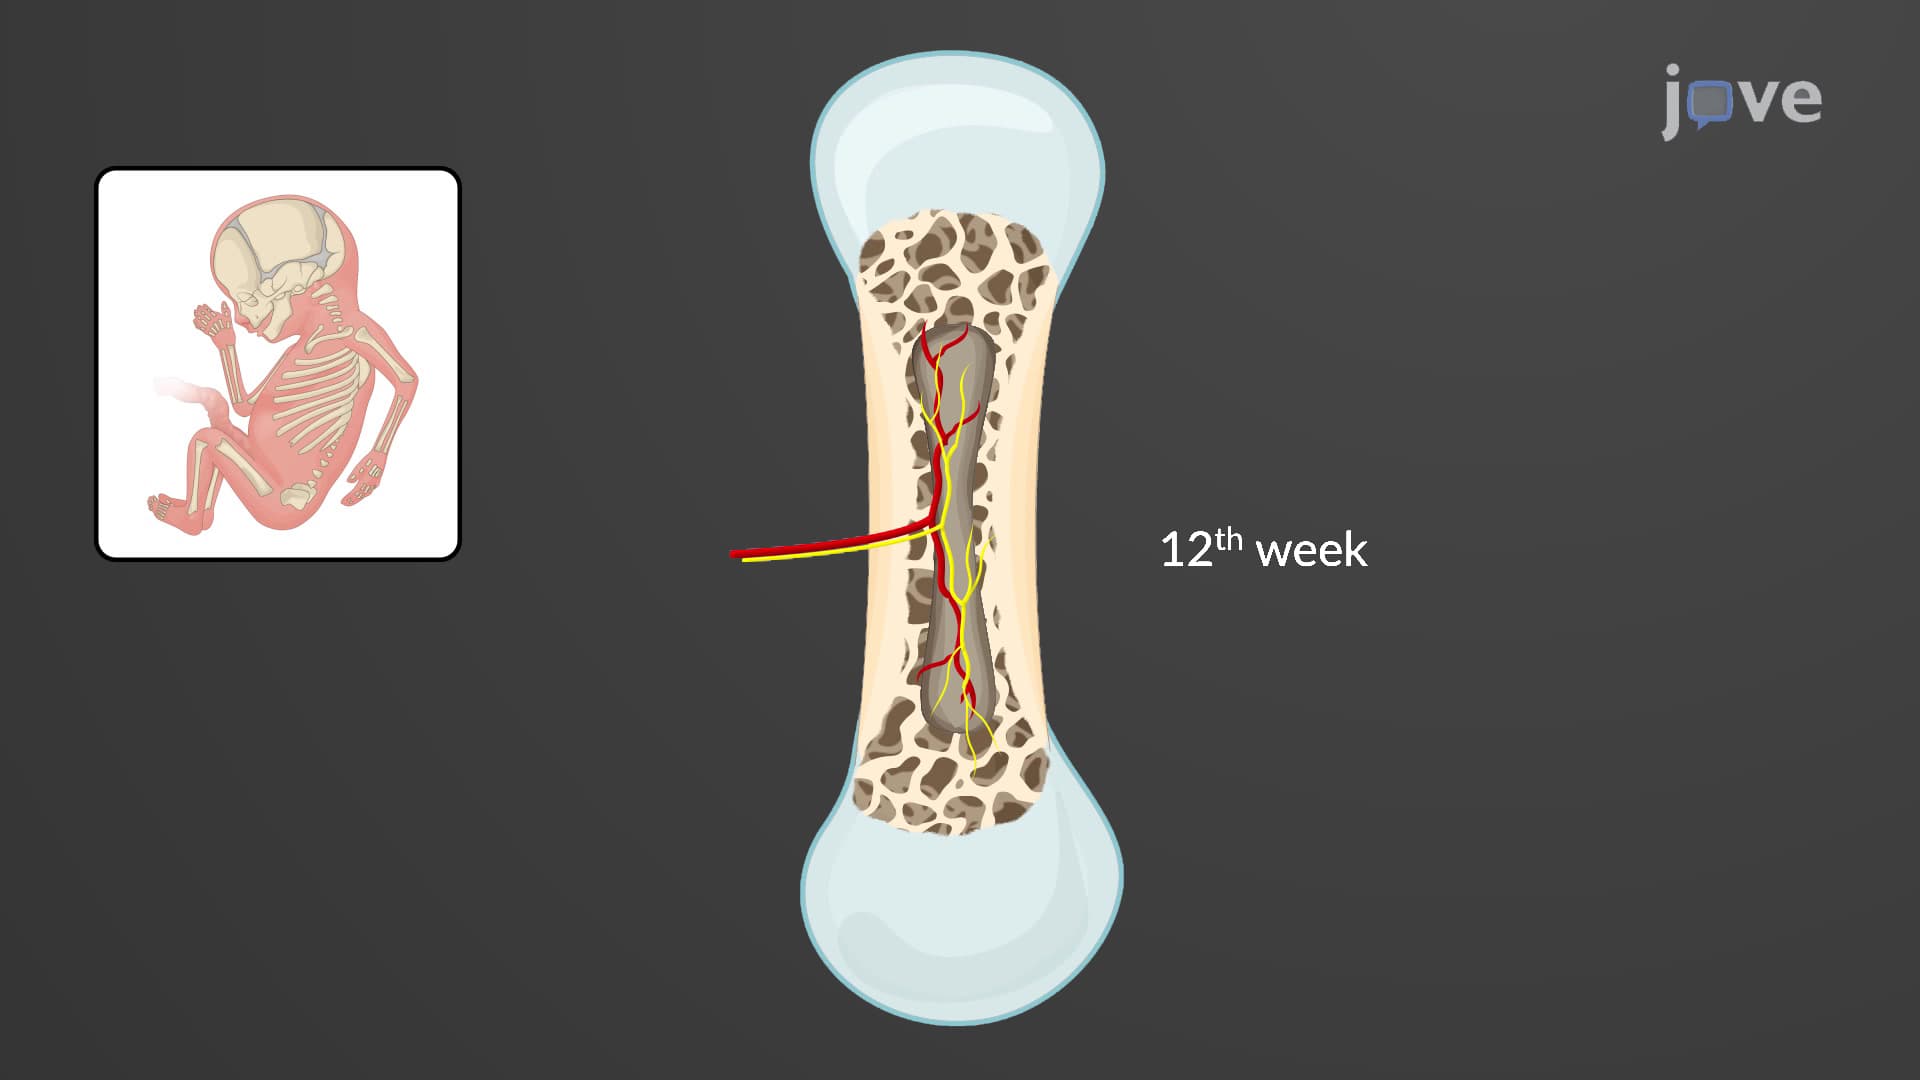
Bone Formation by Endochondral Ossification
 01:23
Mitral Stenosis II: Clinical features and Diagnostic Tests
 01:27
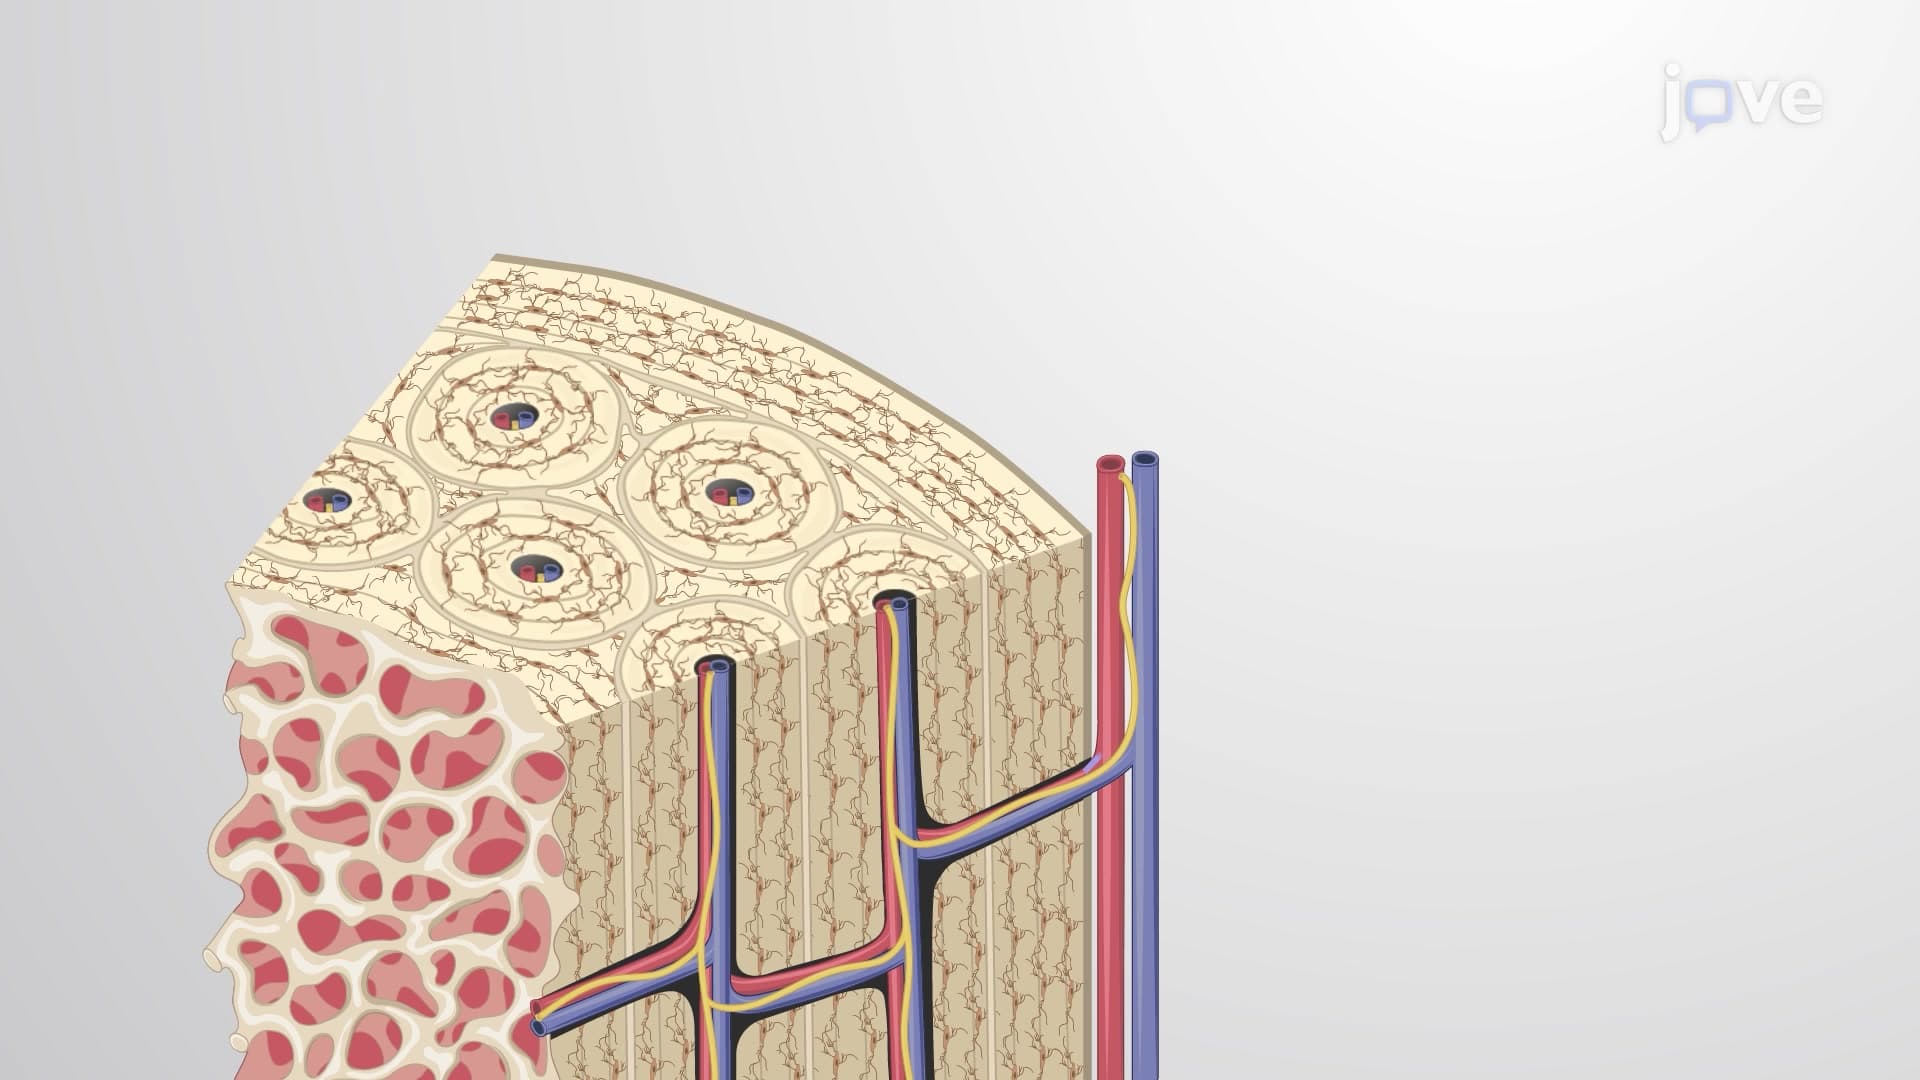
Compact Bone
Compact bone, also called cortical bone, is the denser, stronger of the two types of bone tissue. It is found under the periosteum and in the diaphyses of long bones, where it provides support and protection. The microscopic structural unit of compact bone is called an osteon, or haversian system. Each osteon is composed of concentric rings of calcified...