Related Experiment Video
Updated: Mar 9, 2026


Standardized Hemorrhagic Shock Induction Guided by Cerebral Oximetry and Extended Hemodynamic Monitoring in Pigs
Published on: May 21, 2019
The role of bicarbonate precursors in balanced fluids during haemorrhagic shock with and without compromised liver
B Ergin1, A Kapucu2, P Guerci1,3
1Department of Translational Physiology, Academic Medical Centre, Amsterdam, The Netherlands.

Background:
Lactate, acetate, and gluconate are anions used in balanced resuscitation fluids, of which lactate and acetate are considered bicarbonate precursors. This study investigated the role of the liver in the ability of balanced and unbalanced solutions to correct acid-base alterations and renal haemodynamics and microvascular oxygenation in a rat model of resuscitated haemorrhagic shock.
Methods:
Ringer's lactate, Ringer's acetate, PlasmaLyte, or normal saline were administered following haemorrhagic shock in the presence or absence of a 70% partial liver resection. Renal haemodynamics and microvascular oxygenation (by oxygen-dependent quenching of phosphorescence) were measured as well as concentrations of lactate, gluconate, and acetate in plasma and urine. Kidney wet and dry weight was also assessed.
Results:
Partial liver resection resulted in increased liver enzymes compared with control and shock groups (P < 0.01). Haemorrhagic shock decreased systemic and renal perfusion and reduced microvascular kidney oxygenation with lactic acidosis (P < 0.01). Resuscitation with balanced fluids did not fully restore renal oxygenation (P < 0.01). Ringer's acetate and PlasmaLyte increased bicarbonate content and restored pH better than Ringer's lactate or saline after partial liver resection (P < 0.01). Liver resection caused an increase in plasma gluconate after PlasmaLyte resuscitation (P < 0.05).
Conclusions:
Acetate-buffered balanced fluids show superior buffering effects compared with Ringer's lactate or saline. Gluconate is partially metabolized by the liver, although it does not contribute to acid-base control because of its excretion in urine. Acetate is metabolized regardless of liver function and may be the most efficient bicarbonate precursor. Lactate infusion tends to overwhelm the metabolism capacity of the residual liver.

Related Concept Videos
 01:22
Bicarbonate-Carbonic Acid Buffer
 01:29
Roles of Electrolytes: Chloride and Bicarbonate
Conditions such as hypochloremia can arise from insufficient chloride reabsorption by the kidneys, often compounded by extended bouts of diarrhea, vomiting,...
 01:25
Acid-Base Balance
When the pH of arterial blood rises above 7.45, it results in a condition called alkalosis. Conversely, a drop below 7.35 leads to...
 01:24
Diagnosing Acidosis and Alkalosis
First, the pH level is assessed to determine whether the blood pH is normal (7.35–7.45), low (acidosis), or high (alkalosis).
Next, the PCO2 and...
 01:29
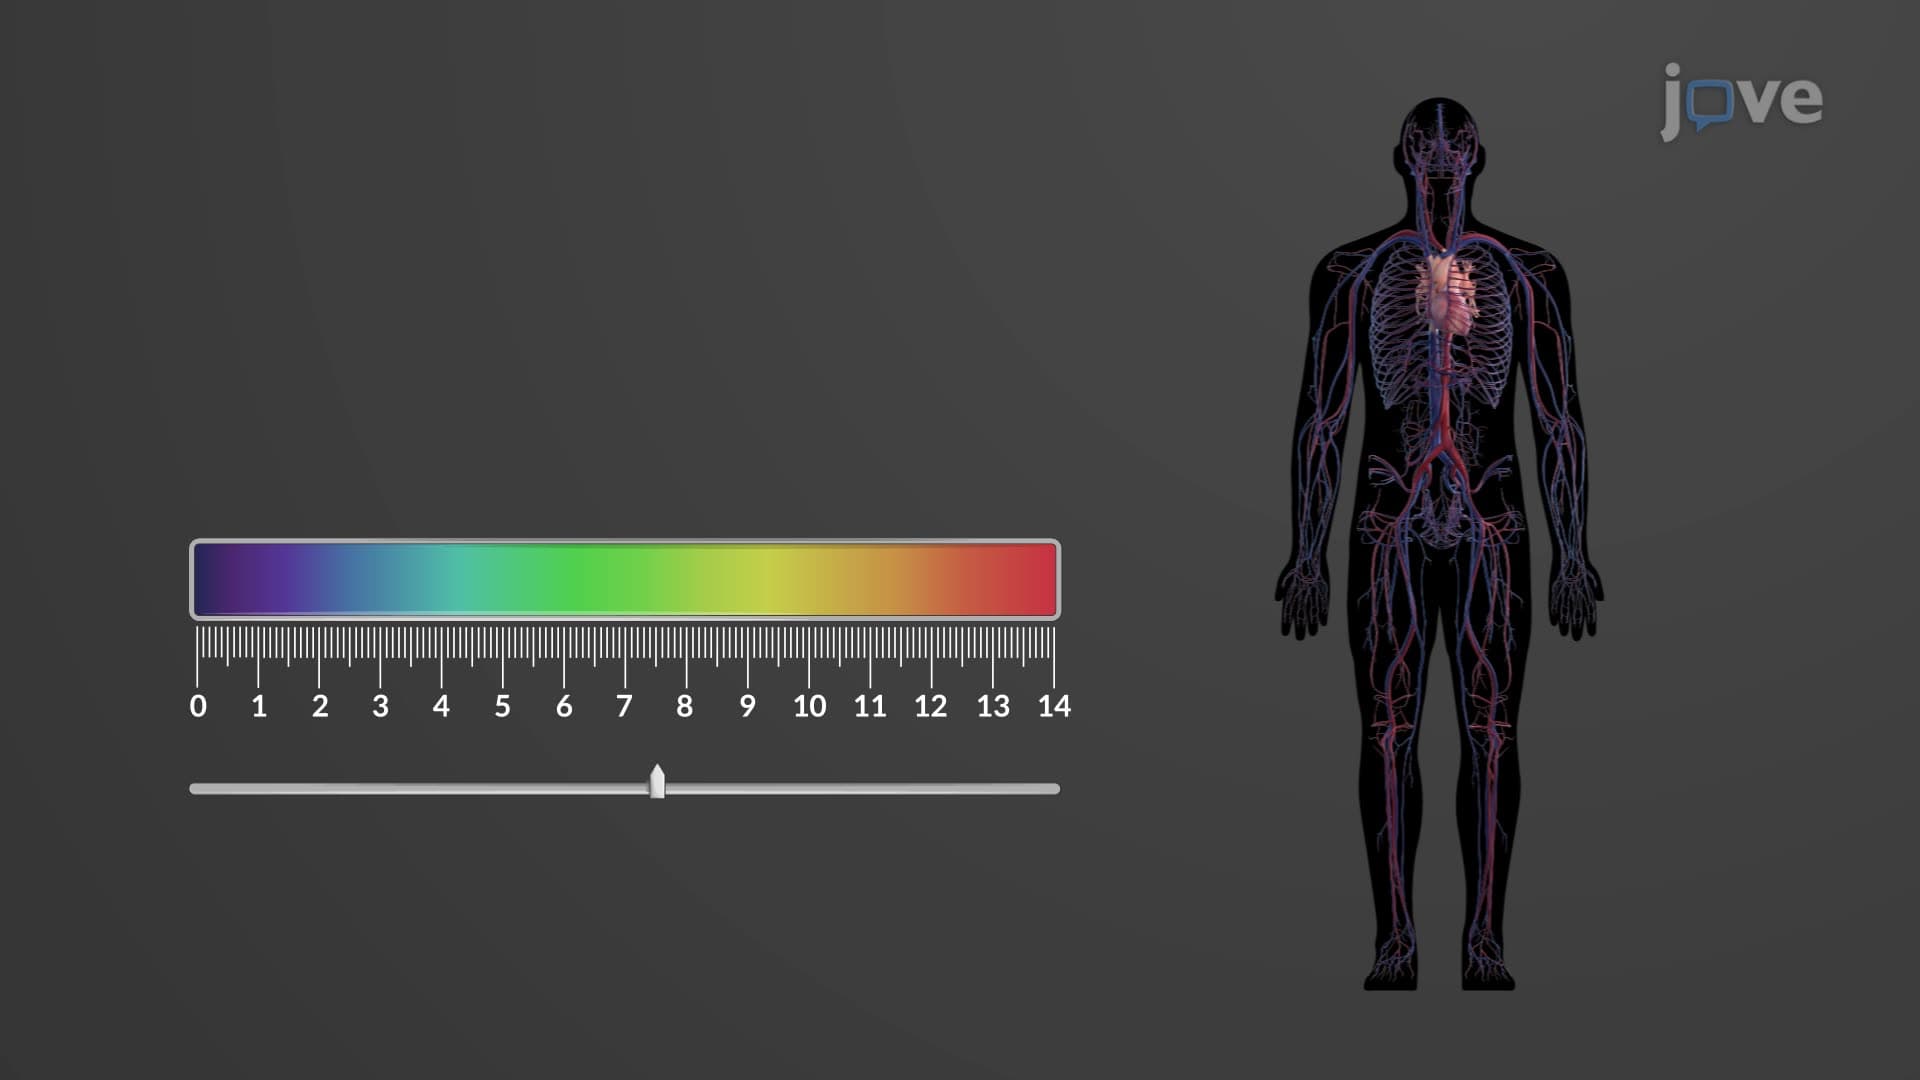
Disorders of Acid-Base Balance
Respiratory Acidosis and Alkalosis
Respiratory acidosis occurs due to an increase in the partial pressure of carbon dioxide PCO2 in the blood. It often arises from shallow breathing or impaired gas exchange caused by...
 01:28
Compensation Mechanisms
Respiratory Compensation
This mechanism addresses metabolic-induced pH imbalances by adjusting breathing rates. Respiratory compensation begins within minutes of detecting a pH...