Related Experiment Video
Updated: Mar 8, 2026
A Reversible, Non-invasive Method for Airway Resistance Measurements and Bronchoalveolar Lavage Fluid Sampling in Mice
Published on: April 13, 2010
Contribution of rostral fluid shift to intrathoracic airway narrowing in asthma
Swati A Bhatawadekar1, Mark D Inman2, Jeffrey J Fredberg3
1Toronto Rehabilitation Institute-University Health Network, Toronto, Ontario, Canada.

Abstract:
In asthma, supine posture and sleep increase intrathoracic airway narrowing. When humans are supine, because of gravity fluid moves out of the legs and accumulates in the thorax. We hypothesized that fluid shifting out of the legs into the thorax contributes to the intrathoracic airway narrowing in asthma. Healthy and asthmatic subjects sat for 30 min and then lay supine for 30 min. To simulate overnight fluid shift, supine subjects were randomized to receive increased fluid shift out of the legs with lower body positive pressure (LBPP, 10-30 min) or none (control) and crossed over. With forced oscillation at 5 Hz, respiratory resistance (R5) and reactance (X5, reflecting respiratory stiffness) and with bioelectrical impedance, leg and thoracic fluid volumes (LFV, TFV) were measured while subjects were seated and supine (0 min, 30 min). In 17 healthy subjects (age: 51.8 ± 10.9 yr, FEV1/FVC z score: -0.4 ± 1.1), changes in R5 and X5 were similar in both study arms (P > 0.05). In 15 asthmatic subjects (58.5 ± 9.8 yr, -2.1 ± 1.3), R5 and X5 increased in both arms (ΔR5: 0.6 ± 0.9 vs. 1.4 ± 0.8 cmH2O·l-1·s-1, ΔX5: 0.3 ± 0.7 vs. 1.1 ± 0.9 cmH2O·l-1·s-1). The increases in R5 and X5 were 2.3 and 3.7 times larger with LBPP than control, however (P = 0.008, P = 0.006). The main predictor of increases in R5 with LBPP was increases in TFV (r = 0.73, P = 0.002). In asthmatic subjects, the magnitude of increases in X5 with LBPP was comparable to that with posture change from sitting to supine (1.1 ± 0.9 vs. 1.4 ± 0.9 cmH2O·l-1·s-1, P = 0.32). We conclude that in asthmatic subjects fluid shifting from the legs to the thorax while supine contributed to increases in the respiratory resistance and stiffness.NEW & NOTEWORTHY In supine asthmatic subjects, application of positive pressure to the lower body caused appreciable increases in respiratory system resistance and stiffness. Moreover, these changes in respiratory mechanics correlated positively with increase in thoracic fluid volume. These findings suggest that fluid shifts from the lower body to the thorax may contribute to overnight intrathoracic airway narrowing and worsening of asthma symptoms.


Related Concept Videos
 01:19
Factors Affecting Pulmonary Ventilation
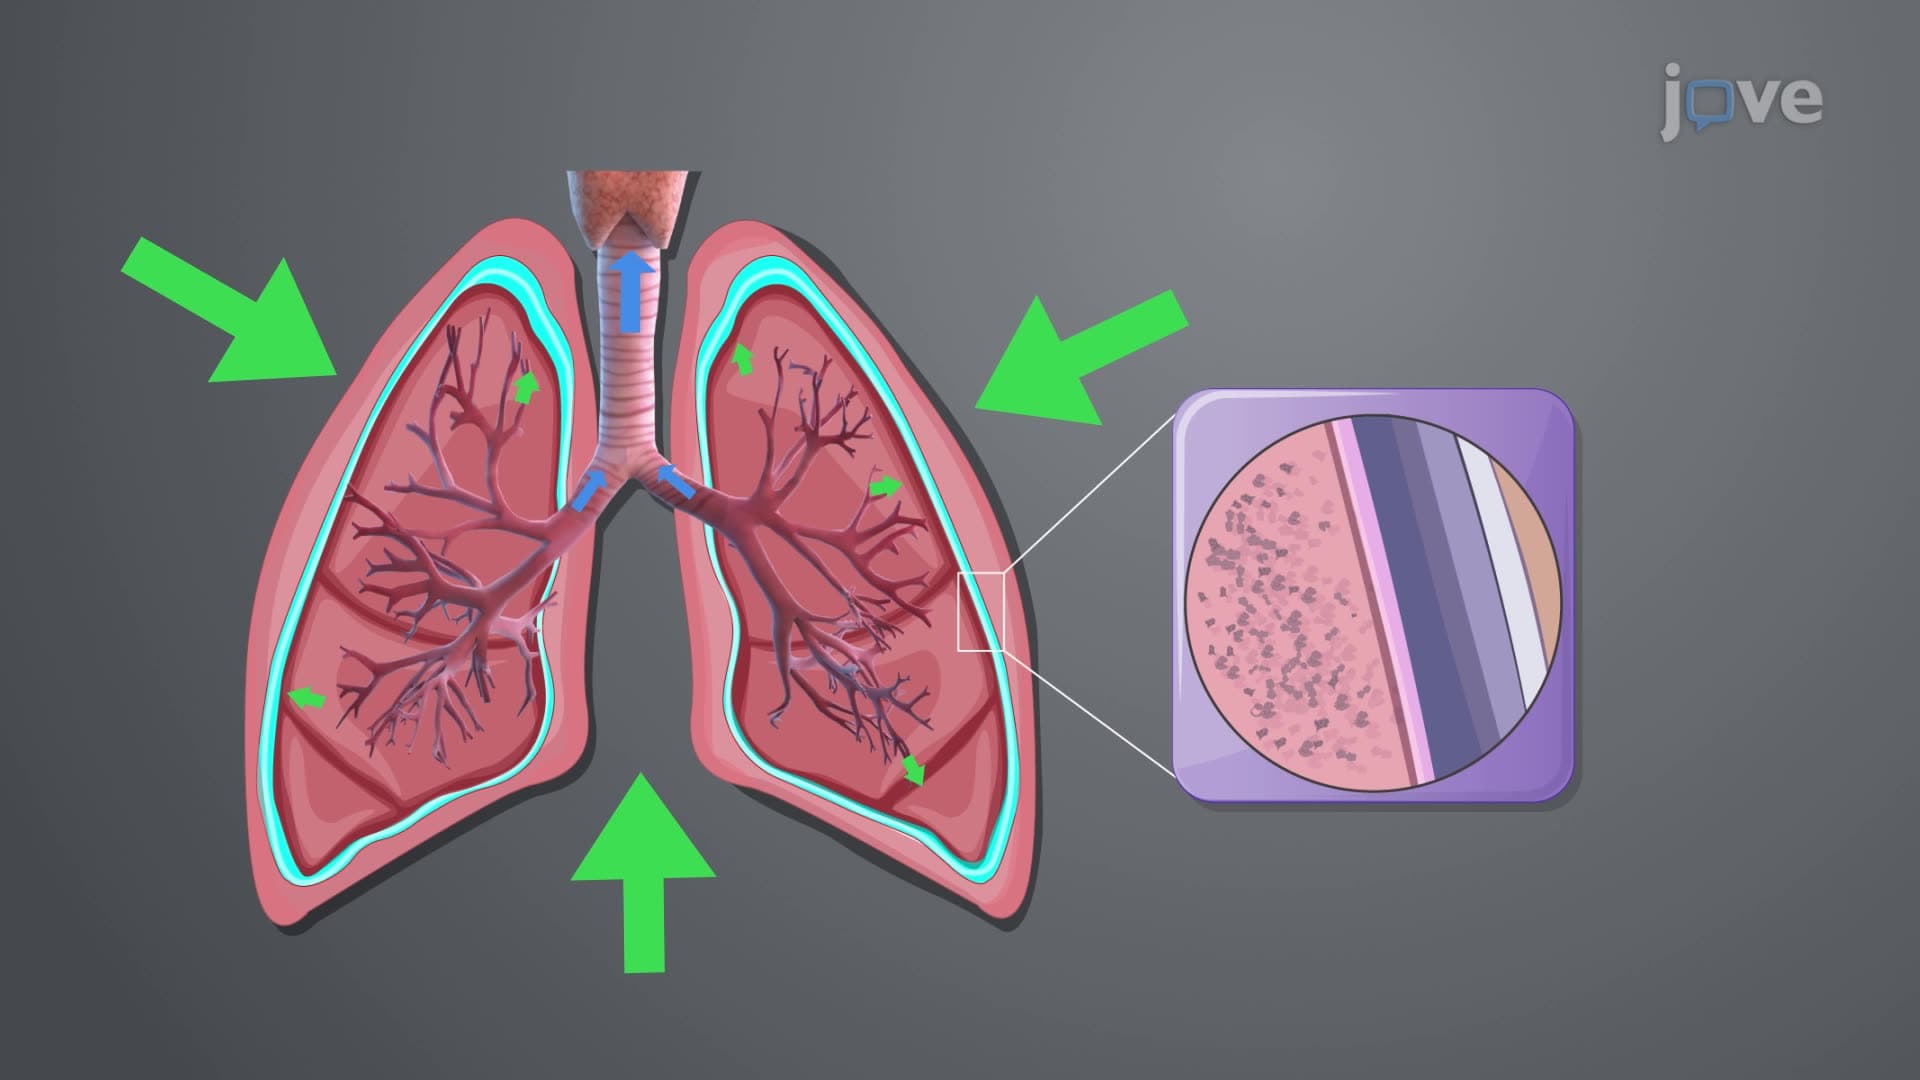
Alveolar Surface Tension
The alveolar fluid lines the luminal surface of the alveoli and exerts a force called surface tension. This force is caused by the polar water molecules in the liquid being more strongly attracted to each...
 01:05
Breathing
 01:24
Pressure Relationships in Thoracic Cavity
Breathing Mechanisms
Both intra-alveolar and intrapleural pressures rely on specific lung properties. The ability to breathe—allowing air to enter the lungs...
 01:24
Pulmonary Ventilation: Inhalation
Boyle's law becomes particularly pertinent when examining respiratory...
 01:26
Asthma-II: Pathophysiology and Classification
Additionally, environmental and genetic factors play crucial roles in determining an individual's susceptibility to asthma and the severity of their condition.
Critical processes in asthma pathophysiology include:
 01:20
Asthma: Pathogenesis and Management
Asthma is classified as allergic and non-allergic. Allergens such as dust mites, pollen, and pet dander trigger allergic asthma, while factors like cold air, intense emotions, or exercise can induce non-allergic asthma.