Related Experiment Video
Updated: Mar 8, 2026
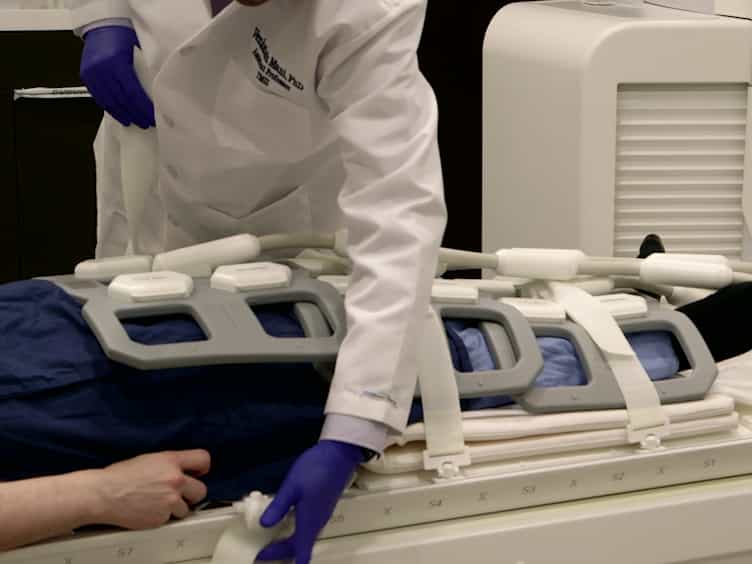

A Multicenter MRI Protocol for the Evaluation and Quantification of Deep Vein Thrombosis
Published on: June 2, 2015
Practice Patterns of Venous Thromboembolism Prophylaxis in Underweight, Critically Ill Patients with Neurologic
Kevin Betthauser1,2, Hannah Pope3, Mollie Gowan3
1Department of Pharmacy, Barnes-Jewish Hospital, 216 S. Kingshighway Boulevard, Mailstop 90-52-411, St. Louis, MO, 63110, USA. kxb0665@bjc.org.

Insights
Venous thromboembolism prophylaxis in underweight patients with neurologic injury is not guided by current literature. Underweight patients experienced increased intracranial hematoma expansion, suggesting caution with unfractionated heparin dosing.
Area of Science:
- Neurology
- Critical Care Medicine
- Pharmacology
Background:
- Venous thromboembolism (VTE) prophylaxis guidelines lack specific recommendations for underweight patients with neurologic injuries.
- Current literature and clinical practices do not adequately address VTE prophylaxis strategies in this vulnerable patient population.
Purpose of the Study:
- To investigate VTE prophylaxis strategies used in underweight patients with neurologic injury.
- To compare the incidence of thrombotic and bleeding events between underweight and non-obese patients receiving VTE prophylaxis.
Main Methods:
- Retrospective review of adult patients with neurologic injury admitted to a neurology/neurosurgery ICU over 6 years.
- Inclusion criteria: admission ≥72 hours, VTE prophylaxis order, and BMI <30 kg/m².
- Stratification into underweight (BMI ≤18.5 kg/m² or weight ≤50.0 kg) and non-obese (BMI 18.6-29.9 kg/m²) groups, matched 2:1 on age, diagnosis, and disease severity.
Main Results:
- Unfractionated heparin (UFH) was the most common VTE prophylaxis, with dose variations observed between groups.
- No significant difference in overall bleeding or thrombotic events between underweight and non-obese patients.
- Underweight patients showed a significantly higher rate of intracranial hematoma expansion (45.5% vs. 8.3%).
- A trend towards increased bleeding risk was noted with UFH doses >150 units/kg/day.
Conclusions:
- Current clinical practice for VTE prophylaxis in neurologically injured underweight patients does not involve routine dose reductions.
- Increased UFH doses (>150 units/kg/day) in underweight, neurologically injured patients warrant caution due to a potential increased bleeding risk.
- Further research is necessary to validate these findings and refine VTE prophylaxis guidelines for this population.
Purpose:
Venous thromboembolism (VTE) prophylaxis in underweight patients with neurologic injury remains unaddressed by guidelines and primary literature. This study aimed to describe VTE prophylaxis strategies employed in this population and compare the impact of underweight and non-obese patients on thrombotic and bleeding events.
Methods:
A retrospective review of adults admitted with a diagnosis of neurologic injury to a neurology/neurosurgery intensive care unit (ICU) over 6 years. Patients admitted ≥72 h with an order for VTE prophylaxis during admission, and a body mass index (BMI) <30 kg/m2 were included. Patients were stratified to underweight (BMI ≤18.5 kg/m2 or weight ≤50.0 kg) or non-obese (BMI 18.6-29.9 kg/m2) groups and matched, 2:1, on age, diagnosis, and disease severity.
Results:
The most common regimen in the underweight (n = 107) and non-obese (n = 214) group was unfractionated heparin (UFH) 5000 units subcutaneously Q12 h (69.1 vs. 83.6%; p = 0.003). Only underweight patients received UFH 2500 units subcutaneously Q12 h (17.8 vs. 0.0%; p < 0.0001). The proportion of overall bleeding and thrombotic events while receiving VTE prophylaxis was not significantly different. The proportion of underweight patients developing intracranial hematoma expansion while receiving prophylaxis versus non-obese patients (45.5 vs. 8.3%; p = 0.017) was significant. Patients receiving >150 units/kg/day of UFH displayed a trend toward increased risk of bleeding (9.7 vs. 4.2%; p = 0.064).
Conclusions:
Current practice does not reflect dose reductions for neurologically injured, underweight patients. Caution should be considered when using increased doses of UFH in neurologically injured patients that are underweight and/or may be exposed to >150 units/kg/day of UFH. Continued assessment of VTE prophylaxis is needed to confirm these findings.
Related Concept Videos
 01:29
Venous Thrombosis III: Interprofessional Care
 01:30
Venous Thrombosis IV: Nursing Management
 01:27
Pulmonary Embolism III: Nursing Management
 01:29
Pulmonary Embolism II: Diagnostic Studies and Interprofessional Care
 01:26
Peripheral Artery Disease IV: Nursing Management
 01:30
Anticoagulant Drugs: Low-Molecular-Weight Heparins