Effect of large weight reductions on measured and estimated kidney function
Related Experiment Video
Updated: Mar 7, 2026

5/6th Nephrectomy in Combination with High Salt Diet and Nitric Oxide Synthase Inhibition to Induce Chronic Kidney Disease in the Lewis Rat
Published on: July 3, 2013
Bernt Johan von Scholten1, Frederik Persson2, Maria S Svane3
1Steno Diabetes Center Copenhagen, Niels Steensens Vej 1, 2820, Gentofte, Denmark. bvon0013@regionh.dk.

Background:
When patients experience large weight loss, muscle mass may be affected followed by changes in plasma creatinine (pCr). The MDRD and CKD-EPI equations for estimated GFR (eGFR) include pCr. We hypothesised that a large weight loss reduces muscle mass and pCr causing increase in eGFR (creatinine-based equations), whereas measured GFR (mGFR) and cystatin C-based eGFR would be unaffected if adjusted for body surface area.
Methods:
Prospective, intervention study including 19 patients. All attended a baseline visit before gastric bypass surgery followed by a visit six months post-surgery. mGFR was assessed during four hours plasma 51Cr-EDTA clearance. GFR was estimated by four equations (MDRD, CKD-EPI-pCr, CKD-EPI-cysC and CKD-EPI-pCr-cysC). DXA-scans were performed at baseline and six months post-surgery to measure changes in lean limb mass, as a surrogate for muscle mass.
Results:
Patients were (mean ± SD) 40.0 ± 9.3 years, 14 (74%) were female and 5 (26%) had type 2 diabetes, baseline weight was 128 ± 19 kg, body mass index 41 ± 6 kg/m2 and absolute mGFR 122 ± 24 ml/min. Six months post-surgery weight loss was 27 (95% CI: 23; 30) kg, mGFR decreased by 9 (-17; -2) from 122 ± 24 to 113 ± 21 ml/min (p = 0.024), but corrected for current body surface area (BSA) mGFR was unchanged by 2 (-5; 9) ml/min/1.73 m2 (p = 0.52). CKD-EPI-pCr increased by 12 (6; 17) and MDRD by 13 (8; 18) (p < 0.001 for both), while CKD-EPI-cysC was unchanged by 2 (-8; 4) ml/min/1.73 m2 (p = 0.51). Lean limb mass was reduced by 3.5 (-4.4;-2.6; p < 0.001) kg and change in lean limb mass correlated with change in plasma creatinine (R 2 = 0.28, p = 0.032).
Conclusions:
Major weight reductions are associated with a reduction in absolute mGFR, which may reflect resolution of glomerular hyperfiltration, while mGFR adjusted for body surface area was unchanged. Estimates of GFR based on creatinine overestimate renal function likely due to changes in muscle mass, whereas cystatin C based estimates are unaffected.
Trial Registration:
ClinicalTrials.gov, NCT02138565 . Date of registration: March 24, 2014.

Related Concept Videos
 01:28
Drug Dosing in Renal Diseases: Estimation of Glomerular Filtration Rate Based on Serum Creatinine Concentration
 01:25
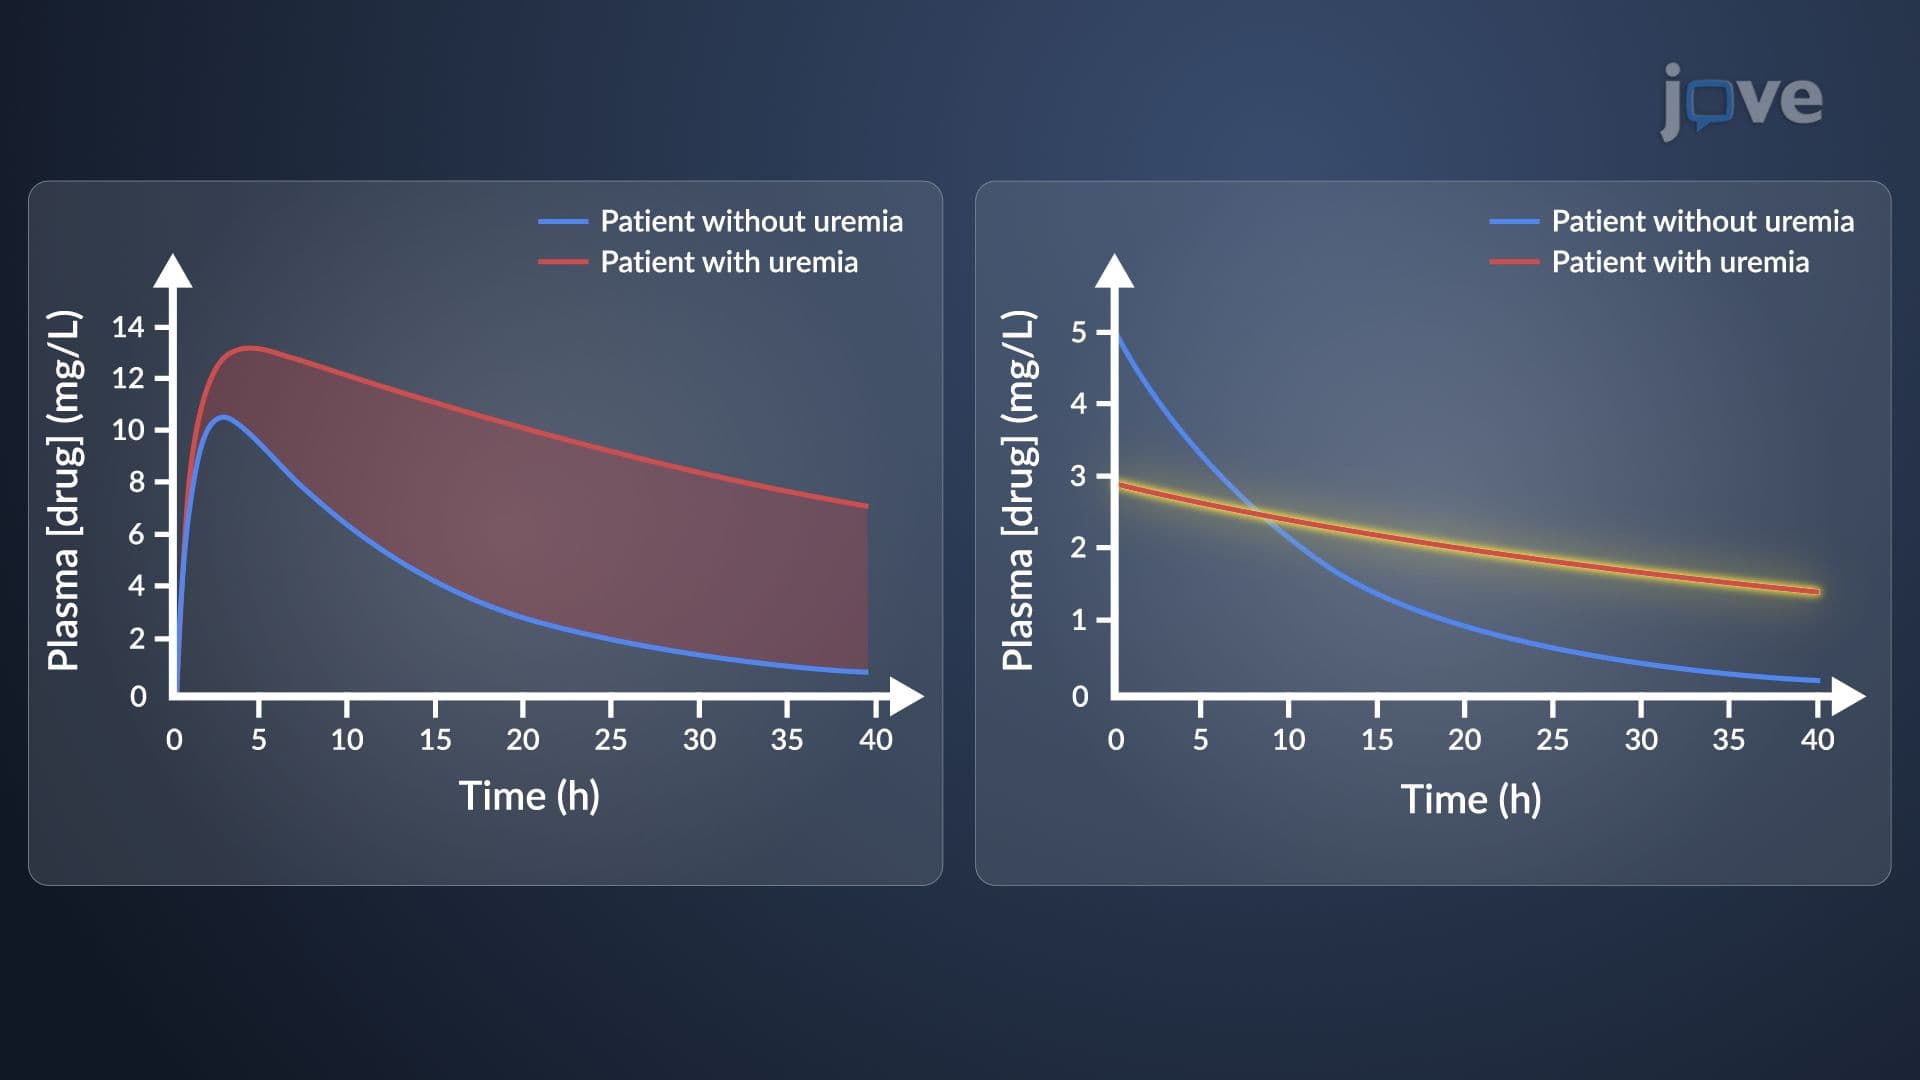
Drug Dosing in Renal Diseases: Dose Adjustments Based on Drug Clearance and Elimination Rate Constant
 01:25
Drug Dosing in Renal Diseases: Measurement of Glomerular Filtration Rate
 01:17
Factors Affecting Renal Clearance: Renal Impairment
One condition associated with renal failure is uremia. Uremia is characterized by impaired glomerular filtration and fluid accumulation in the body. This condition hinders the renal clearance of drugs, resulting in drug accumulation and potential...
 01:11
Renal Failure: Dose Adjustments
Reduced renal clearance and elimination rate are common outcomes of renal impairment. These alterations lead to a prolonged elimination half-life and an altered apparent volume of distribution for drugs. As a result, dosage adjustments are typically necessary to maintain optimal drug levels in the body.
However, dosage adjustments...
 01:25
Drug Dosing in Renal Diseases: Measurement of Serum Creatinine Concentration and Clearance