
Myocardial Oxygen Consumption and Efficiency in Aortic Valve Stenosis Patients With and Without Heart Failure
Nils Henrik Stubkjær Hansson1, Jens Sörensen2, Hendrik Johannes Harms2
1Department of Cardiology, Aarhus University Hospital, Aarhus, Denmark nilhan@rm.dk.

Background:
Myocardial oxygen consumption (MVO2) and its coupling to contractile work are fundamentals of cardiac function and may be involved causally in the transition from compensated left ventricular hypertrophy to failure. Nevertheless, these processes have not been studied previously in patients with aortic valve stenosis (AS).
Methods And Results:
Participants underwent 11C-acetate positron emission tomography, cardiovascular magnetic resonance, and echocardiography to measure MVO2 and myocardial external efficiency (MEE) defined as the ratio of left ventricular stroke work and the energy equivalent of MVO2. We studied 10 healthy controls (group A), 37 asymptomatic AS patients with left ventricular ejection fraction ≥50% (group B), 12 symptomatic AS patients with left ventricular ejection fraction ≥50% (group C), and 9 symptomatic AS patients with left ventricular ejection fraction <50% (group D). MVO2 did not differ among groups A, B, C, and D (0.105±0.02, 0.117±0.024, 0.129±0.032, and 0.104±0.026 mL/min per gram, respectively; P=0.07), whereas MEE was reduced in group D (21.0±1.6%, 22.3±3.3%, 22.1±4.2%, and 17.3±4.7%, respectively; P<0.05). Similarly, patients with global longitudinal strain greater than -12% and paradoxical low-flow, low-gradient AS had impaired MEE (P<0.05 versus controls). The ability to discriminate between symptomatic and asymptomatic patients was superior for global longitudinal strain compared with MVO2 and MEE (area under the curve 0.98, 0.48, and 0.61, respectively; P<0.05).
Conclusions:
AS patients display a persistent ability to maintain normal MVO2 and MEE (ie, the ability to convert energy into stroke work); however, patients with left ventricular ejection fraction <50%; global longitudinal strain greater than -12%; or paradoxical low-flow, low-gradient AS demonstrate reduced MEE. These findings suggest that mitochondrial uncoupling contributes to the dismal prognosis in patients with reduced contractile function or paradoxical low-flow, low-gradient AS.

Related Concept Videos
 01:29
Pathophysiology of Cardiac Performance
 01:27
Mitral Stenosis IV: Nursing Management
 01:22
Mitral Stenosis I: Introduction
 01:23
Mitral Stenosis II: Clinical features and Diagnostic Tests
 01:19
Cardiac Output I:Effect of Heart Rate on Cardiac Output
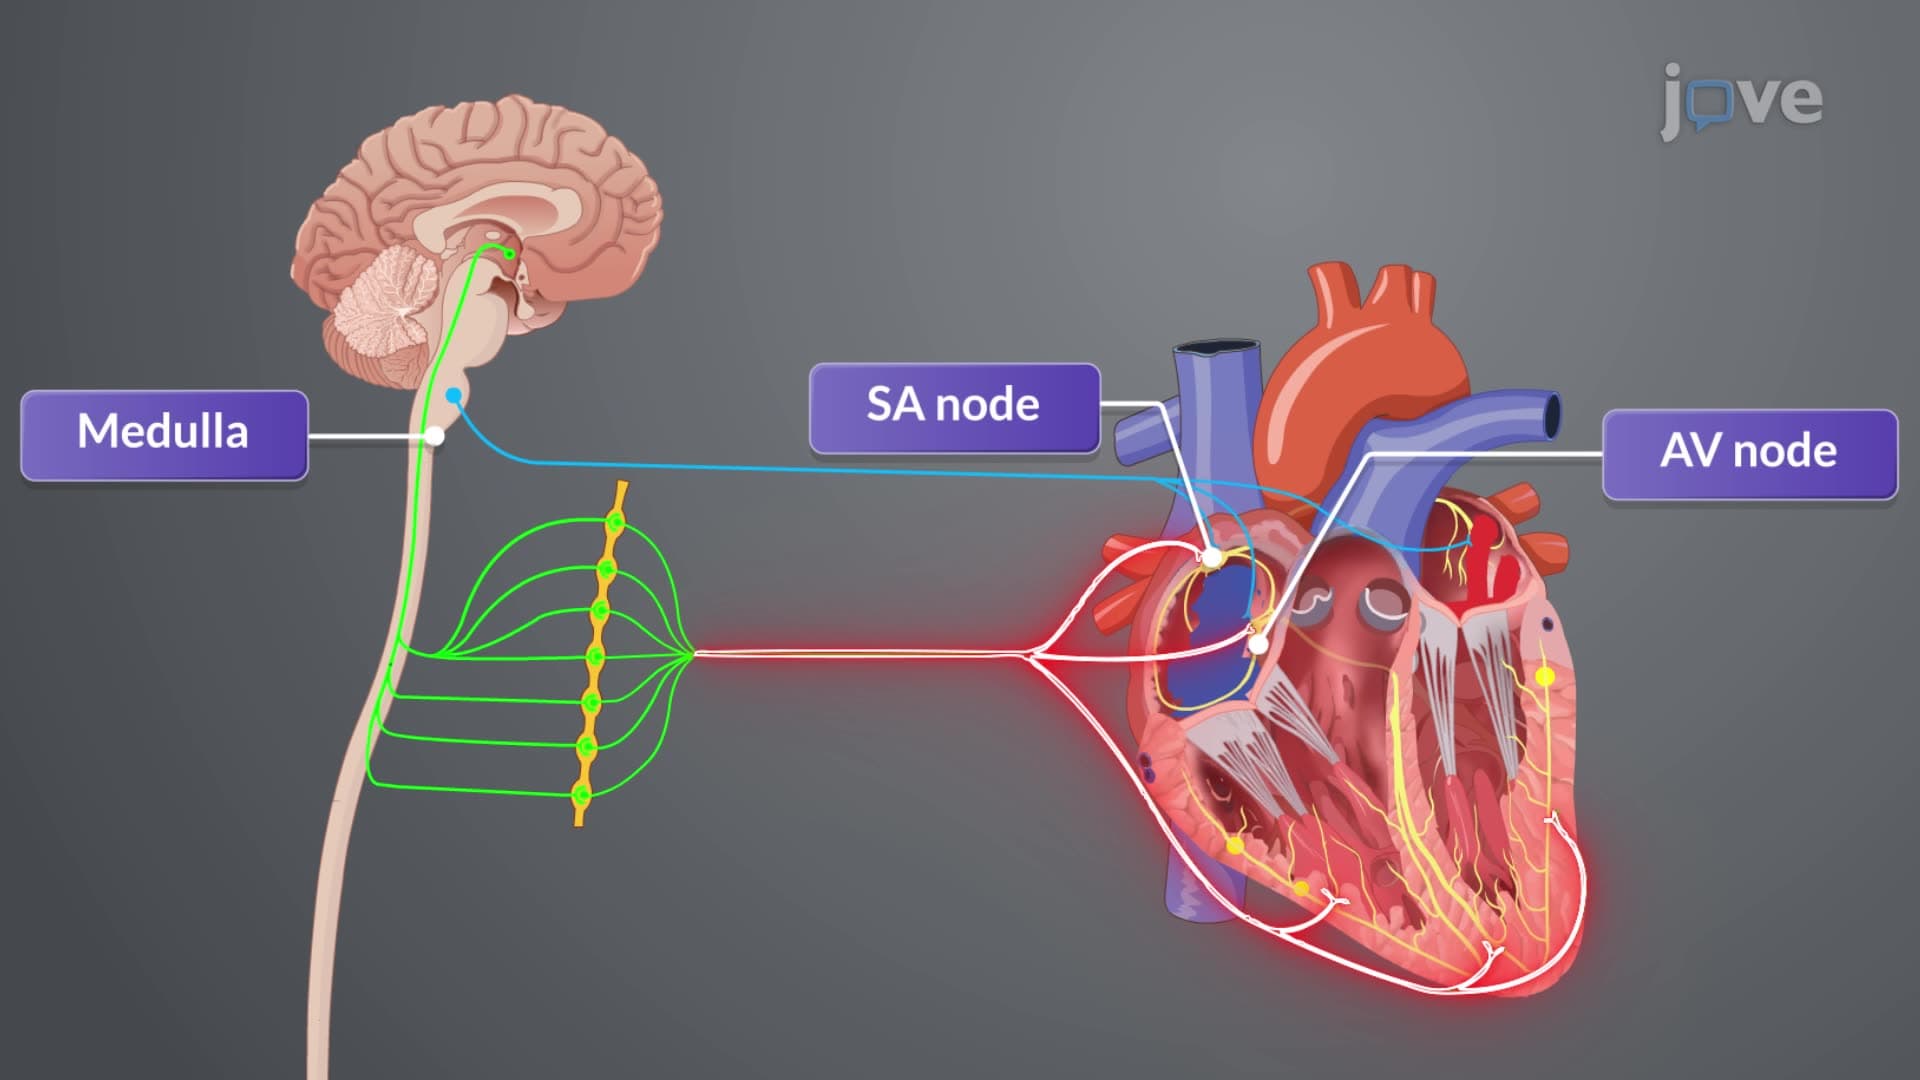
Cardiac output (CO) refers to the total amount of blood ejected by one of the ventricles in liters per minute (L/min). In a resting adult, CO ranges from 5 to 6 L/min, adjusting according to the body's metabolic requirements.
Effect of Heart Rate on Cardiac Output
Cardiac output adapts to metabolic demands during stress, physical activity, or illness. The autonomic nervous system regulates heart rate via the sinoatrial node. The parasympathetic nervous system decreases heart...
 01:22
Cardiac Output II: Effect of Stroke Volume on Cardiac Output
Preload
Preload refers to the initial elongation of the cardiac myocytes before contraction and is related to the volume of blood filling the heart at the end of diastole, or end-diastolic volume. The...