Related Experiment Video
Updated: Mar 7, 2026


Manual Therapy for a Chronic Non-Specific Low Back Pain Rat Model
Published on: August 11, 2023
Diazepam Is No Better Than Placebo When Added to Naproxen for Acute Low Back Pain
Benjamin W Friedman1, Eddie Irizarry1, Clemencia Solorzano2
1Department of Emergency Medicine, Albert Einstein College of Medicine, Montefiore Medical Center, Bronx, NY.

Study Objective:
Low back pain causes more than 2.5 million visits to US emergency departments (EDs) annually. Low back pain patients are often treated with nonsteroidal anti-inflammatory drugs and benzodiazepines. The former is an evidence-based intervention, whereas the efficacy of the latter has not been established. We compare pain and functional outcomes 1 week and 3 months after ED discharge among patients randomized to a 1-week course of naproxen+diazepam versus naproxen+placebo.
Methods:
This was a randomized, double-blind, comparative efficacy clinical trial conducted in an urban health care system. Patients presenting with acute, nontraumatic, nonradicular low back pain of no more than a duration of 2 weeks were eligible for enrollment immediately before discharge from an ED if they had a score greater than 5 on the Roland-Morris Disability Questionnaire, a validated 24-item inventory of functional impairment caused by low back pain. Higher scores on the questionnaire indicate greater functional disability. The primary outcome in the trial was improvement in the score between ED discharge and 1 week later. Secondary outcomes included pain intensity 1 week and 3 months after ED discharge, as measured on a 4-point descriptive scale (severe, moderate, mild, and none). All patients were given 20 tablets of naproxen 500 mg, to be taken twice a day as needed for low back pain. Additionally, patients were randomized to receive either 28 tablets of diazepam 5 mg or identical placebo, to be received as 1 or 2 tablets every 12 hours as needed for low back pain. All patients received a standardized 10-minute low back pain educational session before discharge. Using a between-group mean difference of 5 Roland-Morris Disability Questionnaire points, a previously validated threshold for clinical significance, we calculated the need for at least 100 patients with primary outcome data.
Results:
Enrollment began in June 2015 and continued for 9 months. Five hundred forty-five patients were screened for eligibility. One hundred fourteen patients met selection criteria and were randomized. Baseline demographic characteristics were not substantially different between the 2 groups. One hundred twelve patients (98%) provided 1-week outcome data. The mean Roland-Morris Disability Questionnaire score of patients randomized to naproxen+diazepam improved by 11 (95% confidence interval [CI] 9 to 13), as did the mean score of patients randomized to naproxen+placebo (11; 95% CI 8 to 13). At 1-week follow-up, 18 of 57 diazepam patients (32%; 95% CI 21% to 45%) reported moderate or severe low back pain versus 12 of 55 placebo patients (22%; 95% CI 13% to 35%). At 3-month follow-up, 6 of 50 diazepam patients (12%; 95% CI 5% to 24%) reported moderate or severe low back pain versus 5 of 53 placebo patients (9%; 95% CI 4% to 21%). Adverse events were reported by 12 of 57 diazepam patients (21%; 95% CI 12% to 33%) and 8 of 55 placebo patients (15%; 95% CI 7% to 26%).
Conclusion:
Among ED patients with acute, nontraumatic, nonradicular low back pain, naproxen+diazepam did not improve functional outcomes or pain compared with naproxen+placebo 1 week and 3 months after ED discharge.
More Related Videos
 06:28
Biomechanical Changes Related to Low Back Pain: An Innovative Tool for Movement Pattern Assessment and Treatment Evaluation in Rehabilitation
Published on: December 13, 2024
 04:42
Treating Low Back Pain in Failed Back Surgery Patients with Multicolumn-lead Spinal Cord Stimulation
Published on: June 26, 2018
Related Concept Videos
 01:29
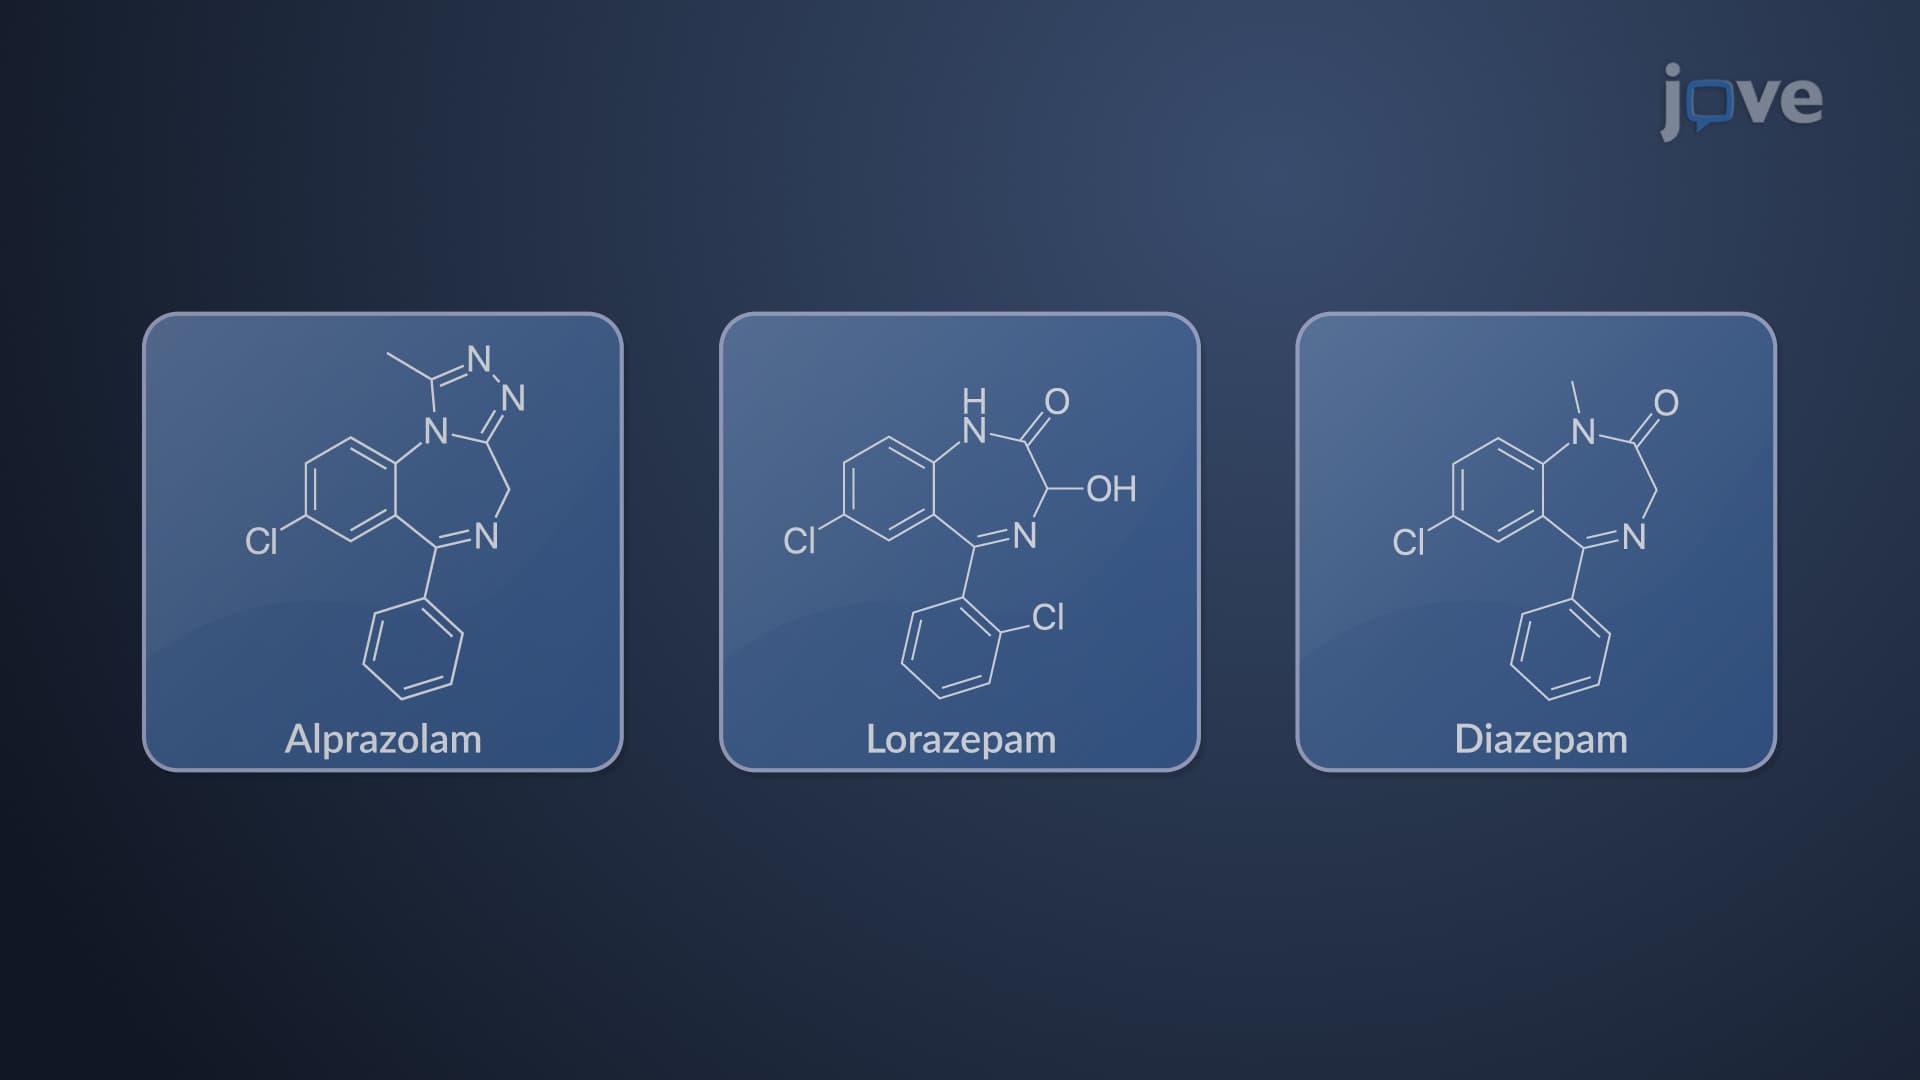
Anxiolytic Drugs: Benzodiazepines and Buspirone
 01:24
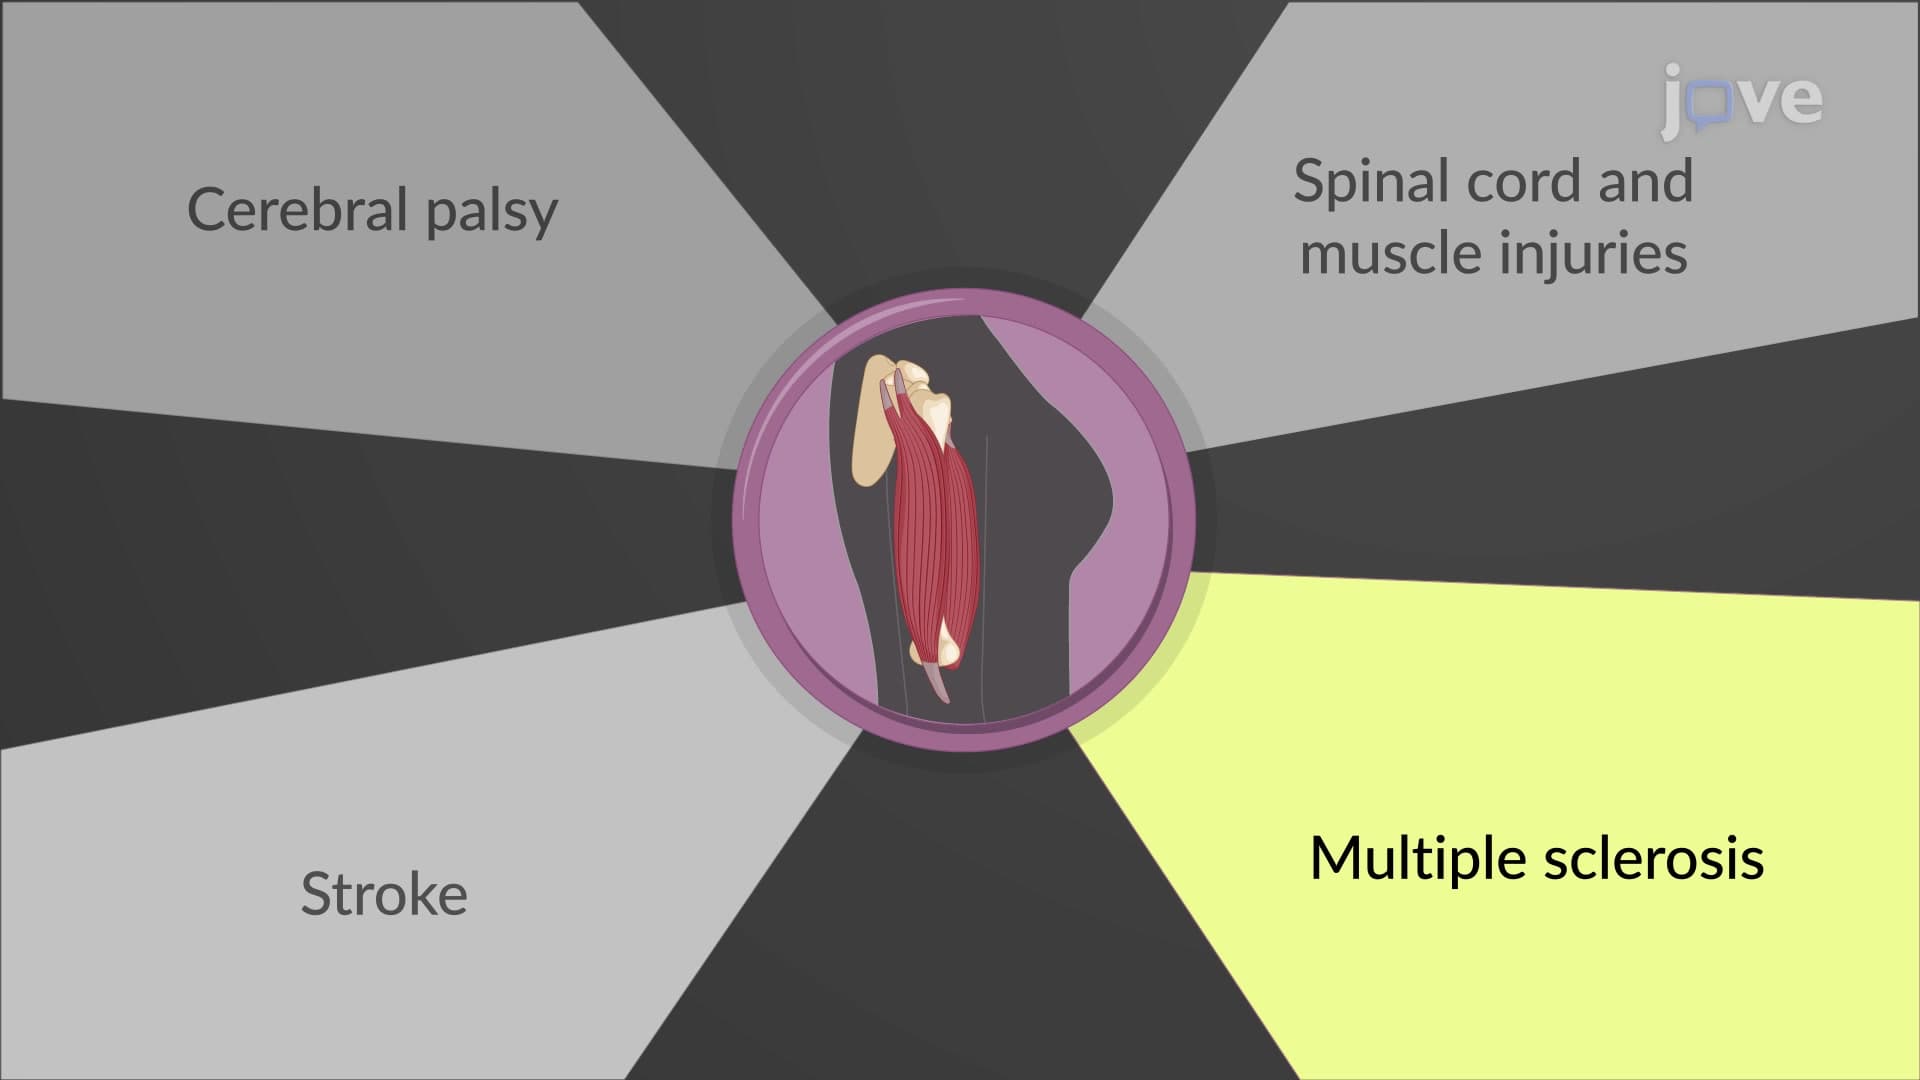
Centrally Acting Muscle Relaxants: Therapeutic Uses
Centrally acting drugs are classified into spasmolytic and antispasmodic drugs. Spasmolytic drugs such as baclofen, diazepam, and tizanidine inhibit spinal motor neurons and decrease muscle tone. Spasmolytic drugs are administered for severe and chronic spasms due to multiple sclerosis, cerebral palsy, stroke, and spinal cord and muscle injuries. However,...
 01:19
Sedatives and Hypnotics Drugs: Benzodiazepines
Benzodiazepines work by enhancing the effects of the inhibitory neurotransmitter GABA. They bind to the GABAA receptor, increasing its affinity for GABA, which opens chloride...
 01:09
Peripherally and Centrally Acting Muscle Relaxants: A Comparison
Centrally acting muscle relaxants can be further divided into spasmolytic and antispasmodic drugs. Spasmolytic...
 01:14
CNS Depressants: Barbiturates and Benzodiazepines
 01:25
Analgesia and Pain Management