Related Experiment Video
Updated: Mar 7, 2026

Author Spotlight: An Automated Method for Assessing Visual Acuity in Infants and Toddlers Using an Eye-Tracking System
Published on: March 17, 2023
Similarities and differences between behavioral and electrophysiological visual acuity thresholds in healthy infants
Claudia Polevoy1,2, Gina Muckle3,4, Jean R Séguin1,5
1Research Center, CHU Sainte-Justine, Montreal, Canada.

Insights
Visual acuity in infants aged 6-10 months differs between sweep visual evoked potentials (sVEP) and Teller acuity cards (TAC). The agreement depends on subjective acuity, not age, with TAC exceeding sVEP at high acuity levels.
Area of Science:
- Developmental Ophthalmology
- Visual Neuroscience
- Pediatric Optometry
Background:
- Correlation between behavioral and electrophysiological methods for visual acuity estimation is established in adults and older children.
- This relationship is less understood in infants, particularly during the second half of the first year of life.
- Previous research suggests age and subjective acuity influence the agreement between methods.
Purpose of the Study:
- To compare visual acuity thresholds obtained using Teller acuity cards (TAC) and sweep visual evoked potentials (sVEP) in healthy infants.
- To investigate the influence of age and subjective acuity on the agreement between TAC and sVEP in infants aged 6-10 months.
Main Methods:
- Visual acuity was assessed in 61 healthy infants (6-10 months old) using TAC and sVEP.
- TAC stimuli ranged from 0.31 to 38 cycles per degree (cpd); sVEP stimuli ranged from 13.5 to 1 cpd.
- Acuity thresholds were determined by experimenter observation for TAC and linear regression for sVEP.
Main Results:
- sVEP acuity thresholds (8.97 ± 2.52 cpd) were significantly higher than TAC scores (5.58 ± 2.95 cpd) in the overall sample.
- 64% of infants showed a difference within one octave between the two methods.
- Agreement between TAC and sVEP was not dependent on age but on subjective acuity; TAC exceeded sVEP at high subjective acuity levels (>10 cpd).
Conclusions:
- The superiority of sVEP over TAC in visual acuity estimation was observed in infants with low to moderate subjective acuity.
- The discrepancy between sVEP and TAC diminished as subjective acuity increased.
- Subjective acuity, rather than age, is the key factor influencing the agreement between behavioral (TAC) and electrophysiological (sVEP) visual acuity measures in infants.
Purpose:
Behavioral and electrophysiological methods for visual acuity estimation typically correlate well in children and adult populations, but this relationship remains unclear in infants, particularly during the second half of the first year of life. It has been suggested that the agreement between both methods mostly relies on age and/or subjective acuity factors. The present study aimed at comparing acuity thresholds obtained with both approaches in a sample of healthy infants in a relatively narrow age range, that is 6-10 months old.
Methods:
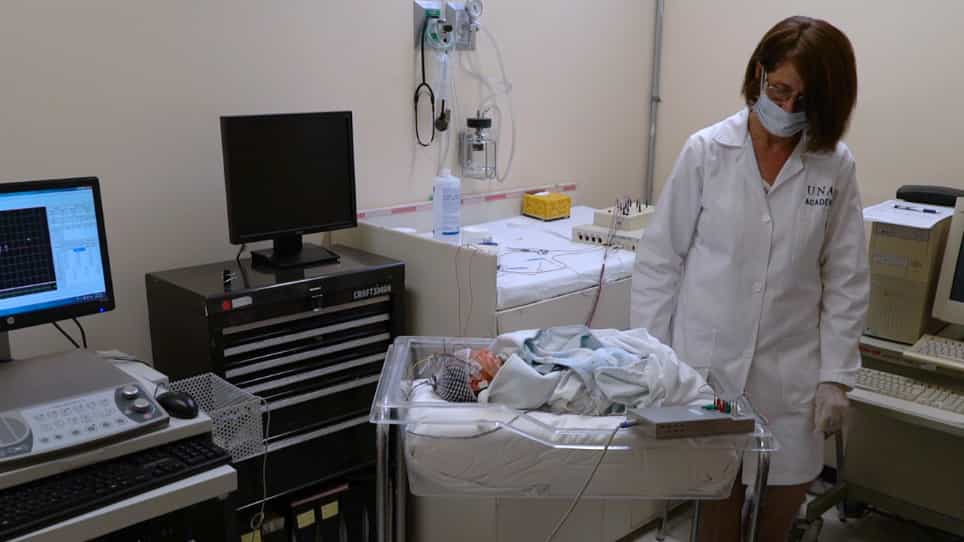
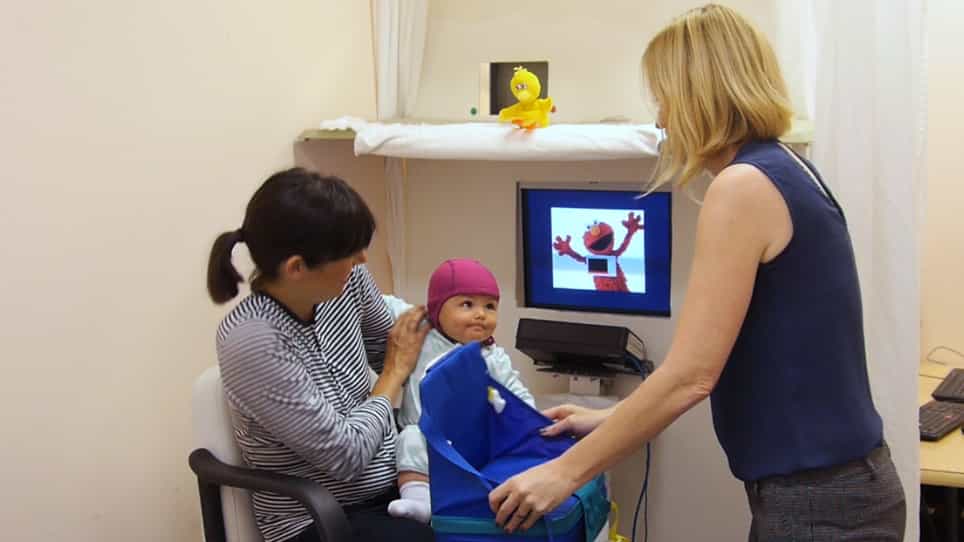
Acuity thresholds were assessed in 61 healthy infants aged between 6 and 10 months using the Teller acuity cards (TAC) and sweep visual evoked potentials (sVEP). The TAC stimuli (stationary vertical gratings displayed on laminated cards) ranged from 0.31 to 38 cycles per degree (cpd). The TAC acuity threshold was estimated according to the highest spatial frequency scored by the experimenter as seen by the infant. The sVEP stimuli (high-contrast vertical gratings counter-phased at 12 reversals/s) ranged from 13.5 to 1 cpd. sVEP were recorded at Oz and acuity threshold was estimated using regression linear fitting.
Results:
Considering the entire sample, sVEP acuity thresholds (8.97 ± 2.52 cpd) were significantly better than TAC scores (5.58 ± 2.95 cpd), although the difference was within 1 octave for 64% of the infants. Neither Pearson nor intra-class correlations between the two methods were significant (0.18 and 0.03, respectively). While age at assessment was not related to any dependent variable (TAC, sVEP, sVEP-TAC difference score), subjective (behavioral) acuity was found to underlie the difference between the two methods. The difference between sVEP and TAC scores decreased as a function of subjective acuity, and at the highest subjective acuity level (>10 cpd), TAC acuity slightly exceeded sVEP acuity.
Conclusions:
The superiority of sVEP acuity often reported in the literature was evident in our infant sample when subjective acuity (TAC) was low or moderate, but not when it was high (>10 cpd). The relationship between the two estimation methods was not dependent on age, but on subjective acuity.