Membrane pressures predict clotting of pediatric continuous renal replacement therapy circuits
Related Experiment Video
Updated: Mar 7, 2026
Microfluidic Flow Chambers Using Reconstituted Blood to Model Hemostasis and Platelet Transfusion In Vitro
Published on: March 19, 2016
Aadil Kakajiwala1,2, Thomas Jemielita3, John Z Hughes4
1Department of Pediatrics, Division of Nephrology, The Children's Hospital of Philadelphia, Philadelphia, PA, USA. kakajiwala_a@kids.wustl.edu.

Insights
Continuous renal replacement therapy (CRRT) circuit clotting is common in children. Elevated circuit pressures increase clotting risk, while higher activated clotting times (ACT) may reduce it, suggesting strategies to optimize ACT for CRRT longevity.
Area of Science:
- Pediatric Nephrology
- Critical Care Medicine
- Biomedical Engineering
Background:
- Circuit clotting in continuous renal replacement therapy (CRRT) compromises patient clearance and increases resource utilization.
- Identifying factors contributing to premature CRRT circuit clotting in pediatric patients is crucial for improving treatment efficacy.
Purpose of the Study:
- To investigate the factors associated with premature clotting of CRRT circuits in a pediatric cohort.
- To determine the impact of anticoagulation type, circuit pressures, and activated clotting time (ACT) on CRRT circuit lifespan.
Main Methods:
- A retrospective analysis of 79 CRRT circuits in 26 pediatric patients was conducted.
- Data collected included hourly pressure, flow, fluid removal rates, ACT, and circuit ionized calcium levels.
- Cox and logistic regression models were employed to identify predictors of premature circuit clotting.
Main Results:
- 64.6% of CRRT circuits experienced premature clotting, with a median circuit duration of 18.25 hours.
- Heparin anticoagulation was associated with lower premature clotting rates compared to citrate.
- Increased transmembrane and filter pressures were independently linked to a higher risk of circuit clotting.
Conclusions:
- Elevated transmembrane and filter pressures are significant risk factors for CRRT circuit clotting in children.
- Maintaining higher activated clotting times (ACT) may be a strategy to reduce circuit clotting.
- Further research is needed to identify additional factors that can extend CRRT circuit longevity in pediatric populations.
Background:
Clotting of continuous renal replacement therapy (CRRT) circuits leads to inadequate clearance, decreased ultrafiltration, and increased resource use. We identified factors associated with premature clotting of circuits during CRRT in children.
Methods:
In a retrospective cohort of 26 children (median age 11.8 years) receiving 79 CRRT circuits (51 heparin, 22 citrate, 6 using no anticoagulation), we captured hourly pressure, flow, and fluid removal rates along with all activated clotting time (ACT) and circuit ionized calcium measurements. Cox and logistic regression models were used to examine factors associated with premature circuit clotting before the scheduled 3-day circuit change.
Results:
Of the 79 circuits, 51 (64.6%) underwent unplanned filter change due to filter clotting (median duration 18.25 h, interquartile range [IQR] 9.25, 33.5 h), and 28 (35.4%) underwent scheduled change (median duration 66 h, IQR 61.00, 69.00 h). Patient age, catheter size and location, blood flow rate, and the percentage of pre-filter replacement fluid were not associated with premature clotting. Heparin circuits were less likely than citrate circuits to clot prematurely. Each 1-mmHg increase in the transmembrane or filter pressure was independently associated with a 1.5% (95% confidence interval [CI] 1.0-2.0%) and 1.5% (95% CI 1.0-2.0%) higher risk of clotting, respectively. Higher ACTs were associated with lower transmembrane (p = 0.03) and filter (p < 0.001) pressures.
Conclusions:
The majority of circuits in our cohort were subject to unplanned filter changes. Elevated transmembrane and filter pressures were associated with clotting. Our results suggest that maintaining higher ACT may decrease the risk of circuit clotting. Larger studies are needed to examine other factors that may prolong the lifespan of the CRRT circuit in this high-risk population.
More Related Videos

Related Concept Videos
 01:30
Continuous Renal Replacement Therapy
 01:26
Extracorporeal Removal of Drugs: Continuous Renal Replacement Therapy
 01:18
Fluid Movement Between Compartments
 01:20
Acute Kidney Injury V: Interprofessional Care
 01:26
Glomerular Filtration: Net Filtration Pressure
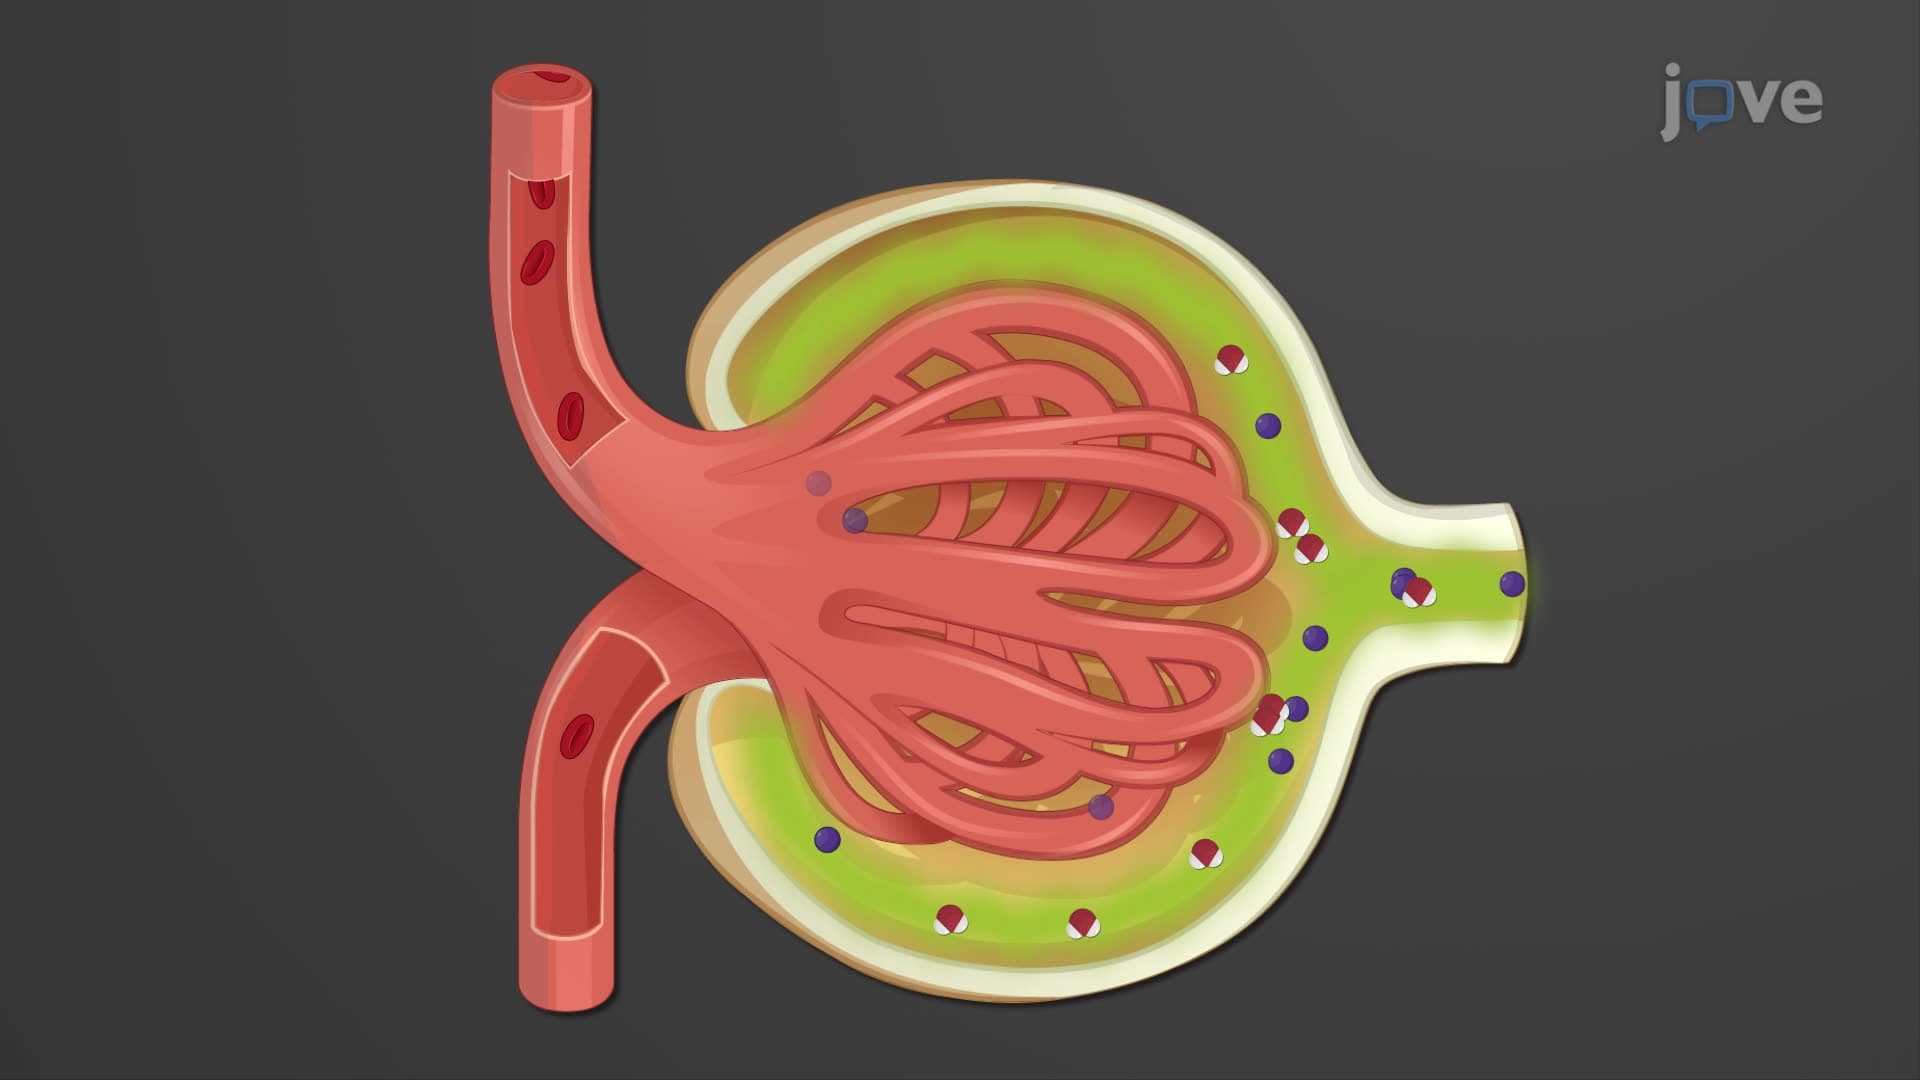
GBHP, with an average value of 55 mmHg, promotes filtration by pushing water and solutes through the filtration membrane. This is balanced by two opposing forces: CHP, a "back pressure" exerted against the filtration membrane by fluid already in the capsular space and renal...
 01:24
Hemodialysis II: Procedure and Complications