Related Experiment Video
Updated: Mar 6, 2026
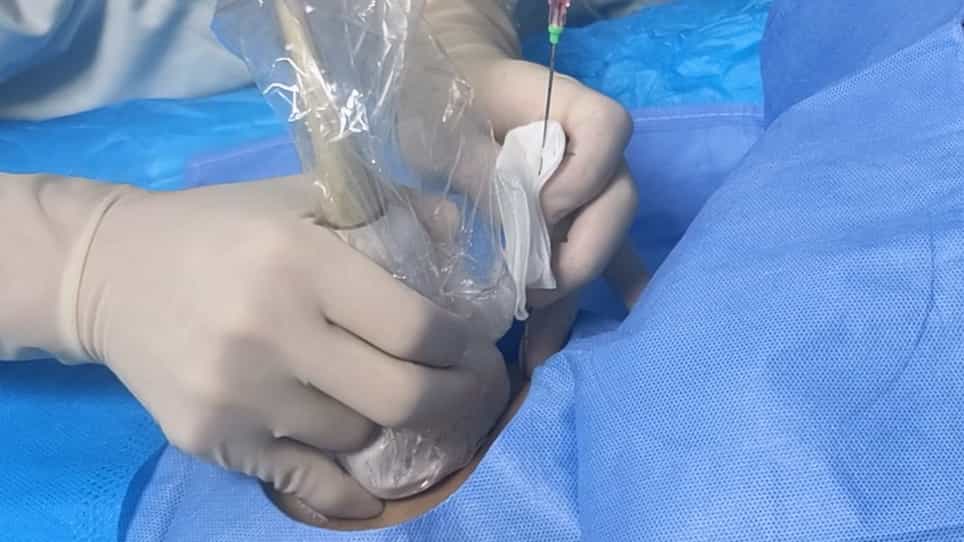

A Two-Step Method for Percutaneous Transhepatic Choledochoscopic Lithotomy
Published on: September 13, 2022
Percutaneous cholecystostomy: A curative treatment modality forelderly and high ASA score acute cholecystitis
Hüseyin Kerem Tolan1, Aslıhan Semiz Oysu, Fatih Başak
1Department of General Surgery, Ümraniye Training and Research Hospital, İstanbul-Turkey. mdkeremtolan@gmail.com.

Insights
Percutaneous cholecystostomy (PC) offers a safe treatment for elderly patients with acute cholecystitis (AC) when surgery is too risky. This gallbladder drainage procedure allows for interval cholecystectomy with a low complication rate.
Area of Science:
- Interventional Radiology
- Gastroenterology
- Surgical Emergency Management
Background:
- Acute cholecystitis (AC) is a common surgical emergency.
- Laparoscopic cholecystectomy (LC) is the optimal treatment for AC.
- High-risk elderly patients with comorbidities may not tolerate LC, necessitating alternative treatments like percutaneous cholecystostomy (PC).
Purpose of the Study:
- To evaluate the safety and efficacy of percutaneous cholecystostomy (PC) in high-risk elderly patients with acute cholecystitis (AC).
- To assess the outcomes of PC, including complication rates and the need for subsequent procedures.
Main Methods:
- Retrospective review of 40 consecutive patients undergoing PC for AC between January 2011 and January 2014.
- Diagnosis and severity assessment of AC based on Tokyo Guidelines.
- PC performed under local anesthesia with ultrasonographic guidance by a single interventional radiologist.
Main Results:
- 100% success rate for PC in 40 high-risk elderly patients (median age 70.5 years).
- A low complication rate of 2.5% was observed.
- 40% of patients underwent subsequent surgery after PC drain removal, with an 18.8% conversion rate to open surgery from LC.
Conclusions:
- Percutaneous cholecystostomy (PC) is a safe and effective alternative for managing acute cholecystitis (AC) in elderly patients who are poor surgical candidates.
- PC provides initial infection control and gallbladder drainage, enabling delayed cholecystectomy under improved physiological conditions.
- Subsequent laparoscopic cholecystectomy after PC is feasible with an acceptable conversion rate.
Background:
Acute cholecystitis (AC) is a common emergency seen by general surgeons. Optimal treatment is laparoscopic cholecystectomy (LC); however, in cases where surgery cannot be performed due to high risk of morbidity and mortality, such as in elderly patients with comorbid diseases, other treatment modalities may be used. Percutaneous cholecystostomy (PC) is one alternative method to treat AC. PC can be used to provide drainage of the gall bladder and control infection. Subsequently, interval cholecystectomy can be performed when there are better conditions. Presently described is experience and results with PC in high risk, elderly patients with AC.
Methods:
Medical records of all consecutive patients who underwent PC between January 2011 and January 2014 were identified. Tokyo Guidelines were used for definitive diagnosis and severity assessment of AC. Senior surgeon elected to perform PC based on higher risk-benefit ratio due to comorbidity, age, or duration of symptoms. All PC procedures were performed by the same interventional radiologist under local anesthesia with ultrasonographic guidance.
Results:
Total of 40 PC procedures were performed during the study period. Of those, 22 (55%) were male and 18 were (45%) were female, with median age of 70.5 years (range: 52-87 years). All of the patients had American Society of Anesthesiologists classification of either 3 or 4. Success rate of PC was 100% with complication rate of 2.5% (n=1). One patient was operated on shortly after PC procedure due to bile peritonitis complication. PC drains were kept in place for 6 weeks. Total of 16 patients (40%) had surgery following removal of PC drain. In 3 (18.8%) cases, conversion from LC was required. Remaining 23 (57.5%) patients did not have subsequent operation after drain removal. No disease recurrence was observed in follow-up.
Conclusion:
When elderly patients present in emergency setting with AC and LC cannot be performed due to comorbid disease or poor general condition, PC can be performed safely. After removal of PC drain, LC may be performed with acceptable conversion rate of 18.8%.
Related Concept Videos
 01:26
Endoscopic Procedures V: ERCP
Patient...
 01:29
Chronic Pancreatitis II: Collaborative Care
Assessment: