Related Experiment Video
Updated: Mar 6, 2026

A Modified Two Kidney One Clip Mouse Model of Renin Regulation in Renal Artery Stenosis
Published on: October 26, 2020
Hypertension's 3 Dilemmas and 3 Solutions: Pharmacology of the Kidney in Hypertension
1Division of Clinical Pharmacology (Retired), University of Texas Southwestern Medical School (Retired), Bonita Springs, FL.

Insights
Effective hypertension management requires addressing dietary sodium and arteriolar hypertrophy. Minoxidil, a potent drug, should be reconsidered for treating high blood pressure (HBP) despite its Black Box warning.
Area of Science:
- Cardiovascular Medicine
- Nephrology
- Pharmacology
Background:
- Hypertension management faces challenges with current treatment goals and drug efficacy.
- A significant portion of hypertensive patients remain uncontrolled, exceeding 140/90 mm Hg.
- Minoxidil, a potent antihypertensive, is underutilized due to FDA Black Box warnings.
Purpose of the Study:
- To review the safety and efficacy of minoxidil for hypertension.
- To emphasize the role of dietary sodium in hypertension.
- To explore the prevention and reversal of arteriolar hypertrophy in hypertension.
Main Methods:
- Review of minoxidil's pharmacological profile and clinical data.
- Analysis of the impact of dietary sodium on blood pressure.
- Examination of arteriolar hypertrophy as a mechanism in hypertension progression.
Main Results:
- Minoxidil demonstrates a favorable toxicity profile when used appropriately.
- Dietary sodium reduction is a fundamental strategy for managing hypertension.
- Arteriolar hypertrophy is a key mechanism in worsening hypertension, potentially reversible.
Conclusions:
- Revisiting minoxidil's use could address uncontrolled hypertension.
- Focusing on sodium intake and arteriolar hypertrophy offers a path to better blood pressure control.
- Preventing or reversing arteriolar hypertrophy is crucial for long-term hypertension management.
Abstract:
The Hypertension Community has 3 conflicting dilemmas: a goal systolic pressure of 120 mm Hg or less (the SPRINT Trials), 40% of our 60,000,000 hypertensives still sustain blood pressures above 140/90 mm Hg, and our most potent antihypertensive drug minoxidil sits on the sidelines, imprisoned in the Food and Drug Administration's Black Box designation. My solutions to these dilemmas are: (1) review of the facts of our most potent antihypertensive drug minoxidil which is essentially free of toxicity, (2) treatment focus on the fundamental cause of high blood pressure, that is excess dietary sodium and, (3) prevention of, and/or reversal of, the fundamental mechanism of worsening hypertension, arteriolar hypertrophy.
Summary:
The Hypertension Community has 3 conflicting dilemmas: a goal systolic pressure of 120 mm Hg or less (the SPRINT Trials), 40% of our 60,000,000 hypertensives still sustain blood pressures above 140/90 mm Hg, and our most potent antihypertensive drug minoxidil sits on the sidelines, imprisoned in the Food and Drug Administration's Black Box designation. My solutions to these dilemmas are: (1) review of the facts of our most potent antihypertensive drug minoxidil which is essentially free of toxicity, (2) treatment focus on the fundamental cause of high blood pressure (HBP) and excess dietary sodium and, (3) prevention of, and/or reversal of, the fundamental mechanism of worsening hypertension, arteriolar hypertrophy. My focus at UT Southwestern in Dallas was on extremely severely hypertensive patients with a quantifiable, measurable complication of HBP, progression of nephrosclerotic damage to kidneys. This model had the greatest likelihood of exposing fundamental disregulatory mechanisms in hypertensive patients (which it did) and the potential for study of the most relevant antihypertensive drug interactions to achieve optimal blood pressure control (which it did). By maintaining diastolic pressures at 80 mm Hg or less in the first National Institutes of Health-supported, long-term randomized clinical trial to save the kidneys, the bases for a fundamental blood pressure support mechanism (arteriolar hypertrophy) was illuminated but not fully described until now. This fundamental hypertensinogenic mechanism results from HBP but with time and severity, becomes its own raison d'être. I am now aged 84 years. As a result of a stroke 20 years ago, which caused permanent double vision, and because of poor blood pressure control with triple therapy, I started using minoxidil 5 mg/d along with atenolol and occasional furosemide. Now, along with some dietary salt restriction, my resting blood pressure is 110/65-125/75 and, despite >30 years history of HBP, I have no retinal arteriolar hypertrophy nor arcus senilis (Dr. Schwartz-U. of Miami) which is almost universally present at this age. Yes, prevention of, or reversal of, arteriolar hypertrophy should be a central focus of HBP treatment. I simply wish to share a bit of accumulated wisdom that might be of use to others.
More Related Videos


Related Concept Videos
 01:28
Antihypertensive Drugs: Potassium-Sparing Diuretics
 01:26
Heart Failure Drugs: Inhibitors of Renin-Angiotensin System
 01:16
Antihypertensive Drugs: Action of Diuretics
 01:22
Heart Failure Drugs: Diuretics
 01:13
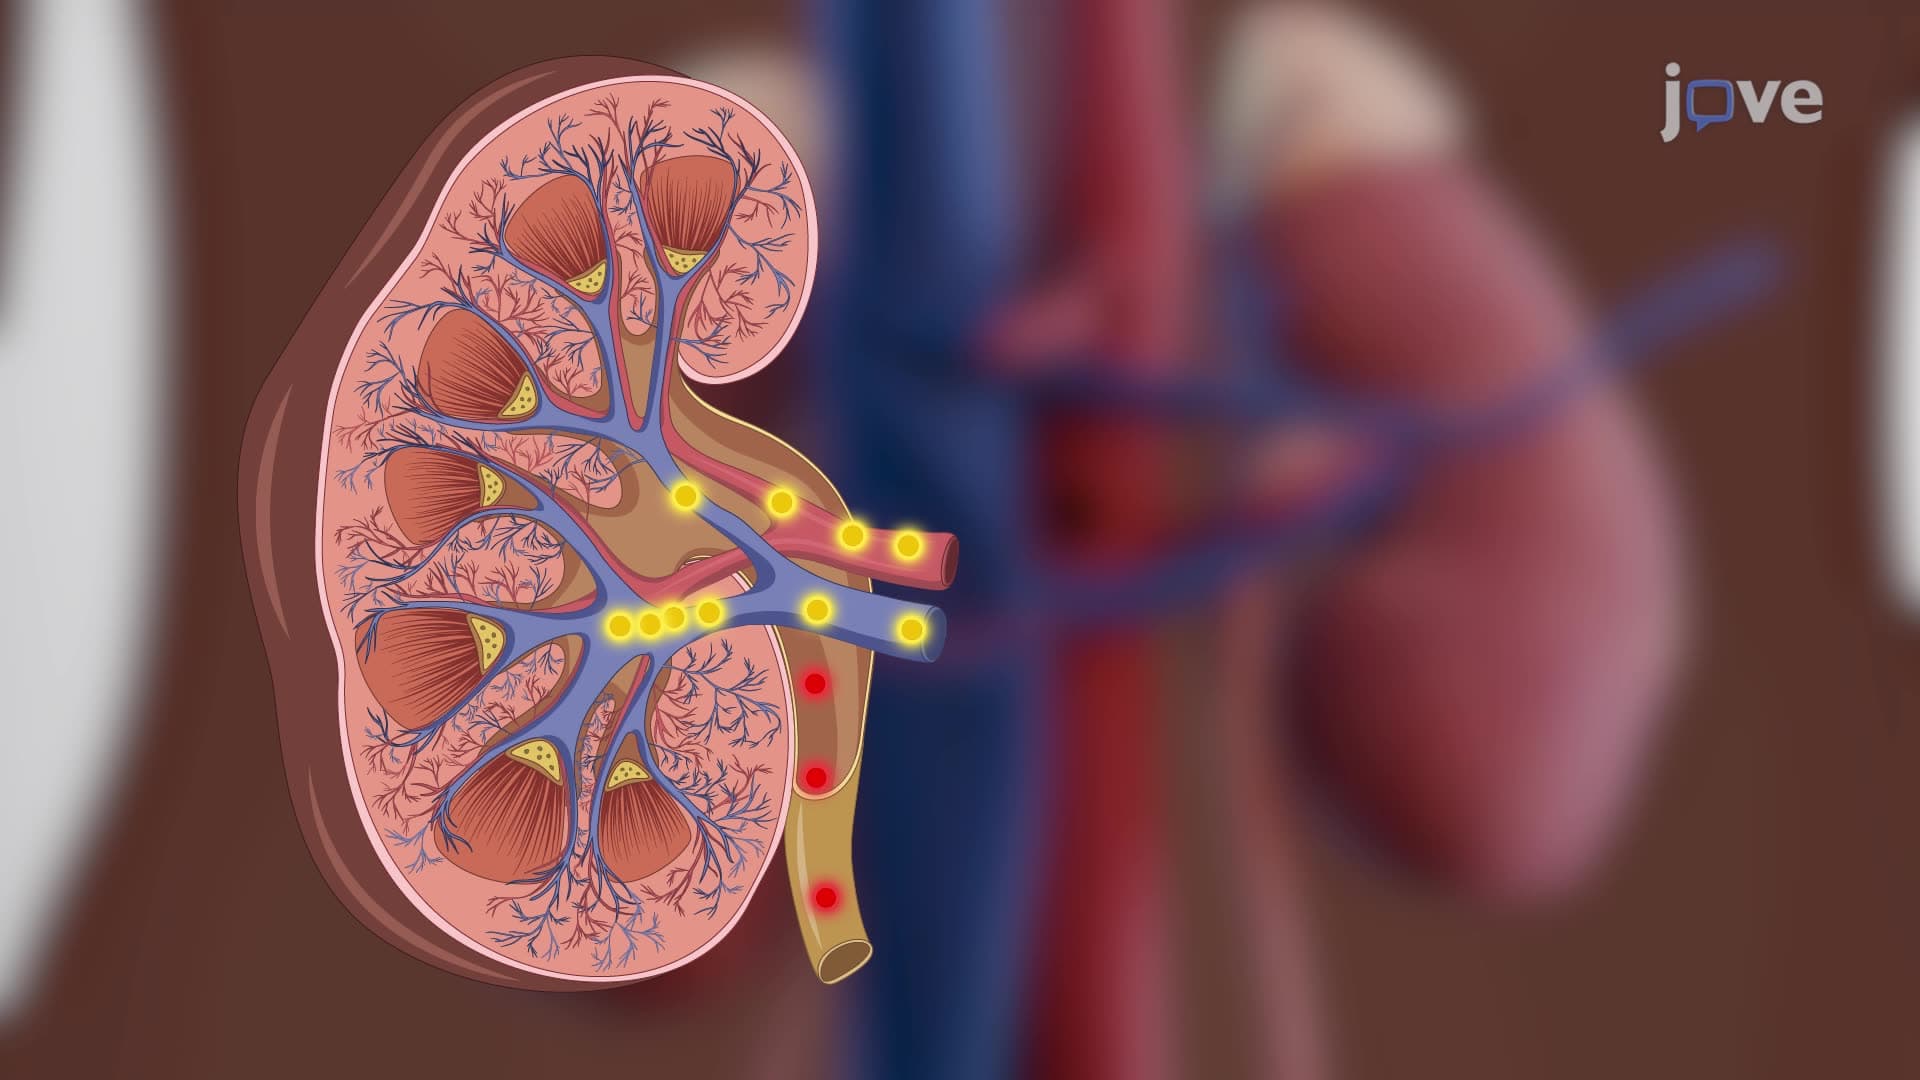
Introduction to Urinary System
The kidneys are bean-shaped organs located in the retroperitoneal space, on either side of the vertebral column, between the T12 and L3 vertebrae. They are partially protected by the rib cage and surrounded by perirenal fat, which provides cushioning. They are responsible for urine formation and play critical roles in regulating blood pressure, electrolyte levels, and hormone production. The ureters...
 01:25
Antihypertensive Drugs: Direct Renin Inhibitors