
Anastomotic loop between common hepatic artery and gastroduodenal artery in coexistence with an aberrant right
K Natsis1, M Piagkou2, T Stamatopoulos
1Department of Anatomy, School of Medicine, Faculty of Health Sciences, Aristotle University of Thessaloniki, Thessaloniki, Greece.

Anatomical variations of the hepatic arteries are not uncommon. The anomalous hepatic arterial supply is of paramount importance in hepatobiliary, pancreatic or liver transplantation and in laparoscopic surgery. We describe an unusual case of a 66-year-old Greek male cadaver, where a rare anastomosis (in the form of an enlarged arterial loop, 4.84 mm in diameter) between the common hepatic artery (6.42 mm) and the gastroduodenal artery (GDA) (4.82 mm) coexisted with an aberrant right hepatic artery (ARHA) (6.38 mm) originating from the superior mesenteric artery. The proper hepatic artery was absent. The ARHA followed a route posterior to the portal vein and the common hepatic duct, entering the liver and supplying the right hepatic segment. A hypoplastic right gastric artery emanated from the GDA. Our case report highlights the combined variations of hepatic arteries and possible anastomoses emphasizing that a thorough knowledge of the classic and variable hepatic arterial anatomy are mandatory for surgeons and radiologists performing hepatic surgery and arteriography to avoid potential iatrogenic injuries in hepatobiliary and pancreas area and further medico-legal implications.
Anatomical variations of the hepatic arteries are not uncommon. The anomalous hepatic arterial supply is of paramount importance in hepatobiliary, pancreatic or liver transplantation and in laparoscopic surgery. We describe an unusual case of a 66-year-old Greek male cadaver, where a rare anastomosis (in the form of an enlarged arterial loop, 4.84 mm in diameter) between the common hepatic artery (6.42 mm) and the gastroduodenal artery (GDA) (4.82 mm) coexisted with an aberrant right hepatic artery (ARHA) (6.38 mm) originating from the superior mesenteric artery. The proper hepatic artery was absent. The ARHA followed a route posterior to the portal vein and the common hepatic duct, entering the liver and supplying the right hepatic segment. A hypoplastic right gastric artery emanated from the GDA. Our case report highlights the combined variations of hepatic arteries and possible anastomoses emphasizing that a thorough knowledge of the classic and variable hepatic arterial anatomy are mandatory for surgeons and radiologists performing hepatic surgery and arteriography to avoid potential iatrogenic injuries in hepatobiliary and pancreas area and further medico-legal implications.
Related Concept Videos
 01:25
Abdominal Aorta
The celiac trunk, a singular artery, divides into the left gastric artery, which...
 01:19
Anastomoses
Anastomoses can be formed at arterial, venous, and lymphatic vessels.
Arterial Anastomosis: These occur between arteries. They...
 01:21
Hepatic Portal System
At its core, the hepatic portal vein is the result of a confluence of the superior and inferior mesenteric veins along with the splenic vein. Each of these veins has a unique role. The superior mesenteric vein is...
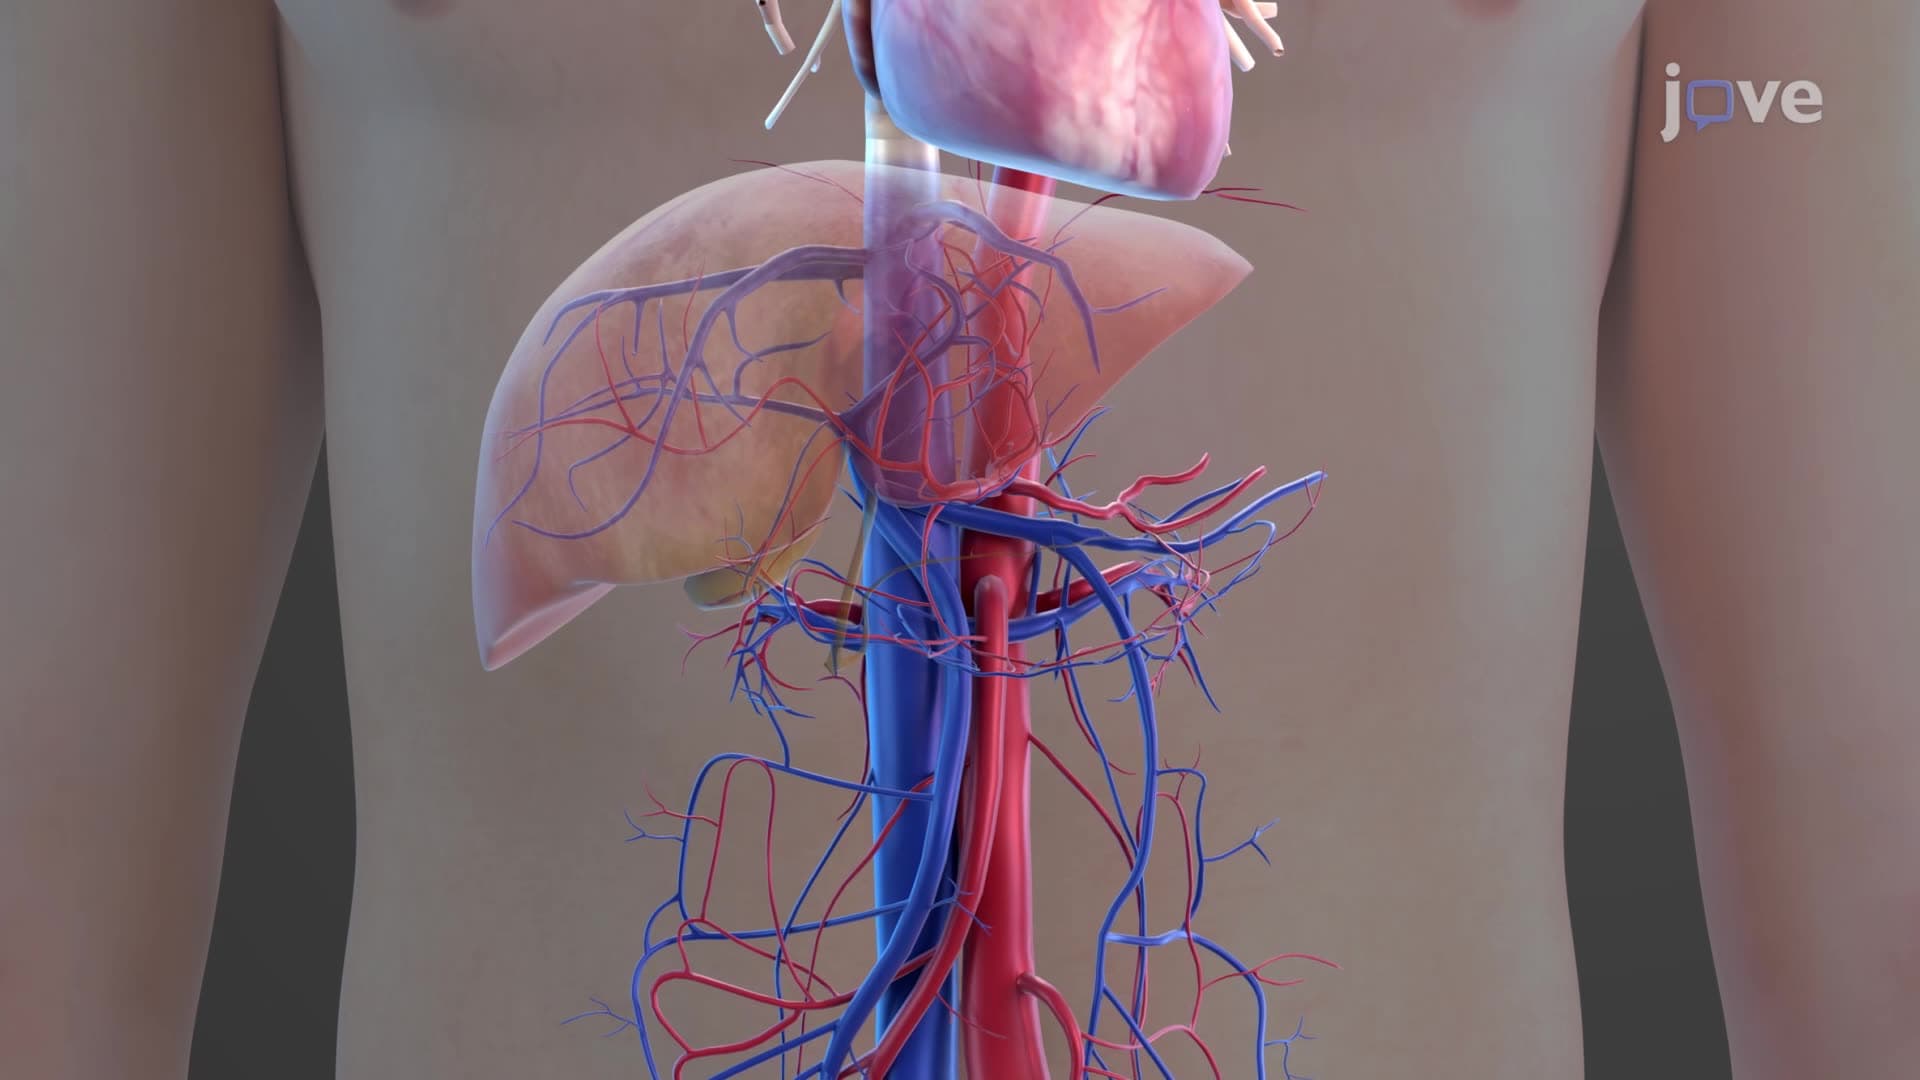 01:16
Blood Supply to the Digestive System
Blood Supply to the Digestive System: The splanchnic circulation involves three main arteries: the celiac artery (also known as the celiac trunk) and the superior and inferior mesenteric...
 01:17
Gross Anatomy of the Liver
Located under the diaphragm, the liver is almost entirely ensconced within the rib cage, providing it with substantial protection. Except for the superior most bare area, the liver's surface is...