Sepsis patients in the emergency department: stratification using the Clinical Impression Score, Predisposition, Infection, Response and Organ dysfunction score or quick Sequential Organ Failure Assessment score?
Related Experiment Video
Updated: Mar 5, 2026
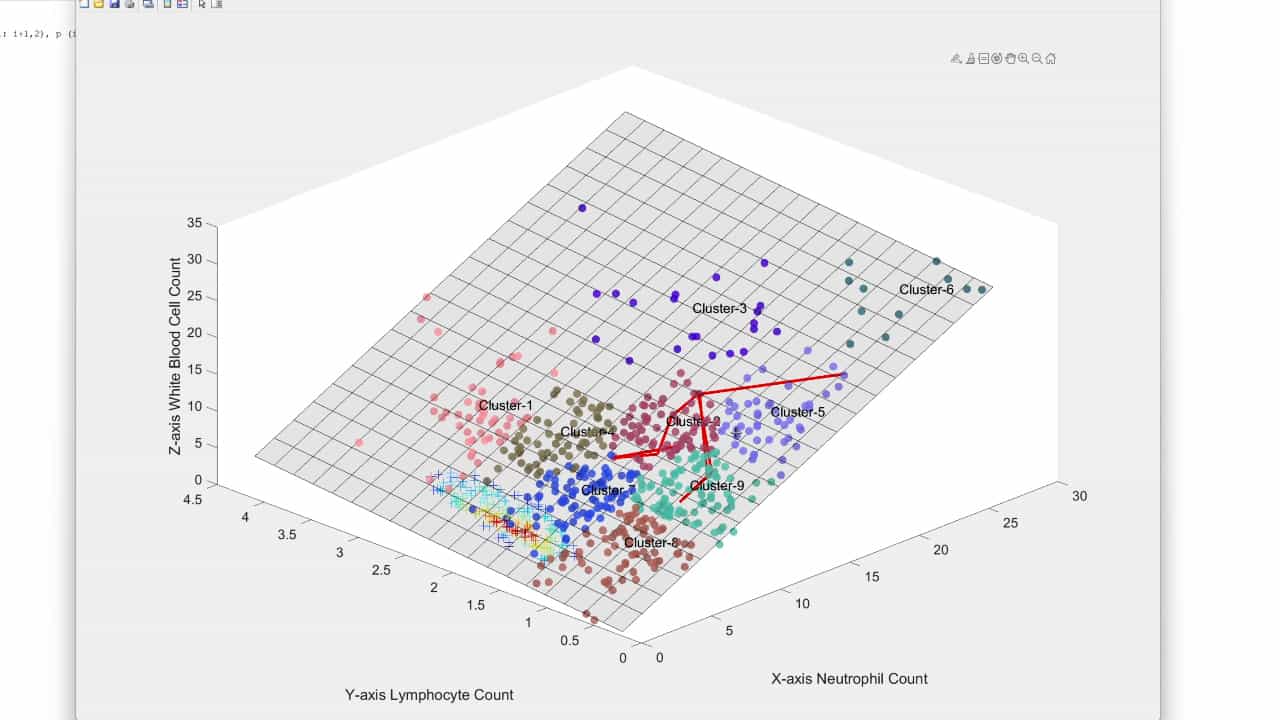
A Data-Driven Approach to Quantifying Immune States in Sepsis
Published on: February 7, 2025
Vincent M Quinten1, Matijs van Meurs2,3, Anna E Wolffensperger1
1Departments of Emergency Medicine.

Objective:
The aim of this study was to compare the stratification of sepsis patients in the emergency department (ED) for ICU admission and mortality using the Predisposition, Infection, Response and Organ dysfunction (PIRO) and quick Sequential Organ Failure Assessment (qSOFA) scores with clinical judgement assessed by the ED staff.
Patients And Methods:
This was a prospective observational study in the ED of a tertiary care teaching hospital. Adult nontrauma patients with suspected infection and at least two Systemic Inflammatory Response Syndrome criteria were included. The primary outcome was direct ED to ICU admission. The secondary outcomes were in-hospital, 28-day and 6-month mortality, indirect ICU admission and length of stay. Clinical judgement was recorded using the Clinical Impression Scores (CIS), appraised by a nurse and the attending physician. The PIRO and qSOFA scores were calculated from medical records.
Results:
We included 193 patients: 103 presented with sepsis, 81 with severe sepsis and nine with septic shock. Fifteen patients required direct ICU admission. The CIS scores of nurse [area under the curve (AUC)=0.896] and the attending physician (AUC=0.861), in conjunction with PIRO (AUC=0.876) and qSOFA scores (AUC=0.849), predicted direct ICU admission. The CIS scores did not predict any of the mortality endpoints. The PIRO score predicted in-hospital (AUC=0.764), 28-day (AUC=0.784) and 6-month mortality (AUC=0.695). The qSOFA score also predicted in-hospital (AUC=0.823), 28-day (AUC=0.848) and 6-month mortality (AUC=0.620).
Conclusion:
Clinical judgement is a fast and reliable method to stratify between ICU and general ward admission in ED patients with sepsis. The PIRO and qSOFA scores do not add value to this stratification, but perform better on the prediction of mortality. In sepsis patients, therefore, the principle of 'treat first what kills first' can be supplemented with 'judge first and calculate later'.


Related Concept Videos
 01:30
Pneumonia III: Complications and Assessment
 01:21
Methods of Documentation III: PIE
 01:28
Pneumonia IV: Management
Bacterial Pneumonia Treatment
For bacterial pneumonia, antibiotics serve as the cornerstone of therapy. Initial treatment often begins with empirical antibiotics, tailored to the anticipated causative organism and adjusted based on culture results. Key antibiotic choices include:
 01:14
SBAR II: Application of SBAR
SBAR Report from a Nurse to a Health Care Provider
S: "Hello, Dr. Smith. This is Jane, RN, from the Med Surg unit. I am calling to tell you about Ms. White in Room 210, who is experiencing increased pain and redness at her incision site. Her recent...
 01:29
Pulmonary Embolism II: Diagnostic Studies and Interprofessional Care
 01:29
Pulmonary Embolism I: Introduction