Related Experiment Video
Updated: Sep 21, 2026

Benefits of Cardiac Resynchronization Therapy in an Asynchronous Heart Failure Model Induced by Left Bundle Branch Ablation and Rapid Pacing
Published on: December 11, 2017
Disease Severity and Exercise Testing Reduce Subcutaneous Implantable Cardioverter-Defibrillator Left Sternal ECG
Neil T Srinivasan1, Kiran H Patel1, Kashif Qamar1
1From the Department of Cardiac Electrophysiology, The Barts Heart Center, St Bartholomew's Hospital, London, United Kingdom (N.T.S., M.B., R.P., P.M.E., P.D.L.); Institute of Cardiovascular Science, University College London, United Kingdom (N.T.S., K.H.P., K.Q., A.T., P.M.E., P.D.L.); and Department of Cardiology, St George's Hospital London, United Kingdom (M.T.-E.).

Insights
Hypertrophic cardiomyopathy (HCM) patients frequently fail subcutaneous implantable cardioverter-defibrillator (S-ICD) screening due to ECG features. Optimizing S-ICD screening algorithms is crucial for high-risk HCM patients.
Area of Science:
- Cardiology
- Medical Devices
Background:
- Hypertrophic cardiomyopathy (HCM) presents unique electrocardiogram (ECG) challenges for subcutaneous implantable cardioverter-defibrillator (S-ICD) screening.
- Investigating S-ICD screening failures in HCM patients is essential for improving device eligibility.
Purpose of the Study:
- To identify the causes of S-ICD screening failure in hypertrophic cardiomyopathy patients at rest and during exercise.
- To inform the development of optimized S-ICD ECG vector selection and sensing algorithms.
Main Methods:
- One hundred thirty-one HCM patients with sudden cardiac death risk factors underwent S-ICD ECG screening.
- Screening was performed in supine and standing positions, with and without exercise.
- Statistical analysis identified factors associated with screening failure, including R:T wave ratio and European Society of Cardiology risk score.
Main Results:
- 38% of HCM patients failed S-ICD screening across all lead vectors.
- Screening failures occurred in supine (66%), standing (24%), and exercise (10%) positions.
- Increased R:T wave ratio was associated with screening failure (OR 4.0), while a low R/T ratio in lead aVF and older age were associated with reduced failure.
Conclusions:
- HCM patients exhibit a high rate of S-ICD screening failure, primarily linked to ECG R:T ratios.
- Higher European Society of Cardiology risk scores correlate with increased screening failure rates.
- Sensing algorithm optimization is necessary to enable S-ICD implantation in high-risk HCM patients.
Background:
The features of the hypertrophic cardiomyopathy (HCM) ECG make it a challenge for subcutaneous implantable cardioverter-defibrillator (S-ICD) screening. We aimed to investigate the causes of screening failure at rest and on exercise to inform optimal S-ICD ECG vector development.
Methods And Results:
One hundred and thirty-one HCM patients (age, 50±16 years; 92 males and 39 females) with ≥1 HCM risk factor for sudden death underwent S-ICD ECG screening at rest and on exercise. Fifty patients (38%) were ineligible for S-ICD because of screening failure in every lead vector: 33 (66%) failed in the supine position, 12 (24%) failed in the standing position, and 5 (10%) failed on exercise. In patients who could exercise and passed screening at rest, 31 (44%) had 1 vector safety, 16 (23%) had 2 vector safety, and 24 (33%) had 3 vector safety. Increased R:T wave ratio in the S-ICD screening ECG (odds ratio, 4.0; confidence interval, 3.0-5.3; P<0.001) was associated with screening failure, while R/T ratio <3 in aVF (odds ratio, 0.3; confidence interval, 0.12-0.69; P=0.006) and increasing age (odds ratio, 0.97; confidence interval, 0.95-0.99; P=0.03) was associated with reduced screening failure. European Society of Cardiology risk score was higher in those failing screening (risk score 5.5% [interquartile range, 3.2-8.7] in failed versus 4.5% [interquartile range, 2.9-7.4] in passed; P=0.04).
Conclusions:
HCM patients have a significant incidence of screening failure, which is determined primarily by the increased R:T ratio on the screening ECG and lead aVF. High-risk patients have an increased screening failure rate. Optimization of sensing algorithms is required to ensure that the highest risk HCM patients can benefit from S-ICD implantation.

Related Concept Videos
 01:26
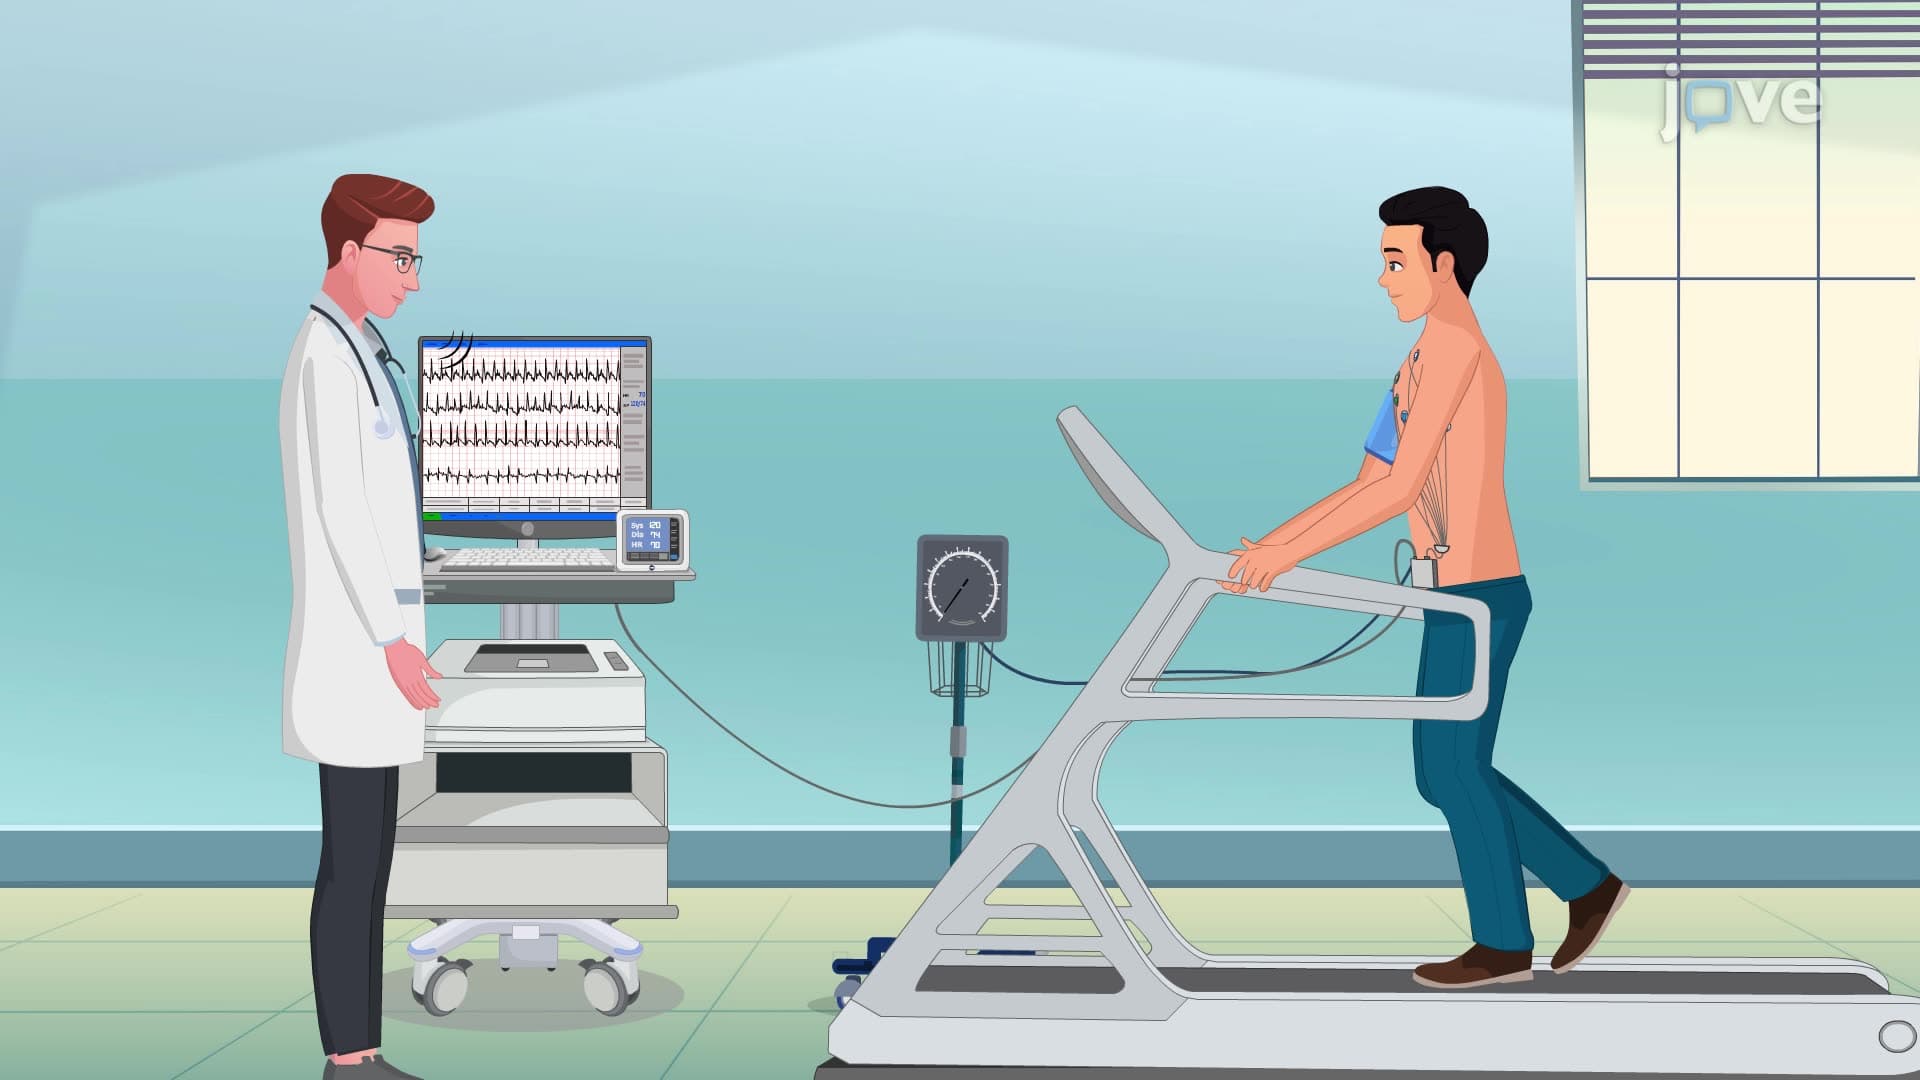
Exercise Stress Test
Exercise stress testing, commonly known as a treadmill test, is a noninvasive procedure used to evaluate cardiovascular function and diagnose heart conditions.
Definition
An exercise stress test measures the heart's response to exertion using a treadmill or stationary bicycle. Chest electrodes record the heart's electrical activity through an ECG, and blood pressure is monitored regularly.
Purposes
 01:23
Mitral Stenosis II: Clinical features and Diagnostic Tests
 01:30
Acute Coronary Syndrome III: Diagnostic Studies
 01:30
Cardiomyopathy II: Dilated Cardiomyopathy
 01:29
Cardiomyopathy III: Hypertrophic Cardiomyopathy
 01:29
Cardiomyopathy V: Interprofessional Care