Related Experiment Video
Updated: Sep 23, 2026
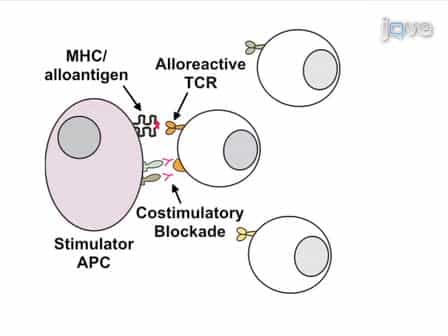

Induction of Alloantigen-specific Anergy in Human Peripheral Blood Mononuclear Cells by Alloantigen Stimulation with Co-stimulatory Signal Blockade
Published on: March 14, 2011
Recipient Immune Modulation with Atorvastatin for Acute Graft-versus-Host Disease Prophylaxis after Allogeneic
Abraham S Kanate1, Parameswaran N Hari2, Marcelo C Pasquini2
1Osborn Hematopoietic Malignancy and Transplantation Program, West Virginia University, Morgantown, West Virginia.

Abstract:
Atorvastatin administration to both the donors and recipients of matched related donor (MRD) allogeneic hematopoietic cell transplantation (allo-HCT) as acute graft-versus-host disease (GVHD) prophylaxis has been shown to be safe and effective. However, its efficacy as acute GVHD prophylaxis when given only to allo-HCT recipients is unknown. We conducted a phase II study to evaluate the safety and efficacy of atorvastatin-based acute GVHD prophylaxis given only to the recipients of MRD (n = 30) or matched unrelated donor (MUD) (n = 39) allo-HCT, enrolled in 2 separate cohorts. Atorvastatin (40 mg/day) was administered along with standard GVHD prophylaxis consisting of tacrolimus and methotrexate. All patients were evaluable for acute GVHD. The cumulative incidences of grade II to IV acute GVHD at day +100 in the MRD and MUD cohorts were 9.9% (95% confidence interval [CI], 0 to 20%) and 29.6% (95% CI,15.6% to 43.6%), respectively. The cumulative incidences of grade III and IV acute GVHD at day +100 in the MRD and MUD cohorts were 3.4% (95% CI, 0 to 9.7%) and 18.3% (95% CI, 6.3% to 30.4%), respectively. The corresponding rates of moderate/severe chronic GVHD at 1 year were 28.1% (95% CI, 11% to 45.2%) and 38.9% (95% CI, 20.9% to 57%), respectively. In the MRD cohort, the 1-year nonrelapse mortality, relapse rate, progression-free survival, and overall survival were 6.7% (95% CI, 0 to 15.4%), 43.3% (95% CI, 24.9% to 61.7%), 50% (95% CI, 32.1% to 67.9%), and 66.7% (95% CI, 49.8% to 83.6%), respectively. The respective figures for the MUD cohort were 10.3% (95% CI, 8% to 19.7%), 20.5% (95% CI, 7.9% to 33.1%), 69.2% (95% CI, 54.7% to 83.7%), and 79.5% (95% CI, 66.8% to 92.2%), respectively. No grade 4 toxicities attributable to atorvastatin were seen. In conclusion, the addition of atorvastatin to standard GVHD prophylaxis in only the recipients of MRD and MUD allo-HCT appears to be feasible and safe. The preliminary efficacy seen here warrants confirmation in randomized trials.


Related Concept Videos
 01:40
Cell-mediated Immune Responses
 01:22
Bone Marrow Sampling and Transplants
The transplant begins with high doses of chemotherapy and radiation treatment, which aim to destroy the...
 01:24
Tissue Transplantation
The Biology of Tissue Transplantation
The biology of tissue transplantation hinges on the Major Histocompatibility Complex (MHC) molecules. These molecules...