Related Experiment Video
Updated: Mar 2, 2026


Combining Volumetric Capnography And Barometric Plethysmography To Measure The Lung Structure-function Relationship
Published on: January 8, 2019
Calculated versus Measured MVV-Surrogate Marker of Ventilatory Capacity in Pediatric CPET
Kelly L Colwell1, Rajeev Bhatia
1Division of Pulmonology, Department of Pediatrics, Akron Children's Hospital, Akron, OH.

Introduction:
Maximum voluntary ventilation (MVV), a surrogate marker of maximum ventilatory capacity, allows for measuring ventilatory reserve during cardiopulmonary exercise testing (CPET), which is necessary to assess ventilatory limitation. MVV can be measured directly during a patient maneuver or indirectly by calculating from forced expiratory volume in 1 s (FEV1 × 40). We investigated for a potential difference between calculated MVV and measured MVV in pediatric subjects, and which better represents maximum ventilatory capacity during CPET.
Methods:
Data were collected retrospectively from CPET conducted in pediatric subjects for exercise-induced dyspnea from January 2014 to June 2015 at Akron Children's Hospital. Subjects with neuromuscular weakness, morbid obesity, and suboptimal effort during the testing were excluded from the study.
Results:
Thirty-five subjects (mean ± SD, age = 13.8 ± 2.7 yr, range = 7-18 yr) fulfilled the criteria. Measured MVV was significantly lower than calculated MVV (89.9 ± 26.4 vs 122.4 ± 34.5 L·min; P < 0.01). The ventilatory reserve based on measured MVV was also significantly lower than ventilatory reserve based on calculated MVV (12.4% ± 19.6% vs 36.1% ± 13.2%; P < 0.01). Calculated MVV (as well as ventilatory reserve based on calculated MVV) was significantly correlated with ventilatory parameters. By contrast, no significant correlations were found between measured MVV (or ventilatory reserve based on measured MVV) and ventilatory parameters except for peak ventilation (peak V˙E).
Conclusions:
The measured MVV was significantly lower than the calculated MVV in our pediatric subjects. The calculated MVV was a better surrogate of maximum ventilatory capacity as shown by significant correlation to other ventilatory parameters during CPET.

Related Concept Videos
 01:20
Assessment of Ventilation I: Respiratory Rate
A Ventilation assessment is critical for monitoring a patient's health status. Respiration, one of the most accessible vital signs, provides insights into the function of numerous body systems and can indicate serious health issues, such as brainstem injuries from head trauma.
Critical Guidelines for Assessing Ventilation:
 01:22
Respiratory Volumes and Capacities
 01:15
Respiratory Volumes
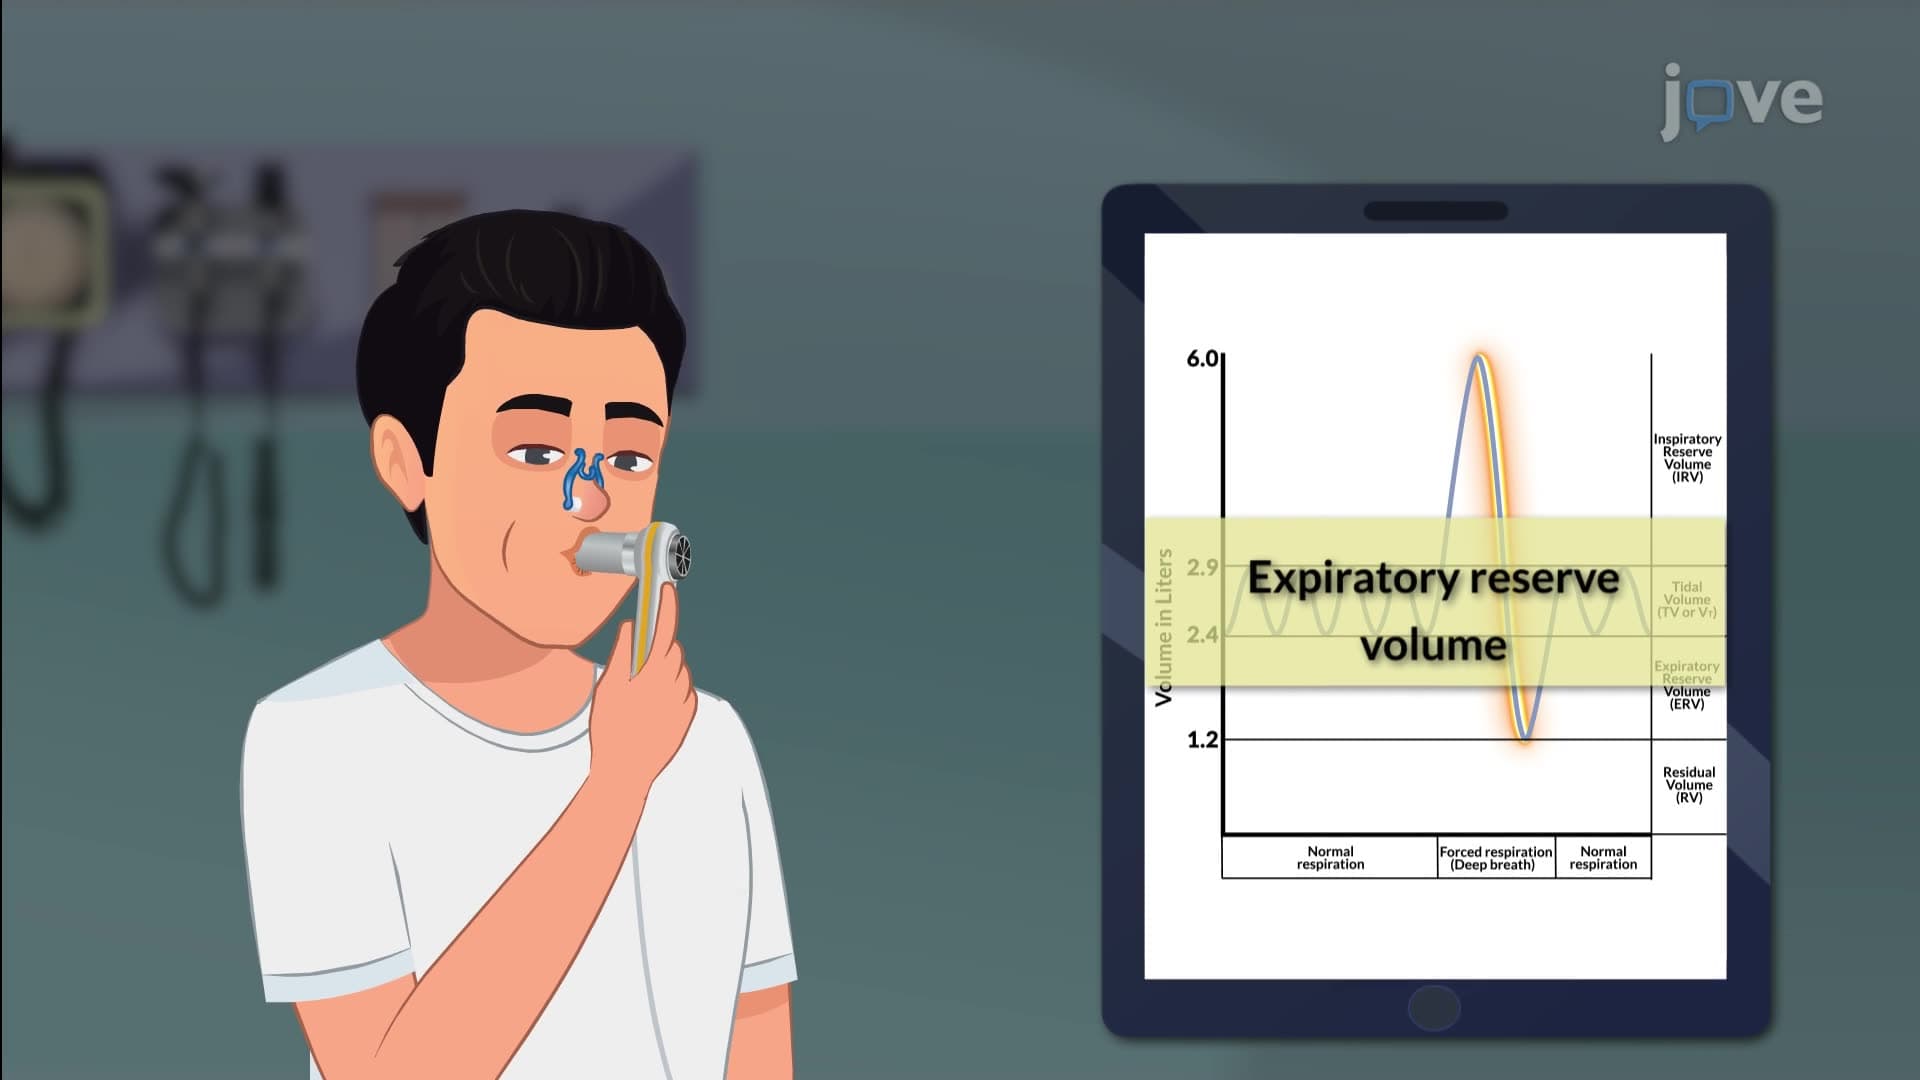
Tidal Volume (TV) Tidal volume (TV) is the air inhaled or exhaled in a...
 01:29
Assessment of Ventilation II: Respiratory Depth and Rhythm
Respiratory depth measures the volume of air inhaled or exhaled during a breath. It can vary from shallow to deep and typically remains consistent when a person is at rest or asleep. Occasionally, individuals will automatically inhale deeply, known as sighing, which inflates the lungs with more air than normal breathing.
To assess respiratory depth, observe the degree of chest excursion or movement:
 01:17
Assessment of Diffusion and Perfusion
The Role of Diffusion in Respiration
Diffusion is the process by which molecules move from an area of higher concentration to an area of lower concentration. In the respiratory system, this...
 01:26
Respiratory Volumes and Capacities I