Related Experiment Video
Updated: Mar 1, 2026


Evaluation of Patients' Posture and Gait Profile After Lumbar Fusion Surgery by Video Rasterstereography and Treadmill Gait Analysis
Published on: March 23, 2019
Characterizing Adult Cervical Deformity and Disability Based on Existing Cervical and Adult Deformity Classification
Peter G Passias1, Cyrus M Jalai1, Justin S Smith2
1Division of Spine Surgery, Hospital for Joint Diseases, NYU Langone Medical Center, New York, New York.

Background:
Adult cervical deformity (ACD) classifications have not been implemented in a prospective ACD population and in conjunction with adult spinal deformity (ASD) classifications.
Objective:
To characterize cervical deformity type and malalignment with 2 classifications (Ames-ACD and Schwab-ASD).
Methods:
Retrospective review of a prospective multicenter ACD database. Inclusion: patients ≥18 yr with pre- and postoperative radiographs. Patients were classified with Ames-ACD and Schwab-ASD schemes. Ames-ACD descriptors (C = cervical, CT = cervicothoracic, T = thoracic, S = coronal, CVJ = craniovertebral) and alignment modifiers (cervical sagittal vertical axis [cSVA], T1 slope minus cervical lordosis [TS-CL], modified Japanese Ortphopaedic Association [mJOA] score, horizontal gaze) were assigned. Schwab-ASD curve type stratification and modifier grades were also designated. Deformity and alignment group distributions were compared with Pearson χ2/ANOVA.
Results:
Ames-ACD descriptors in 84 patients: C = 49 (58.3%), CT = 20 (23.8%), T = 9 (10.7%), S = 6 (7.1%). cSVA modifier grades differed in C, CT, and T deformities (P < .019). In C, TS-CL grade prevalence differed (P = .031). Among Ames-ACD modifiers, high (1+2) cSVA grades differed across deformities (C = 47.7%, CT = 89.5%, T = 77.8%, S = 50.0%, P = .013). Schwab-ASD curve type and presence (n = 74, T = 2, L = 6, D = 2) differed significantly in S deformities (P < .001). Higher Schwab-ASD pelvic incidence minus lumbar lordosis grades were less likely in Ames-ACD CT deformities (P = .027). Higher pelvic tilt grades were greater in high (1+2) cSVA (71.4% vs 36.0%, P = .015) and high (2+3) mJOA (24.0% vs 38.1%, P = .021) scores. Postoperatively, C and CT deformities had a trend toward lower cSVA grades, but only C deformities differed in TS-CL grade prevalence (0 = 31.3%, 1 = 12.2%, 2 = 56.1%, P = .007).
Conclusion:
Cervical deformities displayed higher TS-CL grades and different cSVA grade distributions. Preoperative associations with global alignment modifiers and Ames-ACD descriptors were observed, though only cervical modifiers showed postoperative differences.
More Related Videos
Related Concept Videos
 01:16
Vertebral Column: Regions and Curvature
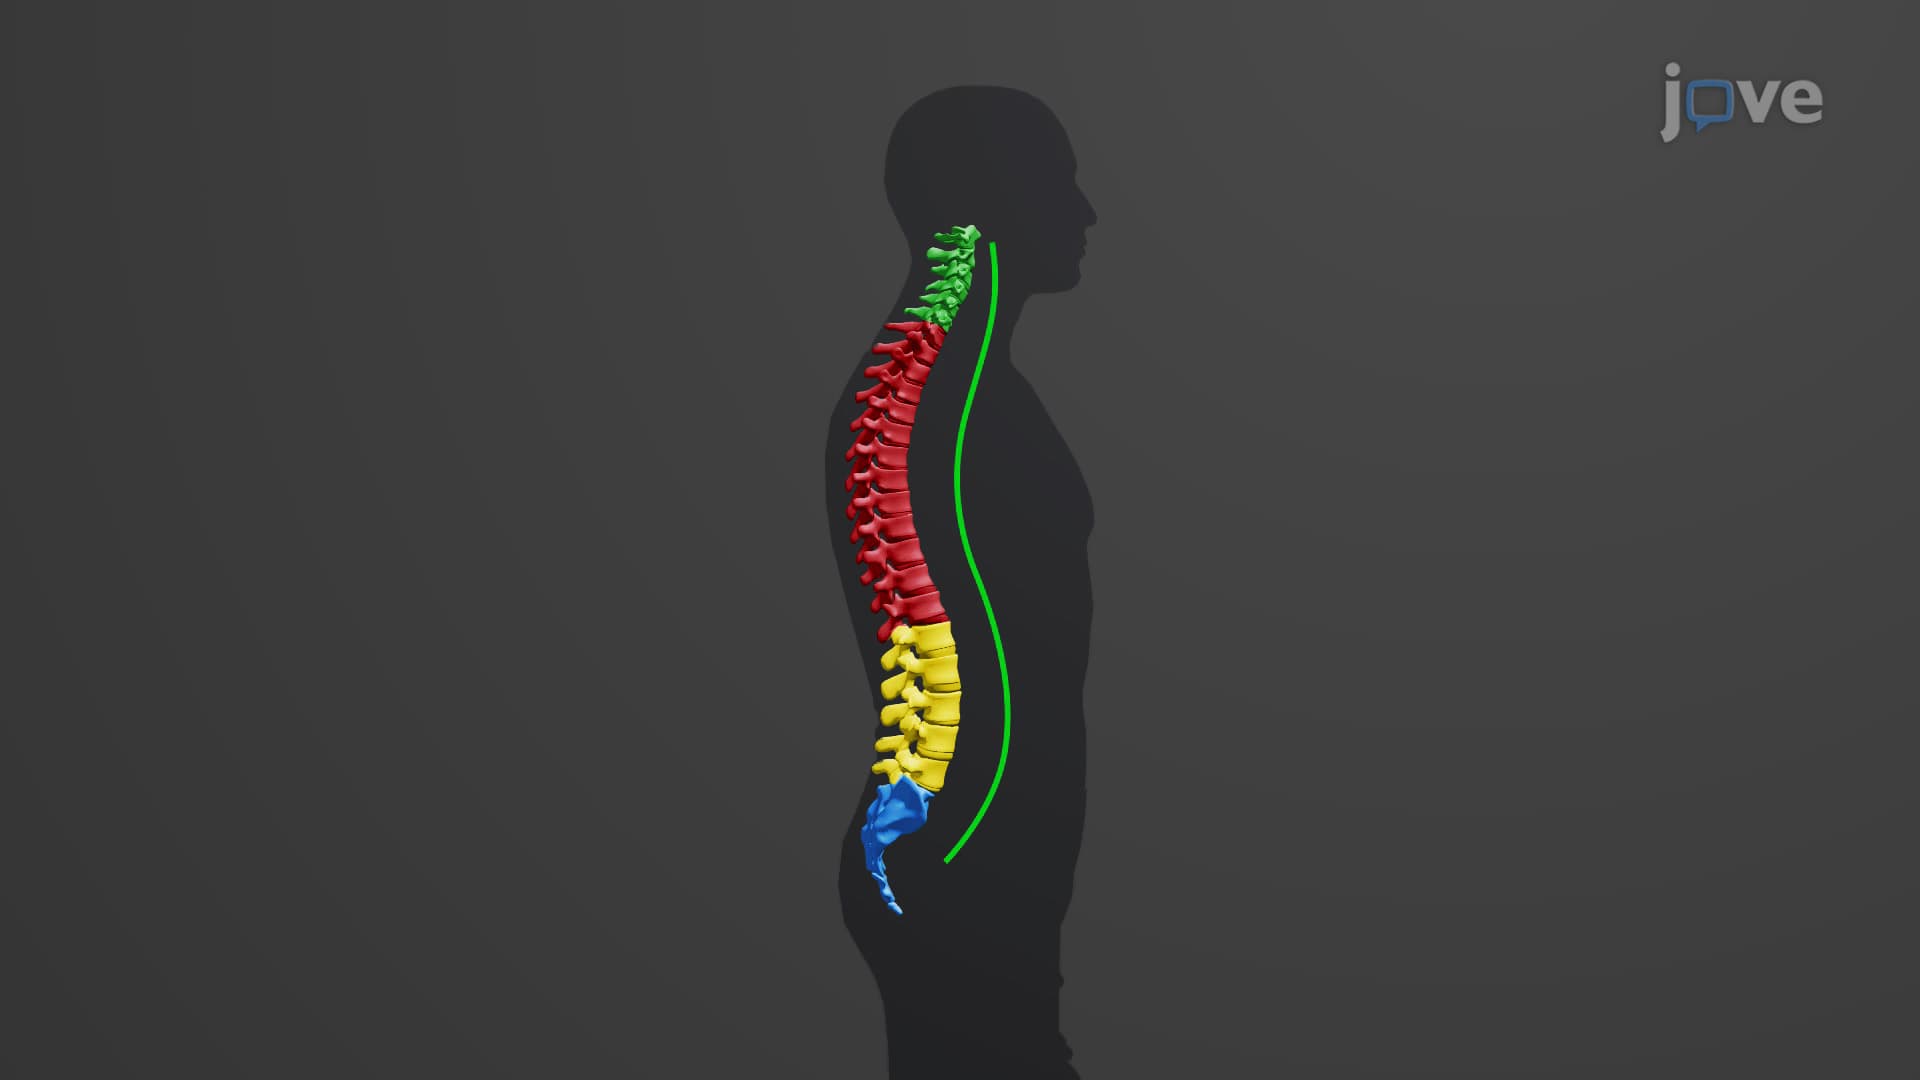
Regions of the Vertebral Column
In an adult, the spine is subdivided into five regions: the cervical, the thoracic, the lumbar, the sacral, and the coccygeal region. The spine initially develops as a series of 33 vertebrae; after 20 years of age, the nine bones in the sacral region, five sacral, and four coccygeal bones fuse to form...
 01:11
Deformation of Member under Multiple Loadings
In the case of a member with a variable cross-section, the strain is not constant but depends on the position. The deformation of an...
 01:12
Temperature Dependent Deformation
 01:09
Changes in the Appendicular Skeleton with Age
Initially, the limb buds consist of a core of mesenchyme covered by a layer of ectoderm. The ectoderm at the end of the limb bud thickens to form a narrow crest called the apical ectodermal ridge. This ridge stimulates the underlying...
 01:09
Functional Classification of Joints
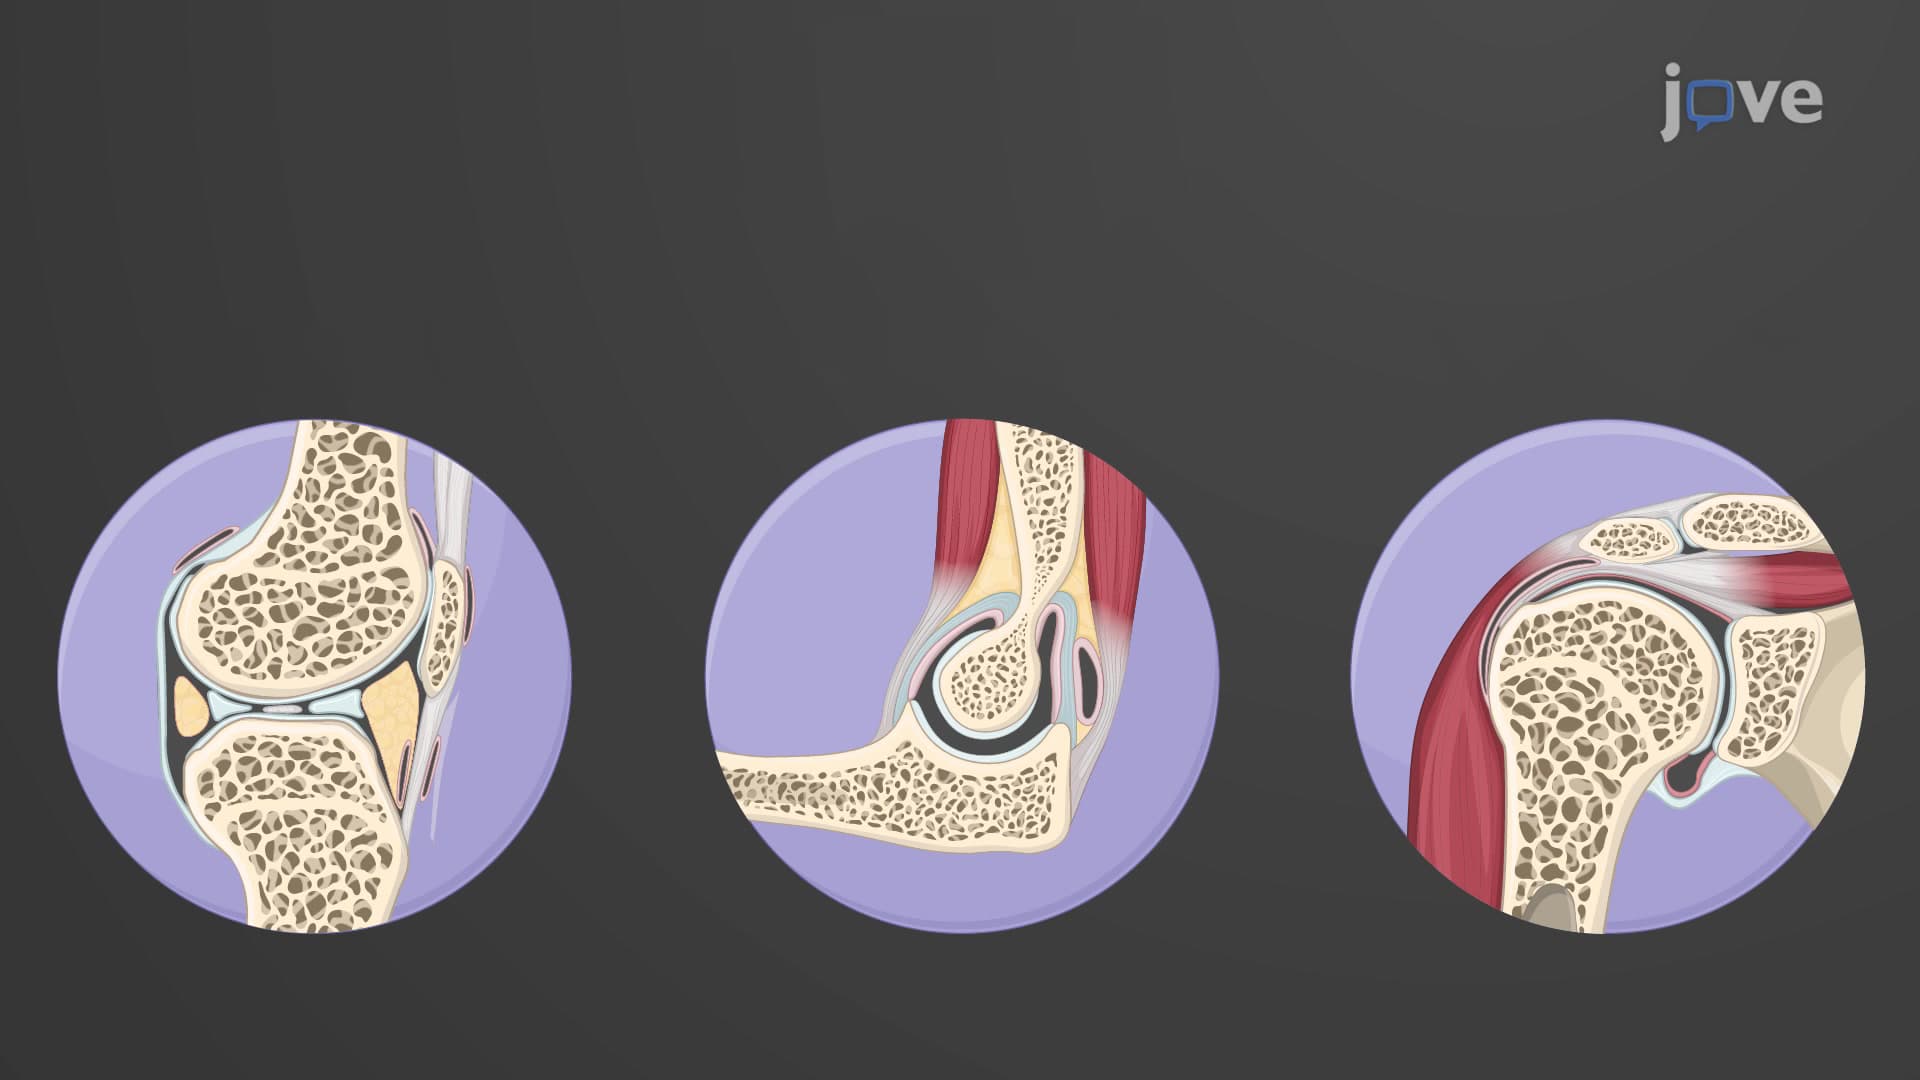
The functional classification of joints is determined by the amount of mobility between the adjacent bones. Joints are functionally classified as a synarthrosis or immobile joint, an amphiarthrosis or slightly moveable joint, or as a diarthrosis, a freely moveable joint. Fibrous and cartilaginous joints can be functionally classified as either synarthroses or amphiarthroses, whereas all synovial joints are classified as diarthroses.
Synarthrosis
An...