Related Experiment Video
Updated: Aug 30, 2026

Minimally Invasive Treatment for Thoracolumbar Burst Fracture Using Sagittal Alignment Screws and A Trauma Reduction Device
Published on: November 8, 2024
Trends in the distribution of skeletal compensation based on severity and correction in adult spinal deformity
Oluwatobi O Onafowokan1, Mohammad Daher1, Renaud Lafage2
11Duke Spine Division, Departments of Neurological and Orthopaedic Surgery, Duke School of Medicine, Durham, North Carolina.

Objective:
Adult spinal deformity (ASD) surgery patients maintain upright posture by using numerous compensatory mechanisms. The distribution of this compensation throughout the skeleton has not been fully investigated.
Methods:
Patients with lumbar deformity curves undergoing fusion from T10 to the pelvis were included. Groups were stratified by Scoliosis Research Society (SRS)-Schwab sagittal deformity severity (mild, moderate, and severe). Compensation was determined based on the published values of asymptomatic individuals by Bao et al. (2018), with patients outside 1 standard deviation of the mean values deemed to be compensating. Adequate deformity correction was determined based on matching published sagittal age-adjusted score (SAAS) criteria. Means comparisons tests assessed differences between cohorts at each time point.
Results:
In total, 379 ASD patients were included (mean age 66.7 ± 10.2 years, body mass index 28.4 ± 5.4 kg/m2, Charlson Comorbidity Index 1.20 ± 1.73). In total, 23.8% of patients had mild deformity, 19.2% moderate, and 57% severe. The severe deformity cohort generally demonstrated the highest rates of compensation across all regions at different time points. At baseline, the severe and moderate cohorts demonstrated predominantly lower limb-dominant compensation, with the highest frequencies of compensation seen at the knee and pelvis. In the mild cohort, knee compensation was relieved by 1 year when adequate correction was achieved. For the moderate cohort, hip and pelvic compensation were relieved first, with knee compensatory relief occurring by 2 years. For the severe cohort, pelvic compensation was relieved first, with global lower limb and thoracic compensation subsequently occurring.
Conclusions:
There is notable variation in how ASD patients compensate as the severity of their deformity progresses. There is also variation in how these patterns are altered postoperatively.
More Related Videos
 07:12
Clinical Efficacy of an Innovative Multidimensional Traction Therapy in Moderate Adolescent Idiopathic Scoliosis
Published on: February 10, 2026
 07:44
Evaluation of Patients' Posture and Gait Profile After Lumbar Fusion Surgery by Video Rasterstereography and Treadmill Gait Analysis
Published on: March 23, 2019
Related Concept Videos
 01:16
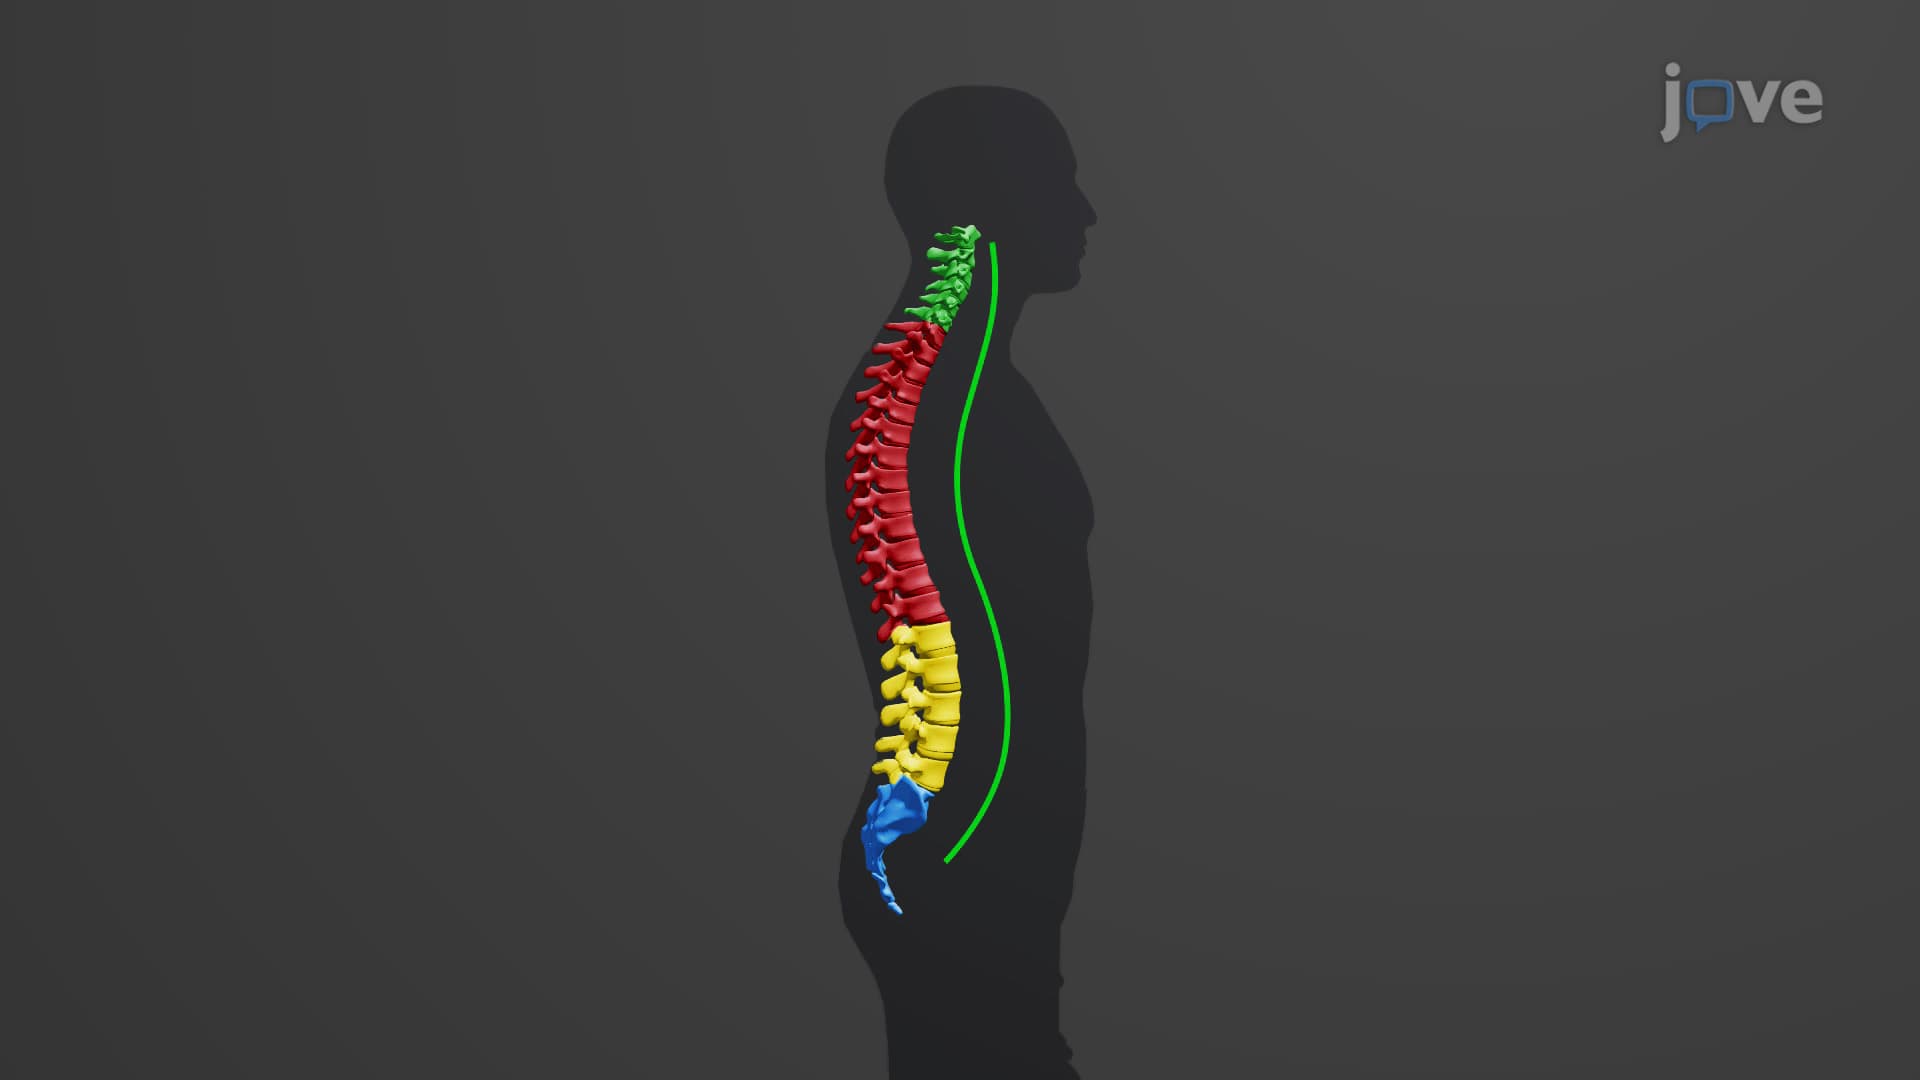
Vertebral Column: Regions and Curvature
Regions of the Vertebral Column
In an adult, the spine is subdivided into five regions: the cervical, the thoracic, the lumbar, the sacral, and the coccygeal region. The spine initially develops as a series of 33 vertebrae; after 20 years of age, the nine bones in the sacral region, five sacral, and four coccygeal bones fuse to form the...
 01:29
Bone Disorders
Bone deposition is also affected by the levels of sex hormones like estrogen and testosterone that promote osteoblast activity and bone matrix synthesis. When the level of these hormones decreases due to aging, it causes a reduction in bone deposition. As a result, bone resorption by osteoclasts...
 01:27
Fractures: Bone Repair
Minor fractures with no bone displacement are treated by immobilizing the fractured bone using a cast or splint. However, in the case of fractures with displaced bones, the broken bones are repositioned before immobilization to ensure successful healing without deformation and loss of function. The realignment of fractured bone ends is performed through a process called reduction. If the procedure...