Related Experiment Video
Updated: Mar 1, 2026
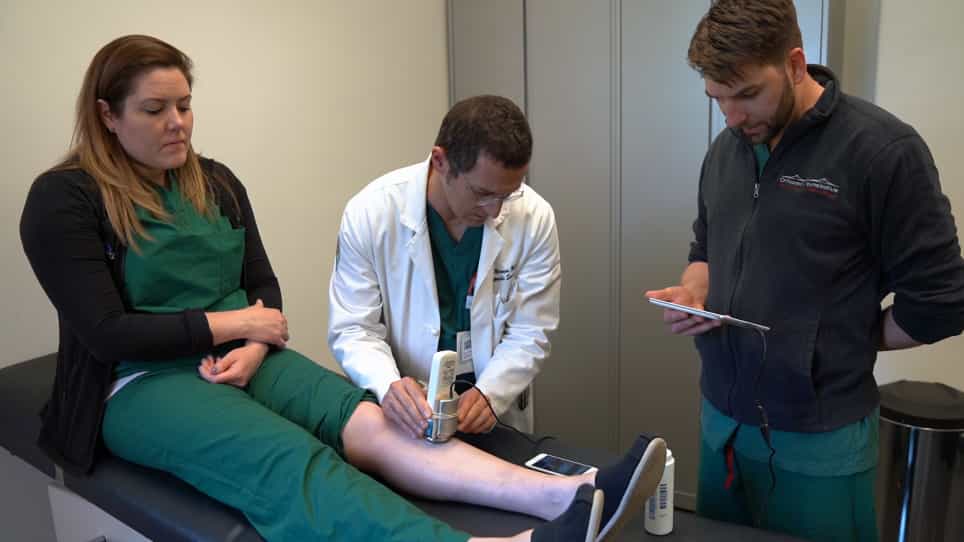

A Novel Non-invasive Method for the Detection of Elevated Intra-compartmental Pressures of the Leg
Published on: May 31, 2019
Extremity compartment syndrome following blunt trauma: a level I trauma center's 5-year experience
Daniel Zuchelli1, Nicholas Divaris2, Jane E McCormack1
1Division of Trauma, Department of Surgery, Stony Brook University School of Medicine, Stony Brook, New York.

Background:
Extremity compartment syndrome is a recognized complication of trauma. We evaluated its prevalence and outcomes at a suburban level 1 trauma center.
Methods:
The trauma registry was reviewed for all blunt trauma patients aged ≥18 years, admitted between 2010 and 2014. Chart review of patients with extremity compartment syndrome was performed.
Results:
Of 6180 adult blunt trauma admissions, 83 patients developed 86 extremity compartment syndromes; two patients had compartment syndromes on multiple locations. Their (n = 83) median age was 44 years (interquartile range: 31.5-55.5). The most common mechanism of injury was motor vehicle/motor cycle accident (45.8%) followed by a fall (21.7%). The median injury severity score was 9 (interquartile range: 5-17); 65.1% had extremity abbreviate injury score ≥3. Notably, 15 compartment syndromes did not have an underlying fracture. Among patients with fractures, the most commonly injured bone was the tibia, with tibial plateau followed by tibial diaphyseal fractures being the most frequent locations. Fasciotomies were performed, in order of frequency, in the leg (n = 53), forearm (n = 15), thigh (n = 9), foot (n = 5), followed by multiple or other locations.
Conclusions:
Extremity compartment syndrome was a relatively uncommon finding. It occurred in all extremity locations, with or without an associated underlying fracture, and from a variety of mechanisms. Vigilance is warranted in evaluating the compartments of patients with extremity injuries following blunt trauma.
More Related Videos

Related Concept Videos
 01:21
Peripheral Arterial Disease II: Clinical Manifestations and Diagnostic Evaluation
 01:26
Flail Chest-II
Assessment:
1. Clinical Evaluation:
History:
 01:22
Burn Injuries
The damage results in the death of skin cells, which can lead to a massive loss of fluid. Dehydration, electrolyte imbalance, and renal and circulatory failure follow, which can be fatal. Burn patients are treated with intravenous fluids to offset...
 01:27
Assessment of the Cardiovascular System III: Palpation
Jugular Venous Pressure (JVP) Measurement
Position the patient at a thirty- to forty-five-degree angle or in a semi-fowler's position. Look for the highest point of pulsation in the internal jugular vein and measure the vertical distance to the angle of Loius or sternal angle. A normal JVP is 3-4 cm above...
 01:24
Flail Chest-I
Flail chest is a severe and potentially life-threatening condition characterized by the fracture of three or more adjacent ribs in multiple places. It is most commonly caused by direct impacts and trauma, such as motor vehicle accidents or injuries from a steering wheel impact. It can also occur due to falls in elderly individuals with osteoporosis, or assaults involving sharp objects.
Pathophysiology
The pathophysiology of flail chest is complex, involving fractures of...
 01:23
Peripheral Artery Disease V: Postoperative Nursing Management