Related Experiment Video
Updated: Feb 28, 2026
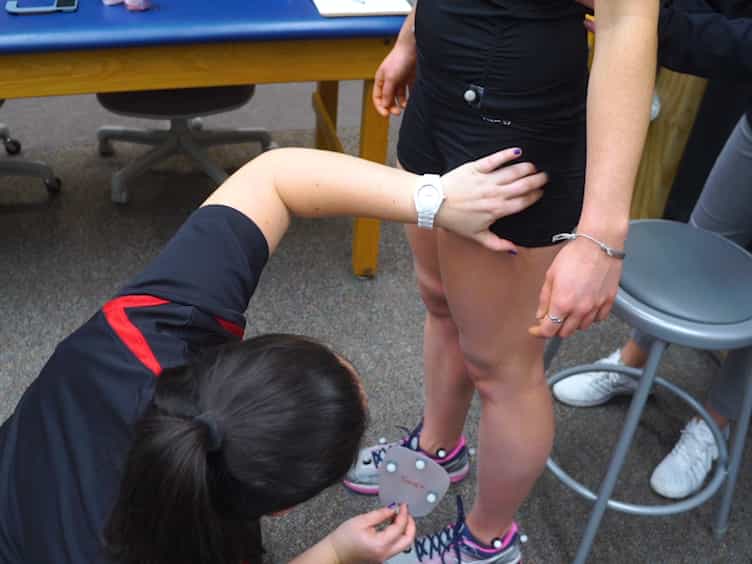

Subject-specific Musculoskeletal Model for Studying Bone Strain During Dynamic Motion
Published on: April 11, 2018
Stress Fractures: Etiology, Epidemiology, Diagnosis, Treatment, and Prevention

Abstract:
Stress fractures are part of a continuum of changes in healthy bones in response to repeated mechanical deformation from physical activity. If the activity produces excessive repetitive stress, osteoclastic processes in the bone may proceed at a faster pace than osteoblastic processes, thus weakening the bone and augmenting susceptibility to stress fractures. Overall stress fracture incidence is about three cases per 1,000 in active duty Servicemembers, but it is much higher among Army basic trainees: 19 per 1,000 for men and 80 per 1,000 for women. Well-documented risk factors include female sex, white ethnicity, older age, taller stature, lower aerobic fitness, prior physical inactivity, greater amounts of current physical training, thinner bones, cigarette smoking, and inadequate intake of vitamin D and/or calcium. Individuals with stress fractures present with focal tenderness and local pain that is aggravated by physical activity and reduced by rest. A sudden increase in the volume of physical activity along with other risk factors is often reported. Simple clinical tests can assist in diagnosis, but more definitive imaging tests will eventually need to be conducted if a stress fracture is suspected. Plain radiographs are recommended as the initial imaging test, but magnetic resonance imaging has higher sensitivity and is more likely to detect the injury sooner. Treatment involves first determining if the stress fracture is of higher or lower risk; these are distinguished by anatomical location and whether the bone is loaded in tension (high risk) or compression (lower risk). Lowerrisk stress fractures can be initially treated by reducing loading on the injured bone through a reduction in activity or by substituting other activities. Higher-risk stress fractures should be referred to an orthopedist. Investigated prevention strategies include modifications to physical training programs, use of shock absorbing insoles, vitamin D and calcium supplementation, modifications of military equipment, and leadership education with injury surveillance.


Related Concept Videos
 01:27
Fractures: Bone Repair
Minor fractures with no bone displacement are treated by immobilizing the fractured bone using a cast or splint. However, in the case of fractures with displaced bones, the broken bones are repositioned before immobilization to ensure successful healing without deformation and loss of function. The realignment of fractured bone ends is performed through a process called reduction. If the...
 01:29
Bone Disorders
Bone deposition is also affected by the levels of sex hormones like estrogen and testosterone that promote osteoblast activity and bone matrix synthesis. When the level of these hormones decreases due to aging, it causes a reduction in bone deposition. As a result, bone resorption by osteoclasts...
 01:28
Disorders of the Skeletal Muscle
Musculoskeletal disorders
Musculoskeletal disorders involve injuries and conditions affecting the skeletal muscles and associated connective tissues. These disorders can arise from acute biomechanical stresses or chronic overuse and can occur across different age groups. Common injuries include sprains, fractures, and muscular strains, often resulting from...
 01:31
Osteoclasts in Bone Remodeling
 01:26
Exercise Stress Test
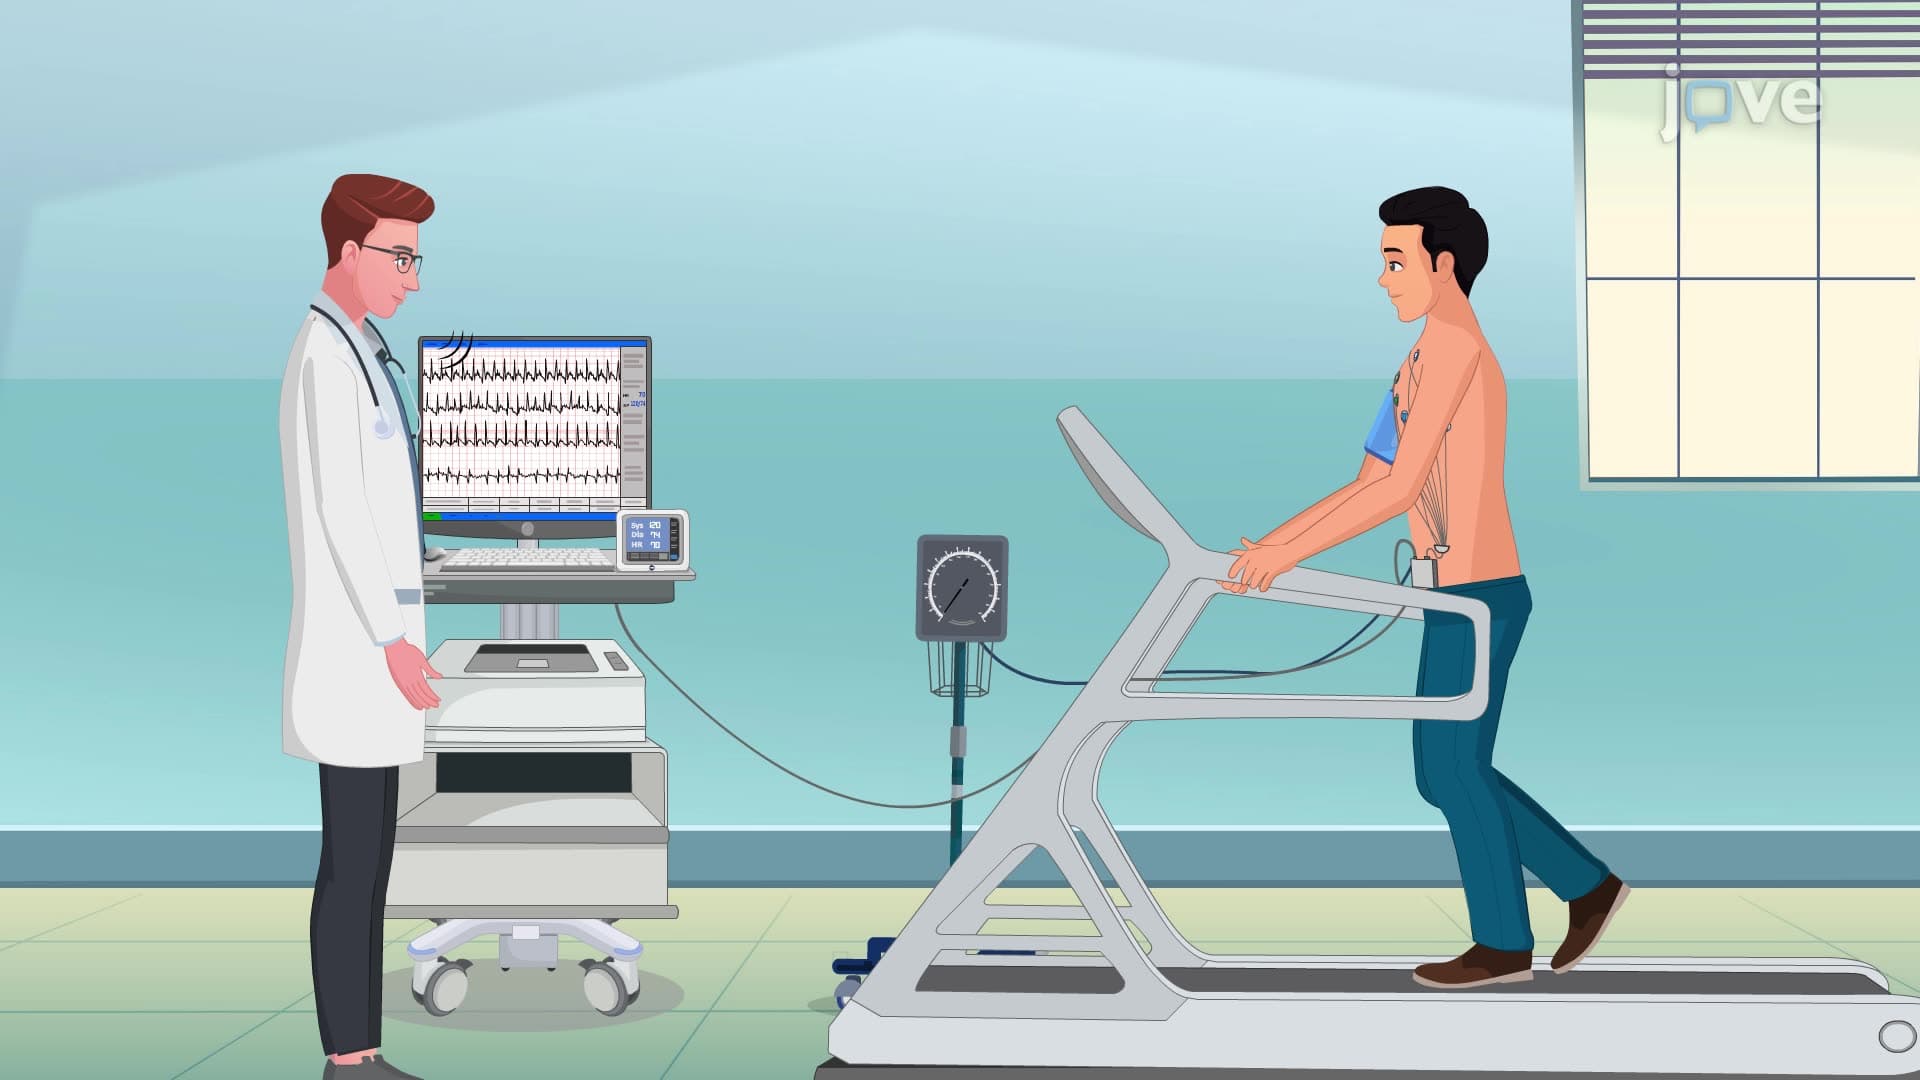
Exercise stress testing, commonly known as a treadmill test, is a noninvasive procedure used to evaluate cardiovascular function and diagnose heart conditions.
Definition
An exercise stress test measures the heart's response to exertion using a treadmill or stationary bicycle. Chest electrodes record the heart's electrical activity through an ECG, and blood pressure is monitored regularly.
Purposes
 01:21
Fatigue