Related Experiment Video
Updated: Feb 28, 2026
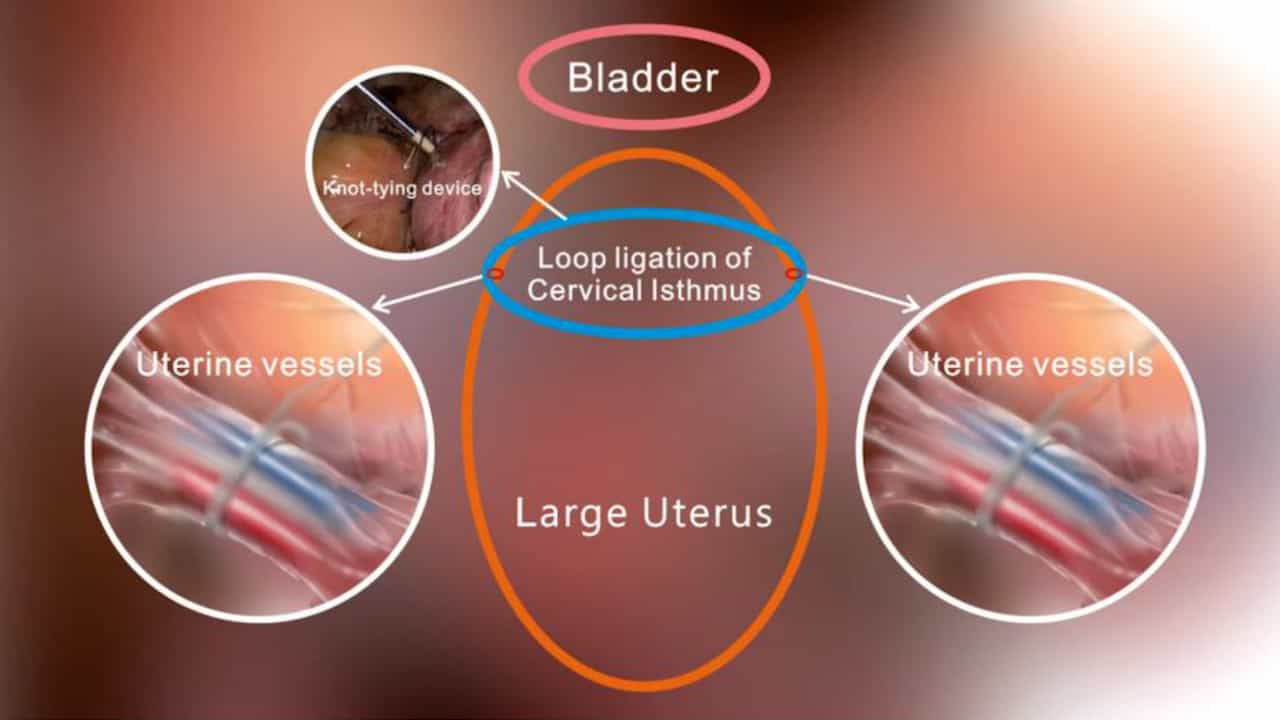

Laparoscopic Extracorporeal Knot-Tying for Uterine Vessel Occlusion during Hysterectomy with Cervical Cerclage in Large Uteri
Published on: September 12, 2025
Sterility of Selected Operative Sites During Total Laparoscopic Hysterectomy
Marie E Shockley1, Benjamin Beran1, Heather Nutting2
1Division of Gynecology, Cleveland Clinic Florida, Weston, Florida.

Study Objective:
To describe the type and quantity of bacteria found intraoperatively on the abdomen, vagina, surgical gloves, instrument tips, and uterus at distinct time points during total laparoscopic hysterectomy (TLH).
Design:
Observational study (Canadian Task Force classification III).
Setting:
Academic affiliated hospital.
Patients:
Thirty-one women undergoing TLH for benign indications in 2016.
Interventions:
After antibiotic prophylaxis and chlorhexidine preparation, swabs were collected from the vaginal fornices and abdomen. During subsequent TLH, additional swabs were collected from the following sites: surgeon's gloves after placement of the uterine manipulator, tips of instruments used to close the vaginal cuff, uterine fundus after extraction, and surgeon's gloves after removal of the uterus. A calibrated loop was used to inoculate each specimen onto 5% blood and chocolate agars for growth of aerobes and onto Brucella blood, phenylethyl alcohol, kanamycin vancomycin, and Bacteroides bile esculin agars for growth of anaerobes. Manual colony counts were tabulated for all positive cultures and reported in colony-forming units per milliliter (CFU/mL).
Measurements And Main Results:
Anaerobic growth was not seen on the instrument tips, in the vagina, or on the abdomen of any patient. Aerobic bacterial growth was not seen in the vagina of any patient. On the surgeon's gloves after uterine manipulator placement, no patients demonstrated sufficient bacterial growth to potentially cause surgical site infection (≥5000 CFU/mL). On the surgeon's gloves following uterine extraction, 1 patient demonstrated sufficient growth to potentially cause infection. None of the patients developed surgical site infections postoperatively.
Conclusion:
Cultures from multiple operative sites yielded bacterial growth, but the bacterial concentrations did not exceed the threshold for infection in 98.9% of cultures. Given absent growth from vaginal cultures and rare growth from abdominal cultures, chlorhexidine gluconate 4% is considered an appropriate surgical preparation for use in laparoscopic hysterectomy.
More Related Videos
 11:29
Surgical Techniques to Optimize Ovarian Reserve during Laparoscopic Cystectomy for Ovarian Endometrioma
Published on: January 22, 2022
 03:33
Author Spotlight: Advancing Hepatobiliary and Pancreatic Tumor Treatment with Minimally Invasive Surgical Techniques
Published on: September 27, 2024