Related Experiment Video
Updated: Feb 28, 2026


Author Spotlight: Point-of-Care Ultrasound for Gastric Content Assessment and Risk Stratification in Perioperative Care
Published on: September 22, 2023
Sonographic appearance of anal cushions of hemorrhoids
Adilijiang Aimaiti1, Ma Mu Ti Jiang A Ba Bai Ke Re1, Irshat Ibrahim1
1Adilijiang Aimaiti, Mayinuer, Department of Anorectal Surgery, Second Affiliated Hospital, Xinjiang Medical University, Urumqi 830011, Xinjiang Uygur Autonomous Region, China.

Aim:
To evaluate the diagnostic value of different sonographic methods in hemorrhoids.
Methods:
Forty-two healthy volunteers and sixty-two patients with grades I-IV hemorrhoids received two different sonographic examinations from January 2013 to January 2016 at the First and Second Hospitals of Xinjiang Medical University in a prospective way. We analyzed the ultrasonographic findings of these participants and evaluated the outcomes. Resected grades III and IV hemorrhoid tissues were pathologically examined. The concordance of ultrasonographic results with pathology results was assessed with the Cohen's kappa coefficient.
Results:
All healthy volunteers and all patients had no particular complications related to sonography. There were no statistically significant differences between the participants regarding age (P = 0.5919), gender (P = 0.4183), and persistent symptoms (P > 0.8692). All healthy control participants had no special findings. However, 30 patients with hemorrhoids showed blood signals around the dentate line on ultrasonography. When grades I and II hemorrhoids were analyzed, there were no significant differences between transrectal ultrasound (TRUS), transperianal ultrasound (TPUS), and transvaginal ultrasound (TVUS) (P > 0.05). Grades III and IV hemorrhoids revealed blood flow with different directions which could be observed as a "mosaic pattern". In patients with grades III and IV hemorrhoids, the number of patients with "mosaic pattern" as revealed by TRUS, TPUS and TVUS was 22, 12, and 4, respectively. Patients with grades III and IV disease presented with a pathologically abnormal cushion which usually appeared as a "mosaic pattern" in TPUS and an arteriovenous fistula in pathology. Subepithelial vessels of resected grades III and IV hemorrhoid tissues were manifested by obvious structural impairment and retrograde and ruptured changes of internal elastic lamina. Some parts of the Trietz's muscle showed hypertrophy and distortion. Arteriovenous fistulas and venous dilatation were obvious in the anal cushion of hemorhoidal tissues. After pathological results with arteriovenous fistulas were taken as the standard reference, we evaluated the compatibility between the two methods according to the Cohen's kappa co-efficiency calculation. The compatibility (Cohein kappa co-efficiency value) between "mosaic pattern" in the TPUS and arteriovenous fistula in pathology was very good (ĸ = 0.8939). When compared between different groups, TRUS presented the advantage that the mosaic pattern could be confirmed in more patients, especially for group A. There was a statistical difference when comparing group A with group B or C (P < 0.05 for both). There were obvious statistical differences between group A and group B with regard to the vessel diameter and blood flow velocity measured by TRUS (P < 0.05).
Conclusion:
Patients with grades III and IV hemorrhoids present with a pathologically abnormal cushion which usually appears as a "mosaic pattern" in sonography, which is in accord with an arteriovenous fistula in pathology. There are clearly different hemorrhoid structures shown by sonography. "Mosaic pattern" may be a parameter for surgical indication of grades III and IV hemorrhoids.
More Related Videos
 07:41
Quantification of Levator Ani Hiatus Enlargement by Magnetic Resonance Imaging in Males and Females with Pelvic Organ Prolapse
Published on: April 17, 2019
 15:49
Flexible Colonoscopy in Mice to Evaluate the Severity of Colitis and Colorectal Tumors Using a Validated Endoscopic Scoring System
Published on: October 16, 2013
Related Concept Videos
 01:25
Assessment of the Rectum and Anus
Rectal Inspection
Begin by inspecting the perianal and anal areas for color, texture, rashes,...
 01:26
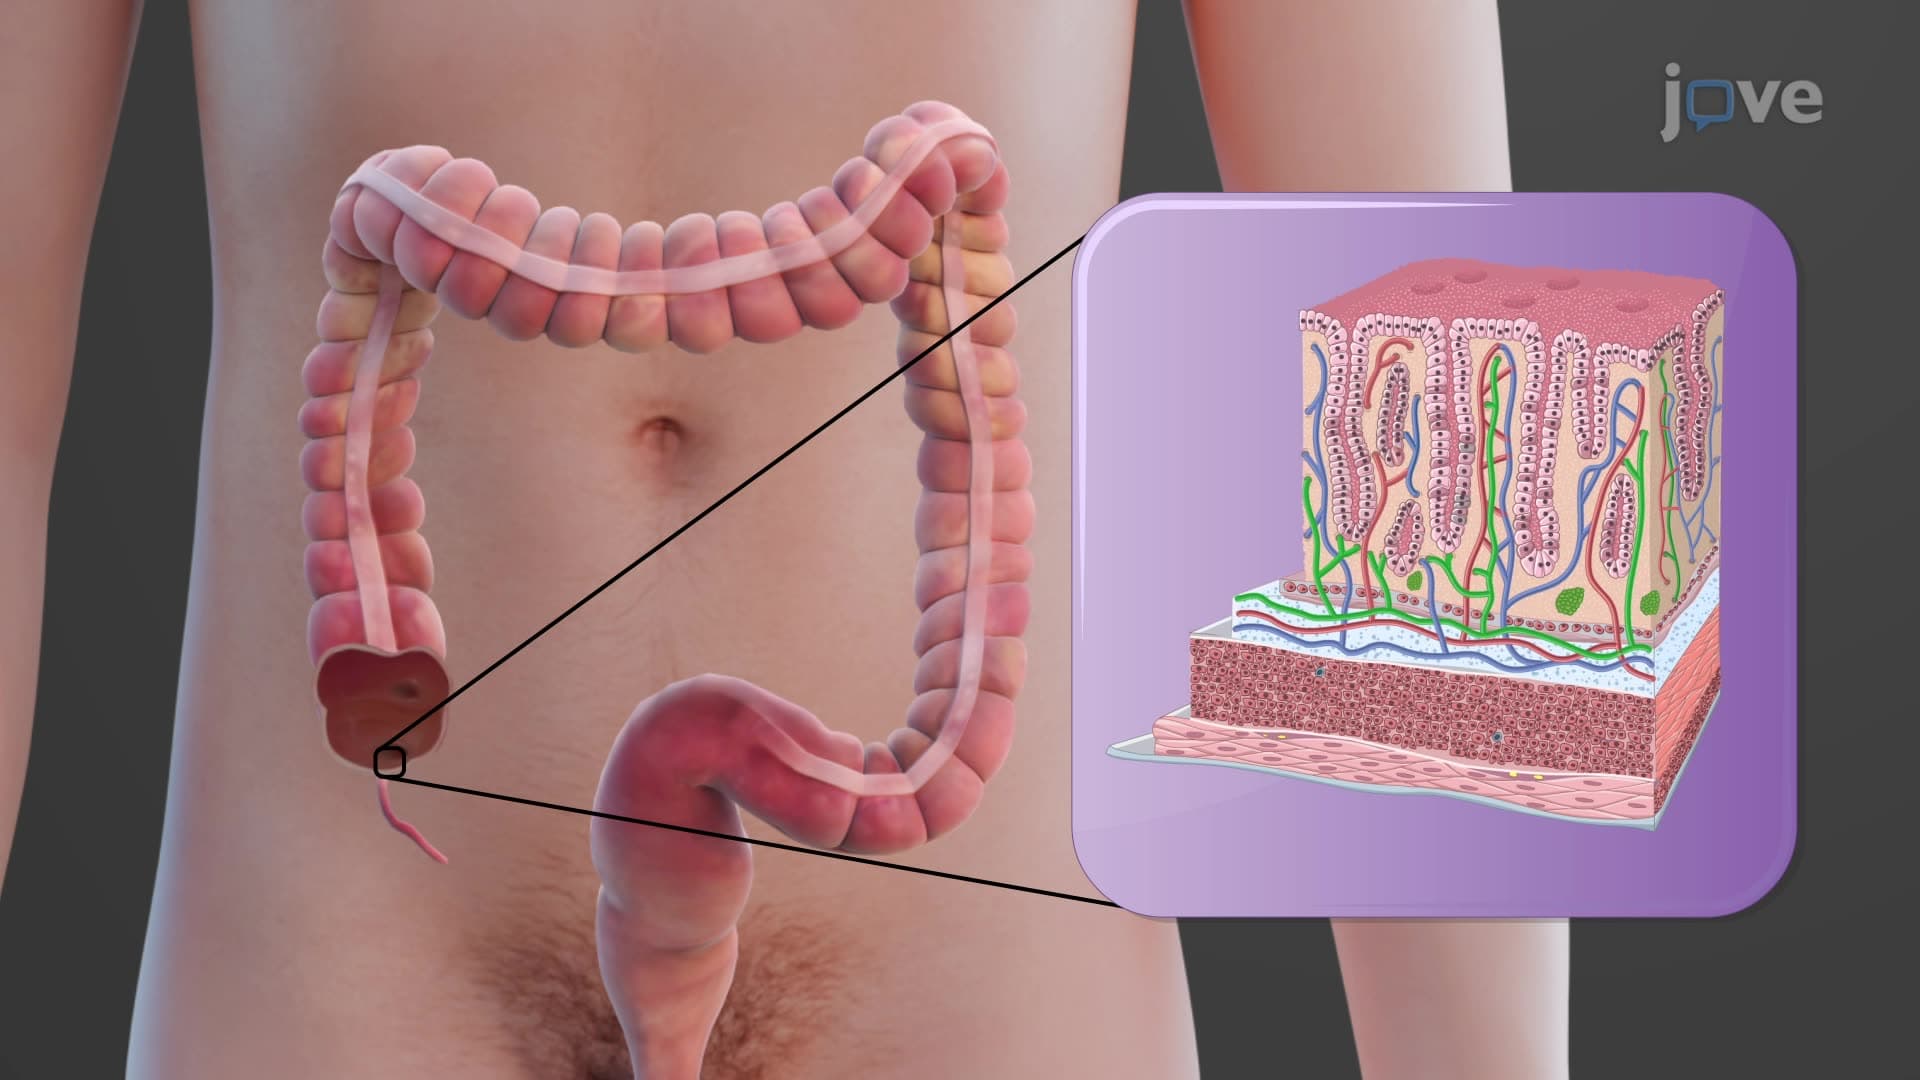
Histology of the Large Intestine
The innermost mucosa layer comprises simple columnar epithelium, lamina propria, and muscularis mucosae. This layer is primarily populated with absorptive cells, tasked with water absorption, and goblet cells, responsible for secreting mucus to...
 01:25
Assessment of the Abdomen I: Inspection and Auscultation
The abdominal examination is a cornerstone of clinical medicine, serving as a critical tool in diagnosing various gastrointestinal (GI) diseases. It involves a systematic approach that includes inspection and auscultation, each with distinct yet complementary roles in assessing the abdomen. This article will delve into these two primary methods healthcare professionals use to examine the abdomen.
Inspection of the Abdomen
The first step in any abdominal examination is inspection....
 01:22
Appendicitis-I: Introduction
Etiology: Appendicitis can arise from various causes, primarily rooted in the obstruction of the appendix lumen. Factors contributing to this obstruction include fecal accumulation, lymphoid hyperplasia and, in...
 01:09
Large Intestine
The ileocecal sphincter, a mucous membrane fold, guards the opening from the ileum to the large intestine. This valve permits material from the small intestine to pass into the large intestine. Attached to the ileocecal valve is the cecum. This small pouch, approximately 6 cm long, has a twisted, coiled tube known as...
 01:21
Inflammatory Bowel Disease V: Surgical Management
Here are some common surgical interventions for IBD: