Related Experiment Video
Updated: Feb 26, 2026
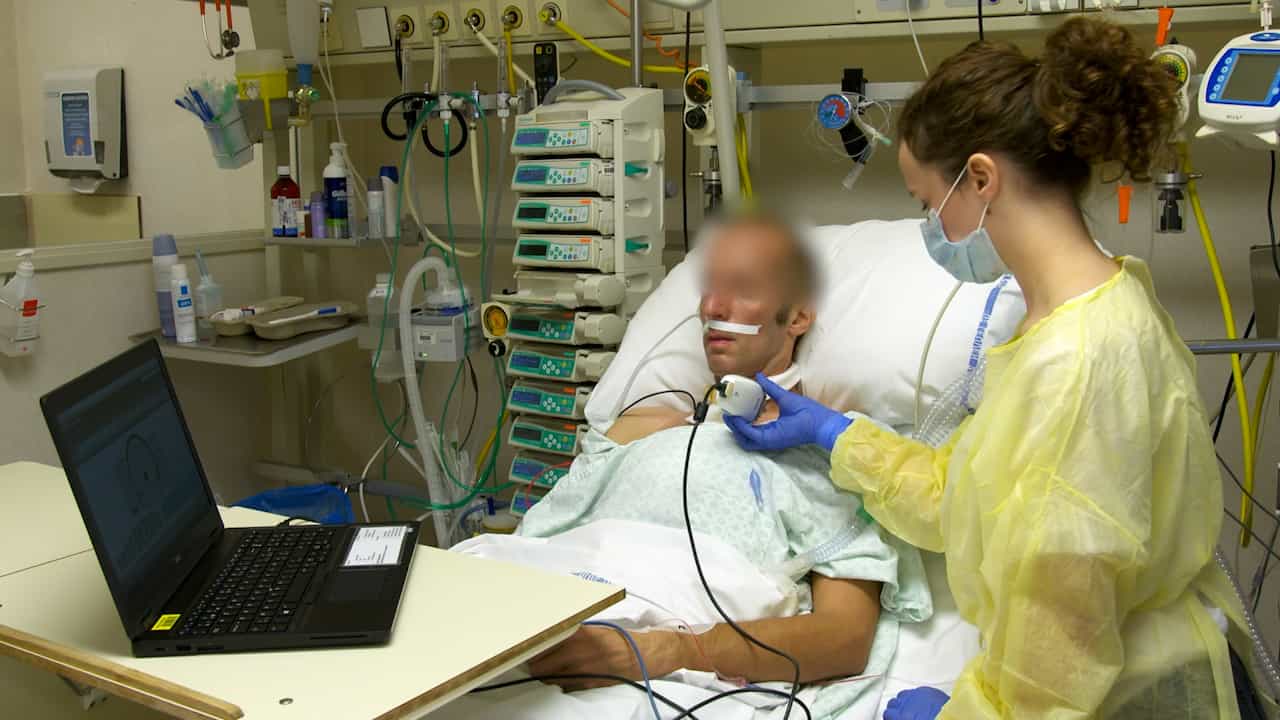

Inspiratory Muscle Training as an Adjunct to the Treatment of Weaning Failure in Critically Ill Patients: A Practical Guide
Published on: January 30, 2026
Weaning from long term continuous positive airway pressure or noninvasive ventilation in children
Meriem Mastouri1,2, Alessandro Amaddeo1,3,4, Lucie Griffon1
1Pediatric Noninvasive Ventilation and Sleep Unit, AP-HP, Hôpital Necker Enfants-Malades, Paris, France.

Insights
Many children can stop long-term continuous positive airway pressure (CPAP) or noninvasive ventilation (NIV). Weaning success depends on the underlying disorder, often requiring surgery, and necessitates long-term follow-up.
Area of Science:
- Pediatric Pulmonology
- Sleep Medicine
- Respiratory Care
Background:
- Long-term use of continuous positive airway pressure (CPAP) and noninvasive ventilation (NIV) is common in children.
- Limited data exists on the ability of children to discontinue these therapies, including the factors influencing successful weaning and patient outcomes.
Purpose of the Study:
- To investigate the underlying disorders, weaning criteria, and clinical outcomes of children who discontinue long-term CPAP or NIV.
- To identify factors associated with successful weaning from respiratory support in pediatric patients.
Main Methods:
- A retrospective cohort study was conducted.
- Consecutive children weaned from long-term CPAP/NIV between October 2013 and January 2016 were analyzed.
- Underlying conditions, weaning protocols, and clinical outcomes were systematically reviewed.
Main Results:
- Of 213 children on long-term CPAP/NIV, 58 (27%) were successfully weaned.
- Common underlying conditions included upper airway anomalies, Prader-Willi syndrome, and bronchopulmonary dysplasia.
- Weaning occurred due to spontaneous improvement (57%), upper airway surgery (24%), or maxillofacial surgery (11%). Relapse of obstructive sleep apnea occurred in 7 patients after a median of 2 years.
Conclusions:
- Discontinuation of long-term CPAP/NIV in children is feasible but highly dependent on the specific underlying disorder.
- While spontaneous improvement can occur, surgical intervention is frequently required for successful weaning.
- Long-term monitoring is crucial for children with underlying conditions requiring respiratory support.
Objectives:
A significant number of children are able to discontinue long term continuous positive airway pressure (CPAP) or noninvasive ventilation (NIV) but the underlying disorders, weaning criteria, and outcome of these children have not been studied.
Study Design:
Retrospective cohort follow up.
Subject Selection:
Consecutive children who were weaned from long term CPAP/NIV between October 2013 and January 2016.
Methodology:
Underlying disorders, weaning criteria, and clinical outcome were analyzed.
Results:
Fifty eight (27%) of the 213 patients on long term CPAP/NIV could be weaned from CPAP/NIV with 50 patients being weaned from CPAP and 8 from NIV. Most patients were young children with upper airway anomalies, Prader Willi syndrome or bronchopulmonary dysplasia. CPAP/NIV was discontinued following spontaneous improvement of sleep-disordered breathing in 33 (57%) patients, upper airway surgery (n = 14, 24%), maxillofacial surgery (n = 6, 11%), neurosurgery (n = 1, 2%), upper airway and neurosurgery (n = 2, 3%), or switch to oxygen therapy (n = 2, 3%). CPAP/NIV was discontinued due to normal nocturnal gas exchange during spontaneous breathing in all patients, with an obstructive apnea-hypopnea index ≤6 events/h on a combined poly(somno)graphy in 27 patients. A relapse of obstructive sleep apnea was observed after a median delay of 2 years in six patients who resumed CPAP and in one patient who underwent midface distraction.
Conclusions:
Weaning from CPAP/NIV is possible in children treated with long term CPAP/NIV but is highly dependent on the underlying disorder. Spontaneous improvement is possible but most children need specific surgery. Long term follow-up is necessary in children with underlying disorders.


Related Concept Videos
 01:23
Mechanical Ventilation III: Noninvasive Ventilation
Noninvasive Positive-Pressure Ventilation...
 01:23
Mechanical Ventilation II: Invasive Ventilation
Negative-Pressure Ventilators
Negative-pressure ventilators create a vacuum around the chest or body to draw air into the lungs, simulating breathing. This method does not require an...
 01:29
Mechanical Ventilation I: Indication and Settings
 01:14
Ventilatory Modes
There are three ventilatory modes: full support, partial support, and spontaneous. These are described below.
Full Support Modes
Full support modes include controlled mechanical ventilation, continuous mandatory...
 01:24
Endotracheal Tube Extubation
Procedure
Extubation removes the endotracheal tube (ETT) from the patient on mechanical ventilation. It requires a well-coordinated, multidisciplinary approach involving physicians, nurses, respiratory therapists, and other healthcare professionals....
 01:29
Suctioning the Nasopharyngeal Airway
Equipment Required