Related Experiment Video
Updated: Feb 26, 2026


Assessment of Child Anthropometry in a Large Epidemiologic Study
Published on: February 2, 2017
Is There an Association Between Cortisol and Hypertension in Overweight or Obese Children?
Aleid Jg Wirix1, Martijn Jj Finken2, Ines A von Rosenstiel-Jadoul3
1VU University Medical Center, EMGO Institute for Health and Care Research, Department of Public and Occupational Health, Amsterdam, The Netherlands.

Insights
Cortisol levels are altered in overweight children, with higher urinary ratios and lower salivary levels. However, these cortisol differences did not directly link to hypertension in overweight or obese children.
Area of Science:
- Pediatric Endocrinology
- Cardiovascular Health
- Metabolic Disorders
Background:
- Hypertension in overweight/obese children lacks clear mechanistic understanding.
- Hypothalamic-pituitary-adrenal axis activity is a potential factor.
- Investigating cortisol's role in pediatric hypertension is crucial.
Purpose of the Study:
- To examine the association between cortisol parameters and hypertension in overweight or obese children.
- To compare cortisol and cortisone levels across hypertensive, normotensive overweight, and normotensive non-overweight children.
Main Methods:
- Collected urine and saliva samples from 3 groups: hypertensive overweight (n=50), normotensive overweight (n=145), and normotensive non-overweight (n=75) children.
- Assessed urinary and salivary cortisol and cortisone levels.
- Analyzed associations with hypertension after adjusting for body mass index-standard deviation score.
Main Results:
- Overweight/obese children had higher urinary cortisol-to-cortisone ratios and cortisol/creatinine ratios compared to non-overweight children.
- Urinary cortisone/creatinine ratio was associated with hypertension after adjustment.
- Salivary cortisol and cortisone levels were lower in overweight/obese children.
- No significant differences in cortisol parameters were found between hypertensive and normotensive overweight/obese children.
Conclusions:
- Findings suggest increased cortisol production and altered renal 11β-hydroxysteroid dehydrogenase 2 activity in overweight/obese children.
- Flattening of early-morning peak cortisol and cortisone observed in overweight/obese children.
- Cortisol parameters did not significantly differentiate hypertensive from normotensive overweight/obese children, indicating other factors may be involved in pediatric hypertension.
Objective:
The precise mechanisms behind the development of hypertension in overweight or obese children are not yet completely understood. Alterations in hypothalamic-pituitary-adrenal axis activity may play a role. We aimed to investigate the association between cortisol parameters and hypertension in overweight or obese children.
Methods:
Random urine (n=180) and early-morning saliva samples (n=126) for assessment of cortisol and cortisone were collected from 1) hypertensive overweight children (n=50), 2) normotensive overweight children (n=145), and 3) normotensive non-overweight children (n=75).
Results:
The age of participants was 10.4±3.3 years and 53% were boys. The urinary cortisol-to-cortisone ratio [β 1.11, 95% confidence interval (CI) 1.05-1.19] as well as urinary cortisol/creatinine (β 1.38, 95% CI 1.09-1.54), and cortisone/creatinine ratios (β 1.26, 95% CI 1.17-1.36) were significantly higher in overweight or obese than in non-overweight children. After adjusting for body mass index-standard deviation score and urinary cortisone/creatinine ratio, but not cortisol/creatinine ratio, was significantly associated with presence of hypertension (β 1.12, 95% CI 1.02-1.23). Salivary cortisol and cortisone levels were significantly lower in overweight or obese than in non-overweight children (β -4.67, 95% CI -8.19- -1.15, and β 0.89, 95% CI 0.80-0.97 respectively). There were no significant differences in cortisol parameters between hypertensive and normotensive overweight or obese children.
Conclusion:
This study provided further evidence for an increased cortisol production rate with decreased renal 11β-hydroxysteroid dehydrogenase 2 activity and flattening of early-morning peak cortisol and cortisone in overweight or obese children. However, there were no significant differences in cortisol parameters between hypertensive and normotensive overweight and obese children.


Related Concept Videos
 01:24
Obesity
 01:27
Adrenal Gland Disorders
Adrenal insufficiency, characterized by insufficient cortisol and aldosterone production, leads to conditions like Addison's disease. This disorder, affecting the adrenal cortex, exhibits symptoms such as skin bronzing, dehydration, low blood pressure, fatigue, and weight loss. Congenital adrenal hyperplasia, a genetic ailment causing...
 01:30
Blood Pressure
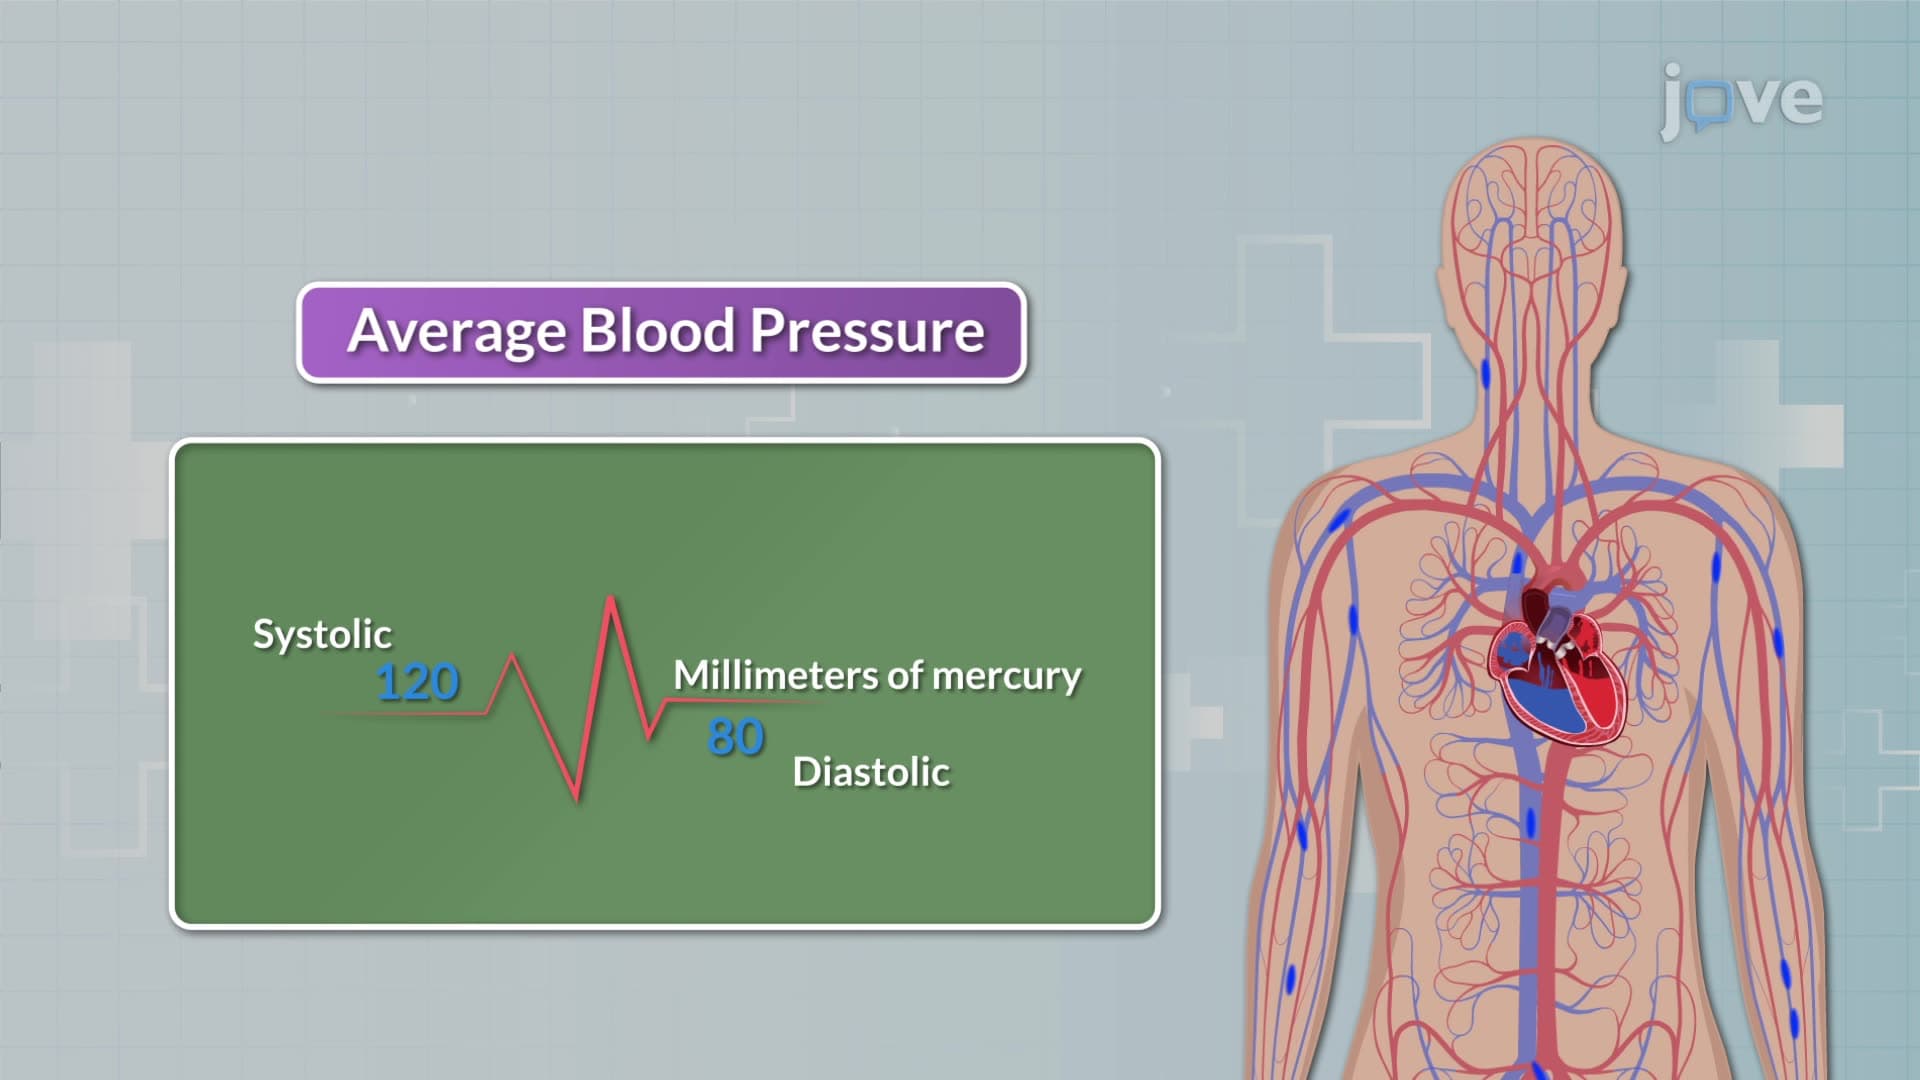
The average BP in an adult is typically around 120/80 mmHg (millimeters of mercury). In this measurement, the numerator (120) indicates the systolic pressure, which is the pressure in the arteries during the contraction of the heart's ventricles as blood is expelled. The denominator (80) represents the...
 01:37
Hypothalamic-Pituitary Axis
 01:27
Psychoneuroimmunology: Cardiovascular Disease
A key area of focus in PNI is the relationship between stress and coronary...
 01:18
Hypertension and Regulation of Blood Pressure