Related Experiment Video
Updated: Feb 26, 2026


Author Spotlight: A Non-Intubated Video-Assisted Thoracoscopic Surgery with Multimodal Analgesia and Sevoflurane Inhalation Anesthesia
Published on: May 26, 2023
Burden of air leak complications in thoracic surgery estimated using a national hospital billing database
Andrew Yoo1, Sudip K Ghosh2, Walter Danker2
1Medical Devices - Epidemiology, Johnson and Johnson, New Brunswick.

Background:
One of the most common outcomes of lung resections are parenchymal air leaks. These air leaks are most often self-limited and spontaneously resolve several days after surgery. Historically, only prolonged air leaks have been considered to have a significant effect on patient outcomes. This study aims to evaluate the impact of any air leak complications (aALCs) on resource utilization and mortality.
Methods:
The Premier Perspective® database was used to identify all elective primary lobectomy, segmentectomy, and wedge resections performed from 2012 to 2014; aALC was defined as a composite of air leak and pneumothorax. Generalized estimating equation models were used to estimate the impact of aALCs on length of stay (LOS), operating room time (ORT), hospital costs, and mortality during index hospitalization.
Results:
A total of 21,150 patients undergoing lung resection surgery were included in the analysis: lobectomy (n=10,946), segmentectomy (n=1,788), and wedge resection (n=8,416). The overall incidence of aALCs was 24.26% (95% CI [23.68, 24.83]). Identified risk factors included resection type, surgical approach, male gender, and presence of COPD. Patients with aALCs had a significantly higher economic burden (adjusted mean [standard error of mean, SE]: LOS=7.24 [SE=0.12] days; ORT=214.9 [SE=6.4] min; and hospital costs=$26,070 [SE=$1404]) compared to those without aALCs (adjusted mean [SE]: LOS=4.75 [SE=0.07] days; ORT=201.7 [SE=3.9] min; and hospital costs=$19,558 [SE=$399]). aALC was also associated with increased overall index hospitalization mortality (odds ratio=1.90, 95% CI [1.42, 2.55]).
Conclusion:
This analysis showed that aALCs are not only frequent but also associated with significantly higher resource utilization and mortality.


Related Concept Videos
 01:27
Pneumothorax-II
Clinical Manifestations:
 01:26
Pneumothorax-I
Pneumothorax can be even further classified as spontaneous, traumatic, and tension pneumothorax.
 01:26
Endoscopic Studies II: Thoracocentesis
Description
Excess pleural fluid or air may accumulate in some respiratory disorders in the thoracic cavity. To treat pleural effusion, a physician conducts thoracentesis by carefully piercing the chest wall and entering...
 01:24
Pressure Relationships in Thoracic Cavity
Breathing Mechanisms
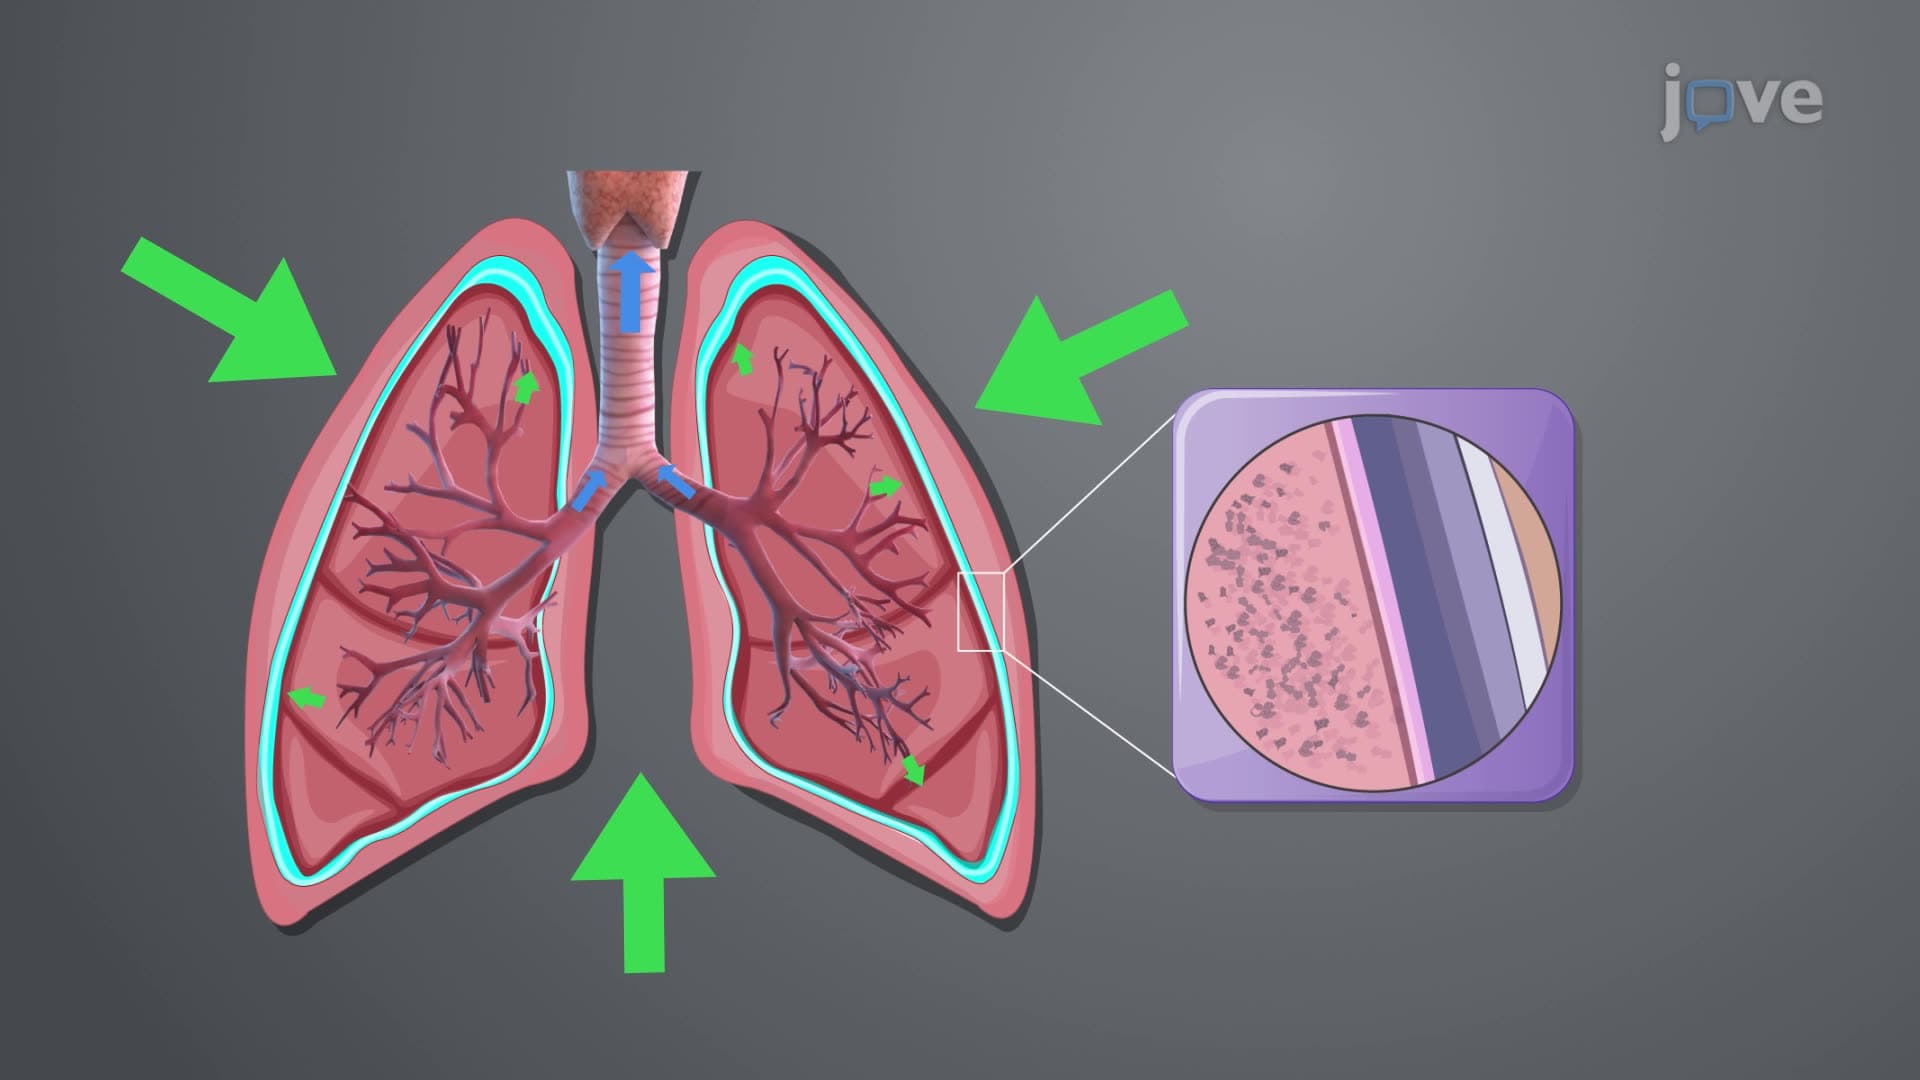
Both intra-alveolar and intrapleural pressures rely on specific lung properties. The ability to breathe—allowing air to enter the lungs...
 01:30
Endoscopic Studies I: Bronchoscopy and Thoracoscopy
Bronchoscopy
Description
Bronchoscopy is a procedure that involves direct visualization of the larynx, trachea, and bronchi for diagnostic and therapeutic purposes. A flexible fiber optic or rigid bronchoscope is used to carry out the procedure. The fiber-optic bronchoscope is more frequently used due...
 01:24
Flail Chest-I
Flail chest is a severe and potentially life-threatening condition characterized by the fracture of three or more adjacent ribs in multiple places. It is most commonly caused by direct impacts and trauma, such as motor vehicle accidents or injuries from a steering wheel impact. It can also occur due to falls in elderly individuals with osteoporosis, or assaults involving sharp objects.
Pathophysiology
The pathophysiology of flail chest is complex, involving fractures of...