Related Experiment Video
Updated: Feb 26, 2026


A Model of Long-Term Ventricular Fibrillation in Isolated Rat Hearts
Published on: February 17, 2023
Prognostic implication of early ventricular fibrillation among patients with ST elevation myocardial infarction
Kristel E Medina-Rodríguez1, Manuel Almendro-Delia, Ángel García-Alcántara
1aDepartment of Cardiology, University Hospital Virgen Macarena, Sevilla bCritical Care Service, University Hospital Virgen de la Victoria, Málaga cCritical Care Unit, Hospital de Antequera dCritical Care Service, University Hospital Regional de Málaga eCritical Care Service, University Hospital Costa del Sol, Málaga fCritical Care Service, University Hospital Jerez gCritical Care Service, University Hospital Puerto Real, Cádiz hCritical Care Service, University Hospital Reina Sofía, Córdoba iCritical Care Service, University Hospital Virgen de las Nieves, Granada, Spain.

Insights
Early ventricular fibrillation (VF) in ST-elevation myocardial infarction (STEMI) patients predicts worse in-hospital outcomes, especially when fibrinolysis is used. However, primary angioplasty negates this increased mortality risk for STEMI patients experiencing VF.
Area of Science:
- Cardiology
- Emergency Medicine
- Clinical Research
Background:
- ST-elevation myocardial infarction (STEMI) is a critical condition requiring prompt intervention.
- Early ventricular fibrillation (VF) is a known complication of STEMI, impacting patient prognosis.
- Understanding the prognostic implications of early VF in STEMI is crucial for guiding treatment strategies.
Purpose of the Study:
- To investigate the prognostic significance of early ventricular fibrillation (VF) in patients with ST-elevation myocardial infarction (STEMI).
- To compare outcomes in STEMI patients with and without early VF, considering different revascularization strategies.
Main Methods:
- Retrospective analysis of STEMI patients from the ARIAM registry admitted within 12 hours and receiving primary revascularization.
- Comparison of in-hospital mortality between patients with and without pre-ICU VF.
- Propensity score matching and logistic regression to assess the independent effect of VF on mortality.
- Subgroup analysis of patients treated with primary angioplasty versus fibrinolysis.
Main Results:
- Of 8340 STEMI patients, 680 (8.2%) presented with early VF. These patients were younger, had fewer comorbidities, but higher rates of Killip class ≥2 and cardiogenic shock.
- Early VF was independently associated with increased in-hospital mortality (OR: 2.08) in the overall cohort.
- After propensity score matching, VF remained associated with higher mortality (OR: 1.53).
- In patients treated with primary angioplasty, VF was not significantly associated with in-hospital mortality (OR: 0.86).
Conclusions:
- Early ventricular fibrillation before ICU admission is an independent predictor of in-hospital mortality in STEMI patients, particularly those treated with fibrinolysis.
- The adverse prognostic impact of early VF in STEMI is not observed in patients undergoing primary angioplasty.
- Primary angioplasty may mitigate the negative prognostic effect of early VF in STEMI management.
Objective:
The aim of this study was to analyze the prognosis of patients presenting early ventricular fibrillation (VF) in the setting of ST elevation myocardial infarction (STEMI).
Patients And Methods:
Among patients included in the ARIAM (Análisis del Retraso en el Infarto Agudo de Miocardio) registry with the diagnosis of STEMI, those who received primary revascularization and were admitted in the first 12 h were analyzed retrospectively.
Results:
From January 2007 to January 2012, 8340 patients were included in the STEMI cohort and 680 (8.2%) of them presented with VF before admission to the ICU (VF). This group comprised younger patients with fewer comorbidities. They received more often primary angioplasty (33.7 vs. 24.9%; P<0.001), had more prevalence of Killip class greater than or equal to 2 at admission (37.5 vs. 17.8%; P<0.001), and suffered more often cardiogenic shock (18.5 vs. 5.9%, P<0.001). By logistic regression analysis, VF was associated with a greater in-hospital mortality [odds rate (OR): 2.08, 95% confidence interval (CI): 1.57-2.81, P<0.001]. After a propensity score matching process, VF was associated with in-hospital mortality (OR: 1.53, 95% CI: 1.05-2.25, P=0.028). However, when analyzing patients treated by primary angioplasty, the mortality was not significantly related to VF (OR: 0.86, 95% CI: 0.45-1.61, P=0.628).
Conclusion:
Our results show that VF before ICU admission was an independent predictor of in-hospital outcome in a cohort of patients in whom fibrinolysis was the most used revascularization therapy. However, this prognostic value was not found in patients treated with primary angioplasty.
More Related Videos
 08:10
Estimating Bilateral Atrial Function by Cardiovascular Magnetic Resonance Feature Tracking in Patients with Paroxysmal Atrial Fibrillation
Published on: July 20, 2022
 04:48
Noninvasive Determination of Vortex Formation Time Using Transesophageal Echocardiography During Cardiac Surgery
Published on: November 28, 2018
Related Concept Videos
 01:25
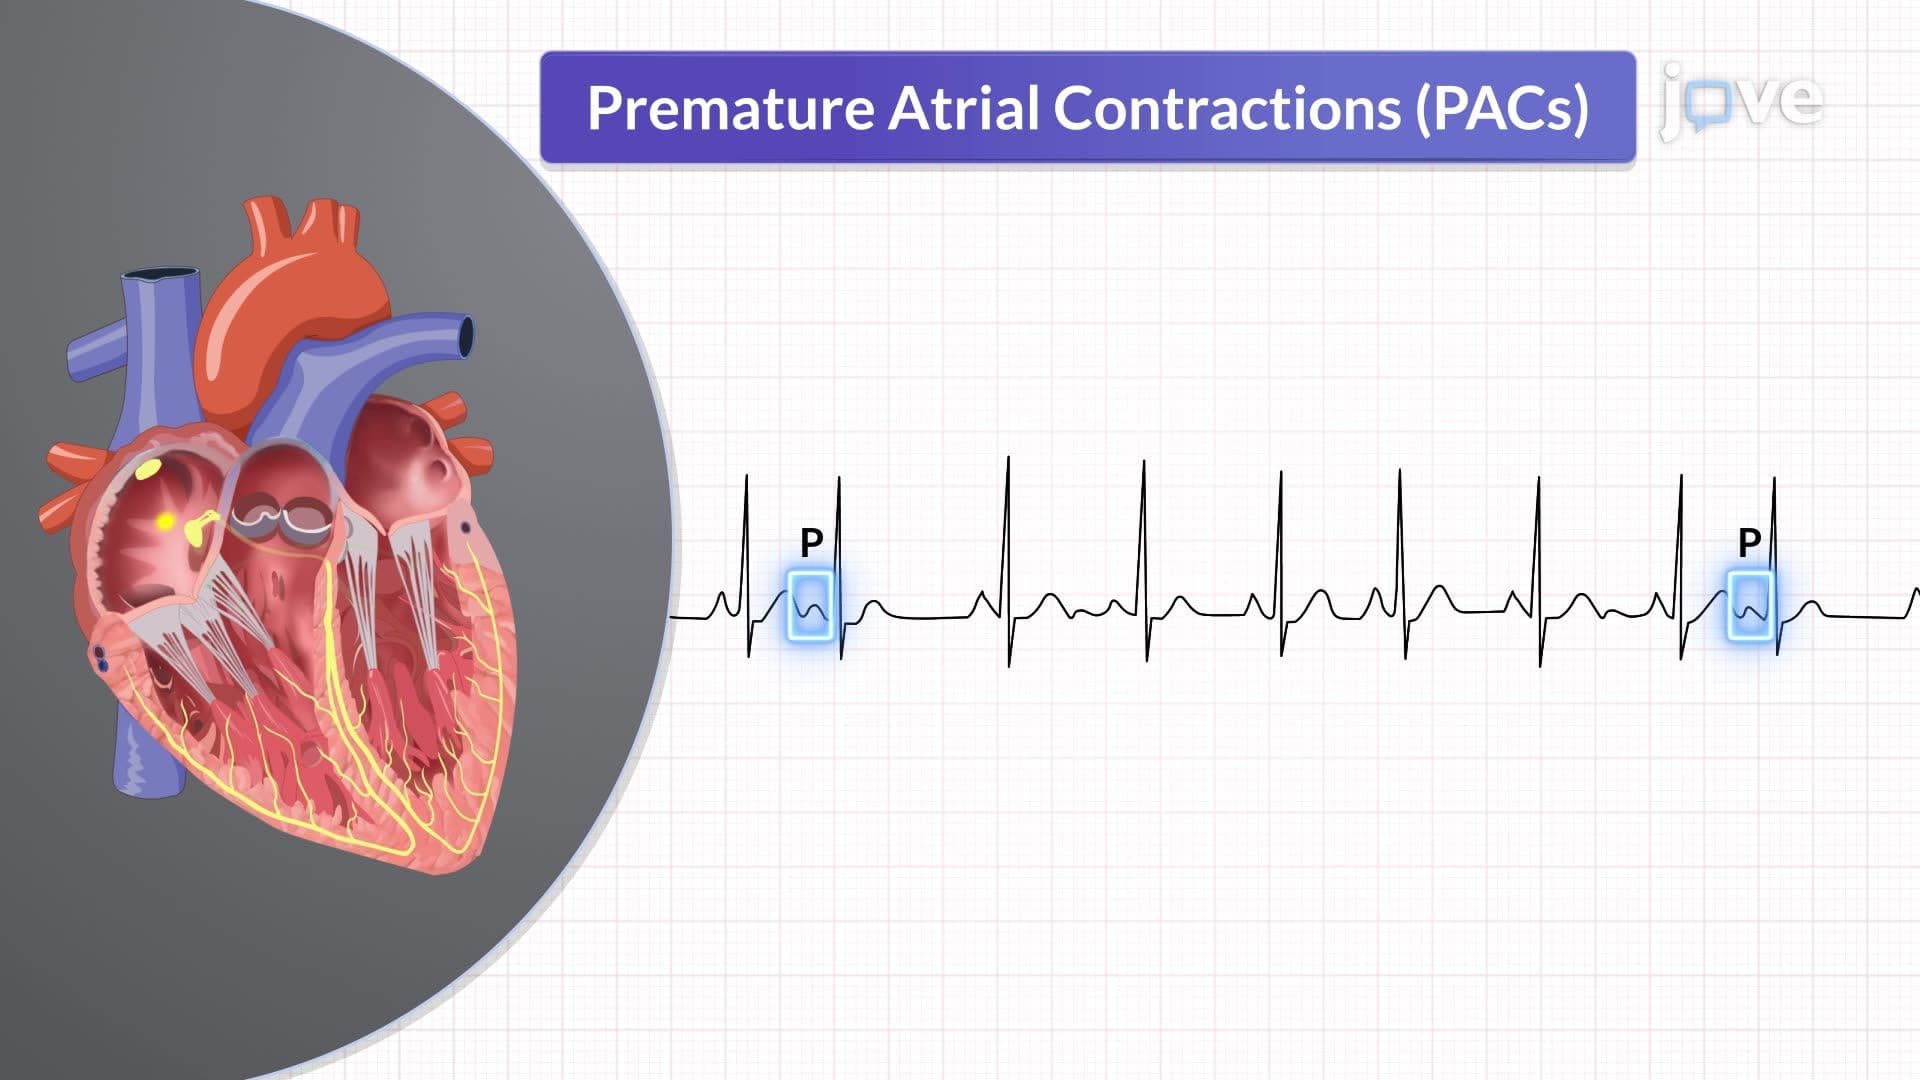
ECG Interpretation of Arrhythmias II: Atrial, Junctional and Ventricular Arrhythmias
 01:29
Dysrhythmias III: Characteristics of Dysrhythmias
 01:29
Disturbances in Heart Rhythm
Arrhythmias are categorized by their speed, rhythm, and origin. A slow heart...
 01:30
Acute Coronary Syndrome I: Introduction
 01:14
Myocarditis III: Medical Management
 01:28
Dysrhythmias II: Classification of Tachyarrhythmias