Related Experiment Video
Updated: Feb 26, 2026
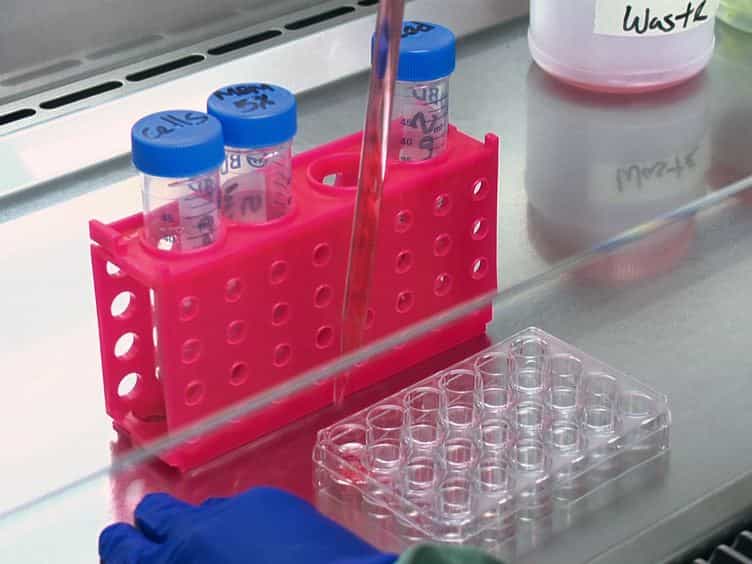

Investigating the Effects of Probiotics on Pneumococcal Colonization Using an In Vitro Adherence Assay
Published on: April 28, 2014
White Blood Cell Counts, Alcoholism, and Cirrhosis in Pneumococcal Pneumonia
Julianna G Gardner1, Divya R Bhamidipati1, Adriana M Rueda1,2
1Departments of Medicine and.

Background:
An elevated white blood cell (WBC) count is a characteristic finding in pneumococcal pneumonia. Very low WBC counts, occurring in some cases, are often associated with overwhelming pneumonia and have been attributed to alcohol-induced suppression of bone marrow. However, a systematic study of neutropenia, leukocytosis, alcohol ingestion, and cirrhosis in pneumococcal pneumonia has not been previously reported.
Methods:
Using a database of patients with pneumococcal pneumonia at our medical center, we extracted data on WBC counts at admission, differential counts, alcohol ingestion, and cirrhosis, and we related these to 7-day and 30-day mortality.
Results:
White blood cell counts were <6000/mm3 in 49 of 481 patients (10.2%) with pneumococcal pneumonia and >25000/mm3 in 40 (8.3%). Mortality at 7 days was 18.4% and 12.5%, respectively, 5-fold and 3-fold greater in patients with WBC <6000 or >25000 than in those with WBC counts between 6000 and 25000 (P < .001). Increased band forms were not associated with a worse outcome (P = .12). Alcohol use and cirrhosis were not associated with WBC counts <6000 (P = .63 and P = .41, respectively).
Conclusions:
In a large series of cases of pneumococcal pneumonia, WBC counts <6000 or >25000 correlated significantly with increased 7-day mortality. More than 10% band forms was not associated with a poor outcome. Alcohol abuse was not associated with low WBC or increased mortality. Our findings suggest that greater consideration be given to more intense care for patients with bacterial pneumonia who have very high or very low WBC counts at the time of hospital admission.

Related Concept Videos
 01:30
Pneumonia III: Complications and Assessment
 01:29
Pneumonia II: Pathophysiology
 01:29
Pulmonary Tuberculosis I
Causative Organism
The primary infectious agent causing tuberculosis is Mycobacterium tuberculosis, a slow-growing, acid-fast, aerobic rod that exhibits sensitivity to heat and ultraviolet light. Instances of Mycobacterium bovis and Mycobacterium avium contributing to the development of TB infection are rare.
Mode of...
 01:30
Pneumonia I: Introduction
Risk Factors
Various factors influence the likelihood of developing pneumonia. Age plays a crucial role, with infants, children under two, and individuals over 65 at increased risk due to their...
 01:27
Disorders of Leukocytes
Leukopenia may result from bone marrow disorders, autoimmune diseases, and infectious diseases. For example, conditions such as multiple myeloma and aplastic anemia can impair the bone marrow's ability to produce adequate leukocytes. Similarly, autoimmune diseases like lupus and viral infections such as HIV can prompt the immune...
 01:27
Chronic Obstructive Pulmonary Disease-IV: Assessement and Diagnostic Studies
Medical History