Related Experiment Video
Updated: Feb 24, 2026
Author Spotlight: Advancing Pelvic Prolapse Treatment with a Non-Mesh Approach using Laparoscopic Pectopexy
Published on: October 25, 2024
Systematic Review of Transabdominal Cerclage Placed via Laparoscopy for the Prevention of Preterm Birth
Gaby N Moawad1, Paul Tyan2, Tracey Bracke3
1Departments of Minimally Invasive Gynecologic Surgery, George Washington University, Washington, DC.

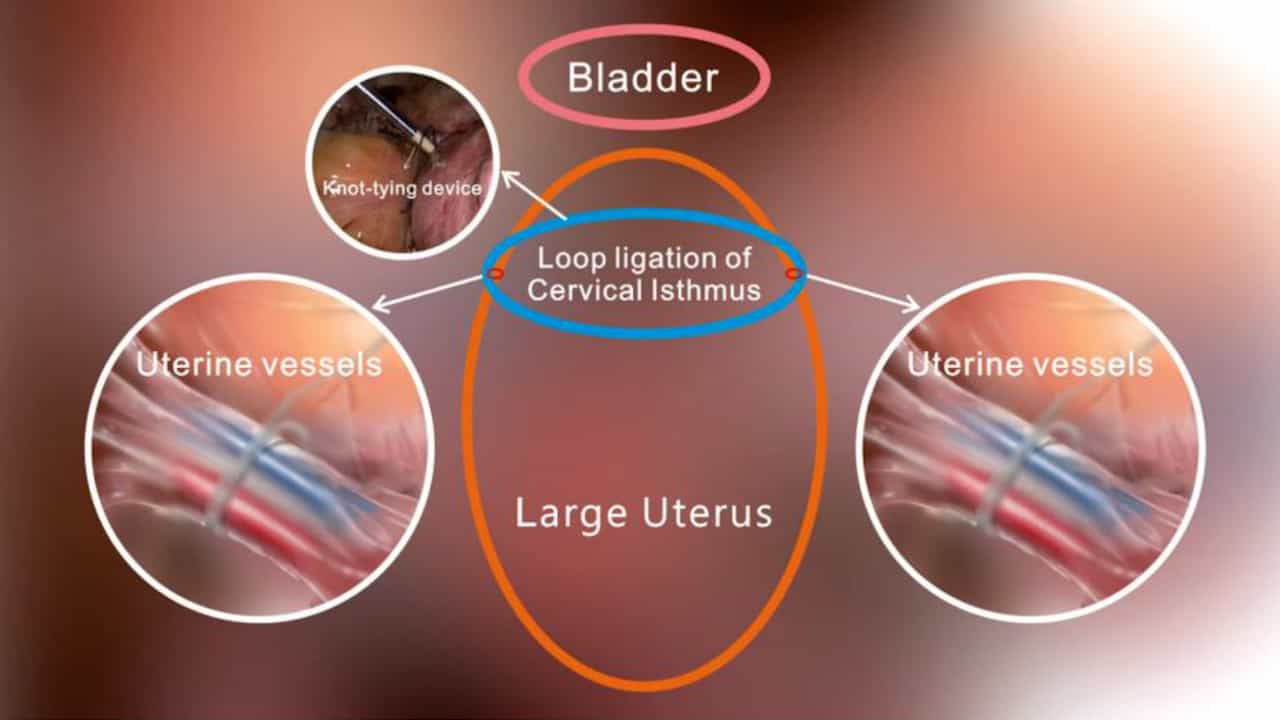
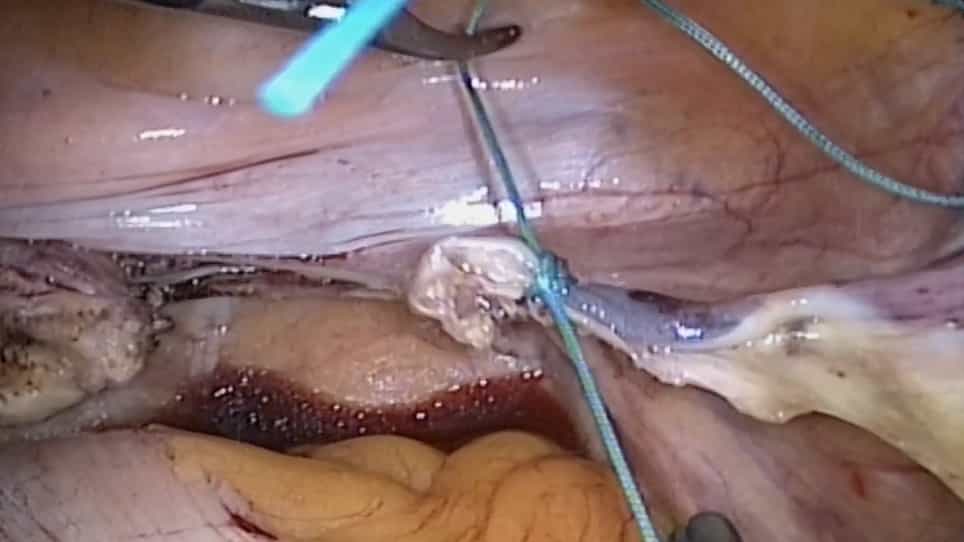
Preterm birth is the leading cause of neonatal mortality and morbidity. Multiple interventions are available to minimize this occurrence; however, despite current recommendations including medical management, cervical length screening, and transvaginal cerclage, a substantial number of women still experience preterm birth. For those patients, experts recommend transabdominal cerclage (TAC). In this systematic review, we compared 26 studies (1116 patients) of TAC placed via laparotomy (TAC-lap) and 15 studies (728 patients) of TAC placed via laparoscopy (TAC-lsc). There was no significant difference in overall neonatal survival between the TAC-lsc and TAC-lap groups (89.9% vs 90.8%, respectively; p = .80). When T1 losses were excluded, the neonatal survival rate was significantly higher for the TAC-lsc group (96.5% vs 90.1%; p < .01). In terms of obstetrical outcomes, the TAC-lsc group had a higher rate of deliveries at gestational age (GA) > 34 weeks (82.9% vs 76%; p < .01) and a lower rate of deliveries at GA 23.0 to 33.6 weeks (6.8% vs 14.8%; p < .01). The TAC-lsc group also had fewer T2 losses (3.2% vs 7.8%; p < .01). TAC-lsc offers all the benefits of minimally invasive surgery with better obstetrical outcomes compared with TAC-lap.
Preterm birth is the leading cause of neonatal mortality and morbidity. Multiple interventions are available to minimize this occurrence; however, despite current recommendations including medical management, cervical length screening, and transvaginal cerclage, a substantial number of women still experience preterm birth. For those patients, experts recommend transabdominal cerclage (TAC). In this systematic review, we compared 26 studies (1116 patients) of TAC placed via laparotomy (TAC-lap) and 15 studies (728 patients) of TAC placed via laparoscopy (TAC-lsc). There was no significant difference in overall neonatal survival between the TAC-lsc and TAC-lap groups (89.9% vs 90.8%, respectively; p = .80). When T1 losses were excluded, the neonatal survival rate was significantly higher for the TAC-lsc group (96.5% vs 90.1%; p < .01). In terms of obstetrical outcomes, the TAC-lsc group had a higher rate of deliveries at gestational age (GA) > 34 weeks (82.9% vs 76%; p < .01) and a lower rate of deliveries at GA 23.0 to 33.6 weeks (6.8% vs 14.8%; p < .01). The TAC-lsc group also had fewer T2 losses (3.2% vs 7.8%; p < .01). TAC-lsc offers all the benefits of minimally invasive surgery with better obstetrical outcomes compared with TAC-lap.