Related Experiment Video
Updated: Feb 23, 2026


Quantification of the Immunosuppressant Tacrolimus on Dried Blood Spots Using LC-MS/MS
Published on: November 8, 2015
Comparative effectiveness and tolerance of immunosuppressive treatments for idiopathic membranous nephropathy: A
Song Ren1, Ying Wang2, Li Xian1
1Renal Division and Institute of Nephrology, Sichuan Academy of Medical Science & Sichuan Provincial People's Hospital, School of Medicine, University of Electronic Science and Technology of China, Chengdu, China.

Background:
Immunosuppressive agents in general are shown to prevent renal progression and all-cause mortality in idiopathic membranous nephropathy (IMN) patients with nephrotic syndrome. However, the efficacy and safety of different immunosuppressive treatments have not been systematic assessed and compared. A network meta-analysis was performed to compare different immunosuppressive treatment in IMN.
Methods:
Cochrane library, MEDLINE, EMBASE and trial register system were searched for randomized controlled trials reporting the treatments for IMN to May 3, 2016. Composite endpoint of mortality or end-stage kidney disease (ESKD), complete or partial proteinuria remission and withdrawal because of treatment adverse events were compared combing direct and indirect comparison using network meta-analysis. Ranking different immunosuppressive treatments in the outcomes were analyzed by using surface under the cumulative ranking curve (SUCRA).
Results:
Total 36 randomized controlled trials (n = 2018) covering 11 kinds of treatments were included. Compared with non-immunosuppressive treatment, only cyclophosphamide (CTX) and chlorambucil significantly reduced the risk of composite outcome of mortality or ESKD while combining the direct and indirect comparison (OR = 0.31, 95%CI: 0.12-0.81 and OR = 0.33, 95%CI: 0.12-0.92). CTX increased the composite outcome of complete remission (CR) or partial remission (PR) (OR = 4.29, 95%CI: 2.30-8.00) but chlorambucil did not (OR = 1.58, 95%CI: 0.80-3.12) as compared with non-immunosuppressive treatment. Chlorambucil also significantly increased the withdrawal risk (OR = 3.34, 95%CI: 1.37-8.17) as compared to CTX. Both tacrolimus (OR = 3.10, 95%CI: 1.36-7.09) and cyclosporine (CsA) (OR = 2.81, 95%CI: 1.08-7.32) also significantly increased the rate of CR or PR as compared with non-immunosuppressive treatment (without significant difference as compared with CTX), while ranking results showed that cyclosporine or tacrolimus was with less possibility of drug withdrawal as compared to CTX.
Conclusions:
Cyclophosphamide and chlorambucil reduce risk of ESKD or death in IMN with nephrotic range proteinuria, but carry substantial toxicity that may be lower for cyclophosphamide. Tacrolimus and cyclosporine increase the possibility of proteinuria remission with less drug withdrawal, but the effects on kidney failure remain uncertain.


Related Concept Videos
 01:26
Nephrotic Syndrome II : Assessment and Medical Management
 01:15
Impact of Pharmacokinetic–Pharmacodynamic Models: Regulatory Decisions
 01:25
Drug Dosing in Renal Diseases: Measurement of Glomerular Filtration Rate
 01:08
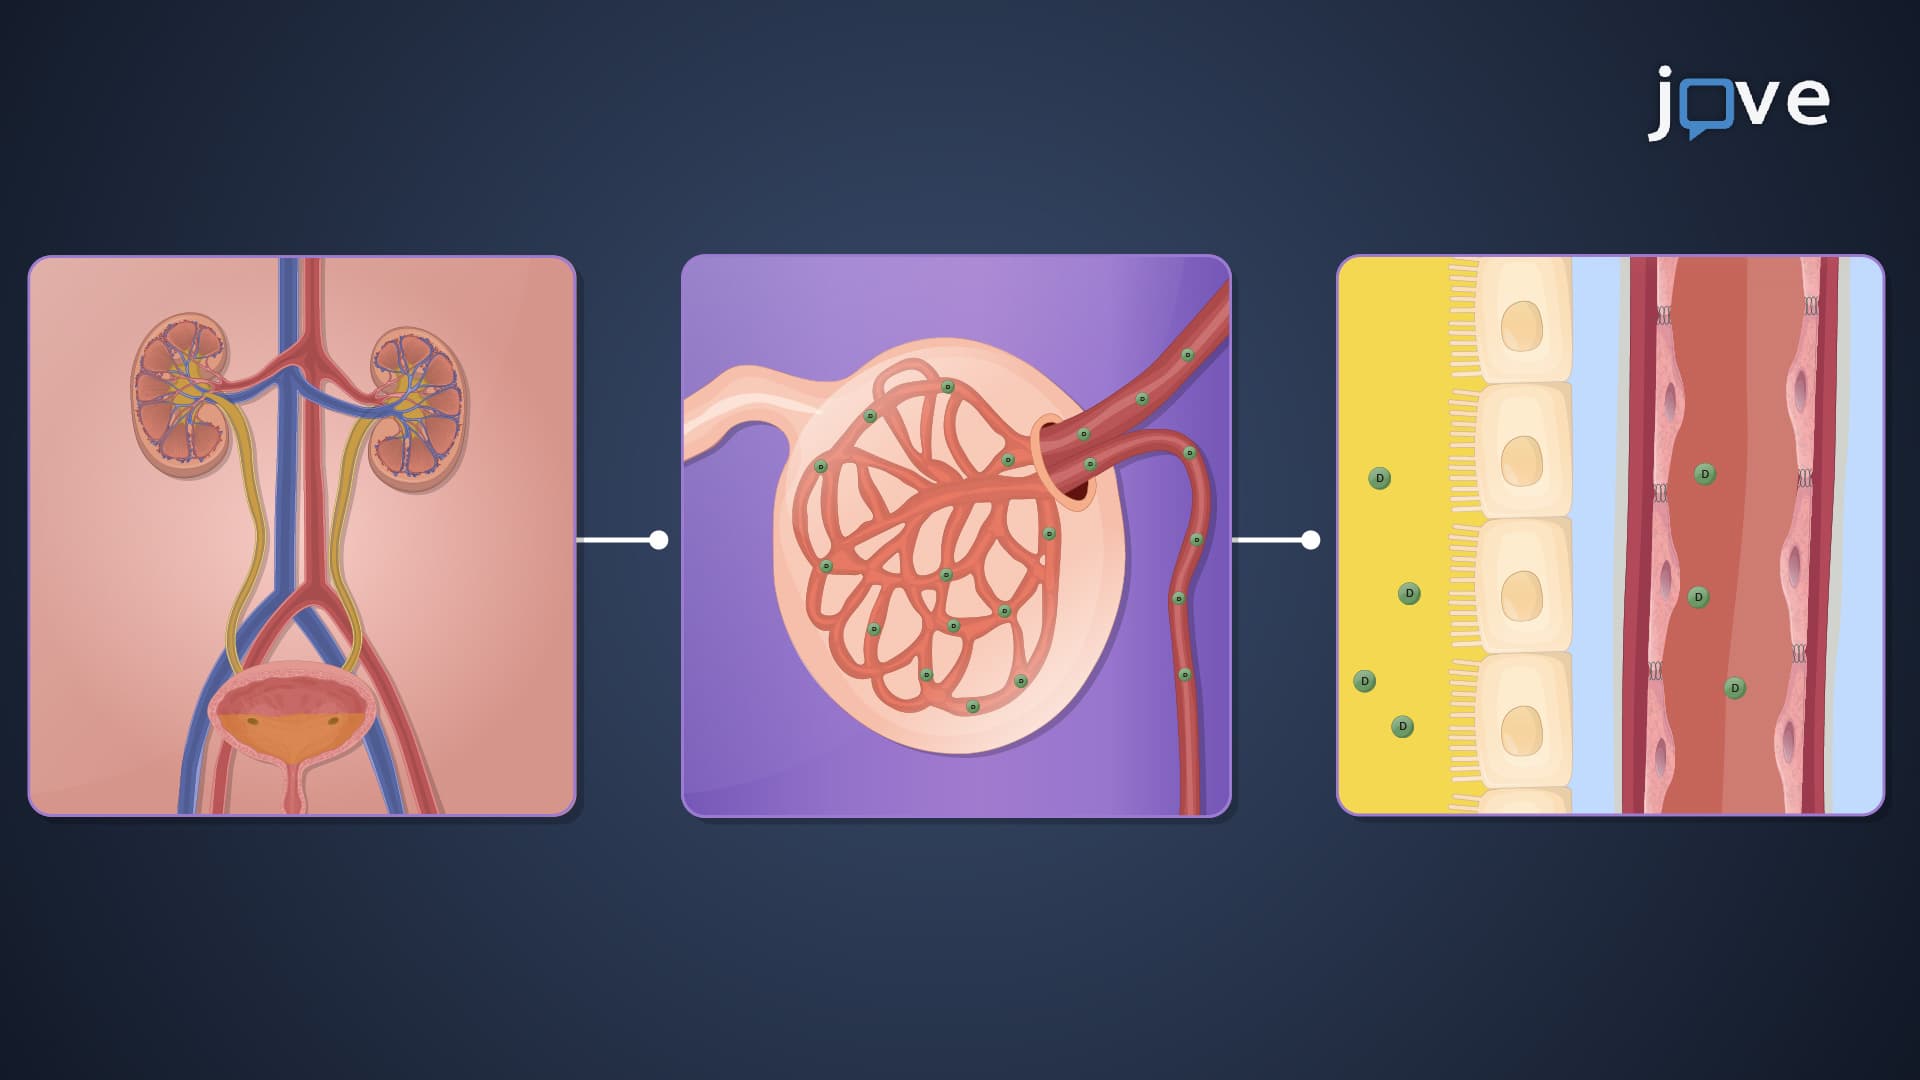
Renal Drug Clearance: Comparison Between Renal Excretion Methods
Renal clearance is often associated with the renal glomerular filtration rate (GFR), which represents the rate at which plasma is filtered through the glomeruli in the kidney. When drug reabsorption is minimal and there is no active secretion, renal clearance is closely related to the...
 01:24
Nephrotic Syndrome I : Introduction