Related Experiment Video
Updated: Oct 11, 2026

Maturation of Human Stem Cell-derived Cardiomyocytes in Biowires Using Electrical Stimulation
Published on: May 6, 2017
Isolated septal myectomy for hypertrophic obstructive cardiomyopathy: an update on the Toronto General Hospital
Rachel D Vanderlaan1, Anna Woo2, Anthony Ralph-Edwards1,3
1Division of Cardiac Surgery, the University of Toronto, Toronto, Canada.

Insights
Isolated septal myectomy is a safe and effective treatment for hypertrophic obstructive cardiomyopathy (HOCM). This procedure successfully reduces left ventricular outflow tract obstruction, even in patients with thin septal thickness.
Area of Science:
- Cardiology
- Cardiac Surgery
- Cardiovascular Disease
Background:
- Isolated septal myectomy is the gold standard for treating refractory left ventricular outflow tract (LVOT) obstruction in hypertrophic obstructive cardiomyopathy (HOCM).
- This study updates the Toronto General Hospital (TGH) experience with isolated septal myectomy.
- It evaluates the safety and efficacy of myectomy in patients with thin basal septal thickness.
Purpose of the Study:
- To assess the outcomes of isolated septal myectomy in patients with HOCM.
- To determine the safety and efficacy of the procedure, particularly in patients with thin basal septal thickness.
- To analyze the impact of myectomy on LVOT obstruction, mitral valve function, and procedural complications.
Main Methods:
- Retrospective review of patients undergoing surgical myectomy from January 2012 to August 2016.
- Analysis of patient characteristics, intraoperative variables, and pre- and post-procedural echocardiographic parameters.
- Evaluation of key outcomes including stroke, renal failure, iatrogenic ventricular septal defect (VSD), pacemaker insertion, and mortality.
Main Results:
- 150 isolated septal myectomy surgeries were performed.
- Preoperative basal septal thickness averaged 2.10 cm with significant LVOT gradients.
- Post-procedure, septal thickness reduced to 1.04 cm with negligible gradients, and mitral regurgitation and systolic anterior motion (SAM) significantly improved. Outcomes were similar for patients with thin (<1.7 cm) and thicker septa.
- No iatrogenic VSDs occurred; 5.3% required permanent pacemakers, and there was one early death.
Conclusions:
- Isolated septal myectomy is a safe and effective procedure for HOCM.
- The operation achieves excellent results regardless of basal septal thickness when performed by experienced surgeons at a dedicated HCM center.
- Myectomy effectively reduces LVOT obstruction and improves mitral valve function in HOCM patients.
Background:
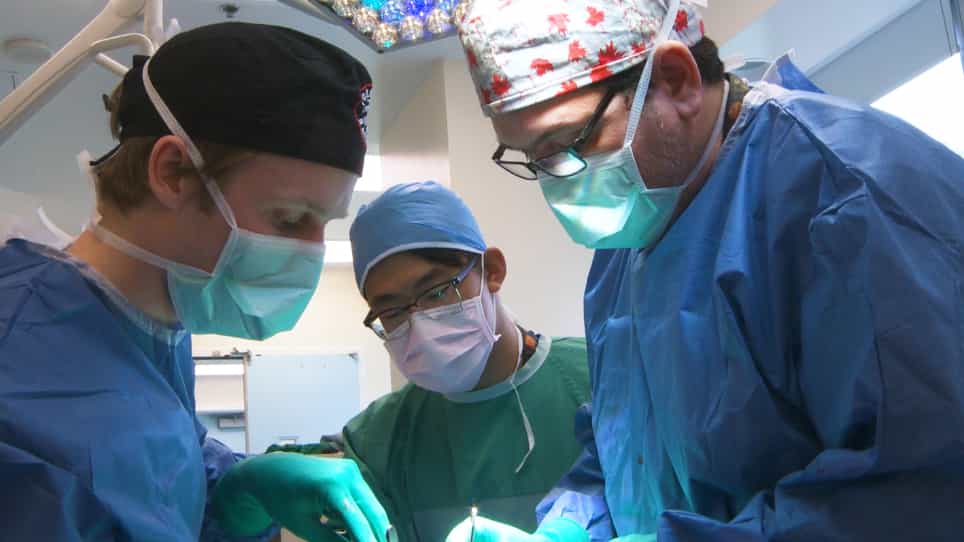
Isolated septal myectomy is considered the gold standard for refractory left ventricular outflow tract (LVOT) obstruction at centers with dedicated hypertrophic obstructive cardiomyopathy (HOCM) surgeons. In this paper, we provide an update on the Toronto General Hospital (TGH) experience for isolated septal myectomy and comment on the safety and efficacy of myectomy in patients with thin basal septal thickness at our institution.
Methods:
We retrospectively reviewed all patients undergoing surgical myectomy at our institution from January 2012 to August 2016. We analyzed patient characteristics, intraoperative variables, pre- and post-procedural echocardiographic parameters, and key outcomes including post-operative stroke, renal failure, iatrogenic ventricular septal defect (VSD), post-procedure insertion of permanent pacemaker, and mortality.
Results:
At our institution, 150 isolated septal myectomy surgeries were performed over the study period. Preoperative echocardiography demonstrated an average basal septal thickness of 2.10±0.43 cm with a resting gradient of 67±37 mmHg and a provoked gradient of 89±40 mmHg. Fifty percent of patients had significant systolic anterior motion (SAM) of their mitral valve and 53% had associated moderate to severe mitral regurgitation (MR). Of note, 24% of patients had a thin septum of ≤1.7 cm. Discharge echocardiograms demonstrated significant septal reduction to an average basal septal thickness of 1.04±0.26 (P<0.05), with negligible resting and provokable LVOT gradients. At the time of discharge, none of the patients had significant SAM and only 5.3% of patients had residual greater than mild MR. Patients undergoing isolated myectomy with a thin basal septum had similar outcomes to those with a >1.7 cm septal thickness. In our contemporary cohort, there were no iatrogenic VSDs, 5.3% of patients required a permanent pacemaker and there was one early death.
Conclusions:
Our cohort demonstrates that isolated septal myectomy remains a safe and effective operation that can achieve excellent results, irrespective of basal septal thickness, when done by experienced surgeons in a dedicated hypertrophic cardiomyopathy (HCM) center.

Related Concept Videos
 01:22
Mitral Stenosis I: Introduction
 01:26
Mitral Stenosis III: Medical Management
 01:29
Cardiomyopathy III: Hypertrophic Cardiomyopathy
 01:29
Cardiomyopathy IV: Restrictive Cardiomyopathy
 01:29
Cardiomyopathy V: Interprofessional Care
 01:28
Cardiomyopathy VII: Pre and Post Operative Nursing Management