Growth Kinetics of Small Renal Masses on Active Surveillance: Variability and Results from the DISSRM Registry
Related Experiment Video
Updated: Feb 22, 2026
In Vivo, Percutaneous, Needle Based, Optical Coherence Tomography of Renal Masses
Published on: March 30, 2015
Akachimere C Uzosike1, Hiten D Patel1, Ridwan Alam1
1The James Buchanan Brady Urological Institute, The Johns Hopkins Hospital (ACU, HDP, RA, MAG, MHJ, HG, MFR, BJT, MEA, PMP), Baltimore, Maryland; Division of Urology, Beth Israel Deaconess Medical Center (PC, AAW), Boston, Massachusetts; Department of Urology, Columbia University Medical Center (JMM), New York, New York.

Purpose:
Active surveillance is emerging as a safe and effective strategy for the management of small renal masses (4 cm or less). We characterized the growth rate and its pertinence to clinical outcomes in a prospective multi-institutional study of patients with small renal masses.
Materials And Methods:
Since 2009, the DISSRM (Delayed Intervention and Surveillance for Small Renal Masses) prospective, multi-institutional registry of patients with small renal masses has enrolled patients who elect primary intervention or active surveillance. Patients who elect active surveillance received regularly scheduled imaging and those with 3 or more followup images were included in the current study to evaluate growth rates.
Results:
We evaluated 318 patients who elected active surveillance, of whom 271 (85.2%) had 3 or more followup images available with a median imaging followup of 1.83 years. The overall mean ± SD small renal mass growth rate was 0.09 ± 1.51 cm per year (median 0.09) with no variables demonstrating statistically significant associations. The growth rate and variability decreased with longer followup (0.54 and 0.07 cm per year at less than 6 months and greater than 1 year, respectively). No patients had metastatic disease or died of kidney cancer. No statistically significant difference was noted in the growth rate in patients with biopsy demonstrated renal cell carcinoma or in those who died.
Conclusions:
Small renal mass growth kinetics are highly variable early on active surveillance with growth rates and variability decreasing with time. Early in active surveillance, especially during the initial 6 to 12 months, the growth rate is variable and does not reliably predict death or adverse pathological features in the patient subset with available pathology findings. An elevated growth rate may indicate the need for further assessment with imaging or consideration of biopsy prior to progressing to treatment. Additional followup will inform the best clinical pathway for elevated growth rates.
Insights
Active surveillance for small renal masses shows variable growth rates initially, which stabilize over time. This strategy is safe, with no observed deaths or metastatic disease linked to growth rate in this study.
Area of Science:
- Urology
- Oncology
- Nephrology
Background:
- Active surveillance is a growing strategy for managing small renal masses (≤4 cm).
- Understanding growth rate is crucial for refining surveillance protocols.
Purpose of the Study:
- To characterize the growth rate of small renal masses during active surveillance.
- To assess the relationship between growth rate and clinical outcomes.
Main Methods:
- Prospective, multi-institutional study (DISSRM registry).
- Included 318 patients electing active surveillance with ≥3 follow-up images.
- Analyzed imaging data to determine small renal mass growth rates.
Main Results:
- Mean growth rate was 0.09 ± 1.51 cm/year, decreasing with longer follow-up.
- Growth rate variability diminished over time (e.g., 0.54 cm/yr <6 months vs. 0.07 cm/yr >1 year).
- No statistically significant associations found between growth rate and adverse outcomes or pathology.
Conclusions:
- Small renal mass growth is highly variable early in surveillance, stabilizing over time.
- Initial growth rates do not reliably predict adverse outcomes.
- Elevated early growth may warrant further assessment or biopsy.
More Related Videos

Related Concept Videos
 01:06
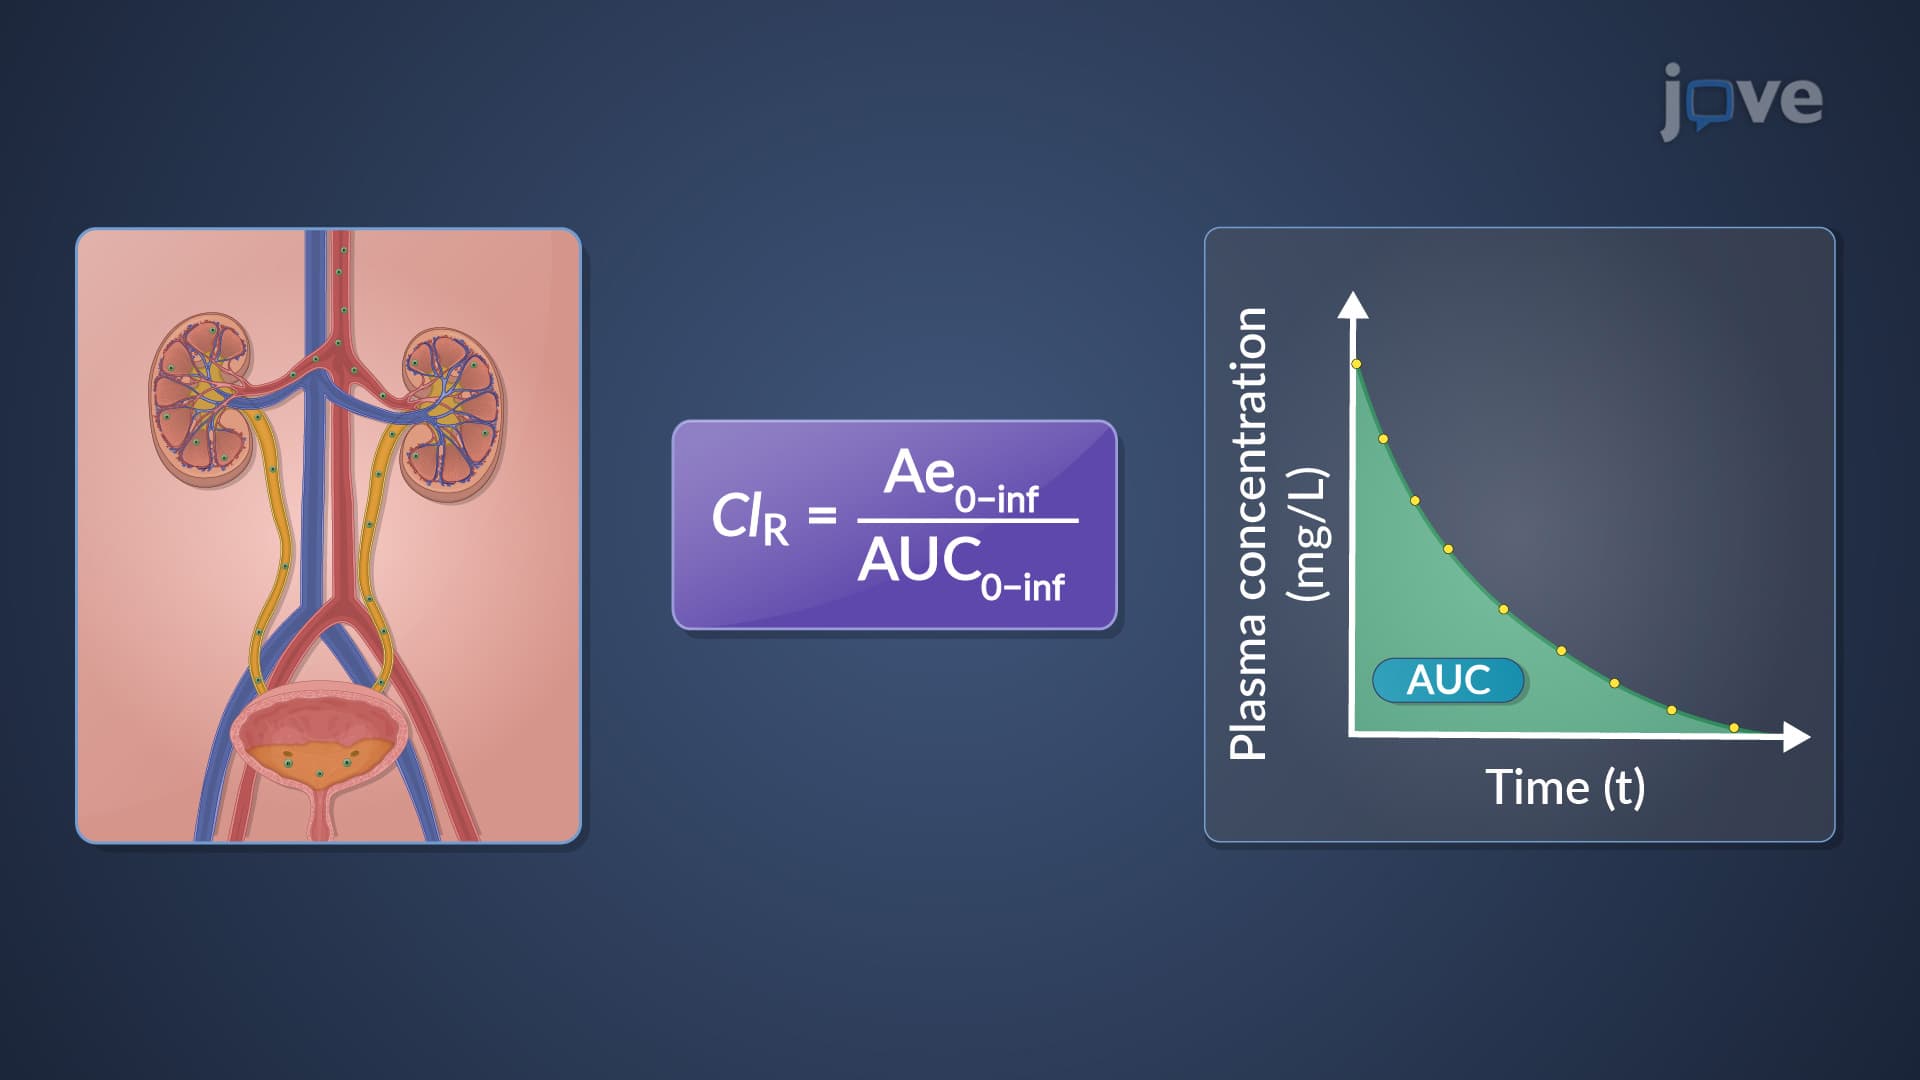
Renal Drug Clearance: Overview
Renal clearance can be calculated using different methods. One approach is to divide the urinary drug excretion rate by the plasma drug concentration. This method directly measures renal clearance, indicating the kidneys' efficiency in...
 01:23
Renal Clearance
Renal clearance refers to the volume of plasma cleared of a specific substance, such as creatinine, per unit of time. To measure clearance, urine samples are collected over a 24-hour period during each bladder voiding, followed by a single blood sample at the...
 01:29
Acute Kidney Injury III: Clinical Manifestations
 01:30
Acute Kidney Injury IV: Diagnostic Studies and Prevention
 01:28
Renal Drug Excretion: Tubular Secretion
 01:07
Determination of Renal Drug Clearance: Graphical and Midpoint Methods
The graphical method involves plotting the rate of drug excretion in urine against the plasma drug concentration. By analyzing the graph, the clearance can be calculated and obtained. Drugs rapidly excreted by the kidneys exhibit a...