Related Experiment Video
Updated: Feb 22, 2026
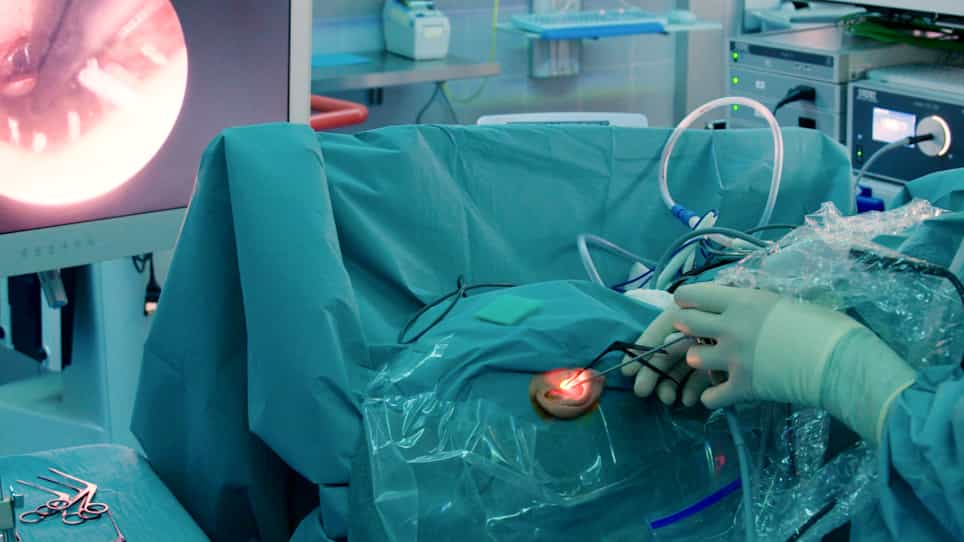

Endoscopic Cholesteatoma Surgery
Published on: January 19, 2022
Risk Factors of Recurrence in Pediatric Congenital Cholesteatoma
Yuka Morita1, Kuniyuki Takahashi, Shuji Izumi
1*Department of Otolaryngology Head and Neck Surgery, Graduate School of Medical and Dental Sciences, Niigata University, Niigata †Department of Otorhinolaryngology, The Jikei University School of Medicine, Tokyo, Japan.

Insights
Pediatric congenital cholesteatoma recurrence is often residual, highlighting the importance of complete epithelial removal. Advanced lesions and young patients require careful monitoring with computed tomography (CT) to detect recurrence.
Area of Science:
- Otolaryngology
- Pediatric Surgery
- Medical Imaging
Background:
- Congenital cholesteatoma is a destructive epidermal growth in the middle ear.
- Recurrence poses a significant challenge in pediatric cases, necessitating effective risk factor identification.
Purpose of the Study:
- To identify risk factors associated with recurrence in pediatric congenital cholesteatoma.
- To evaluate the efficacy of computed tomography (CT) in detecting recurrent cholesteatoma.
Main Methods:
- Retrospective chart review of 67 pediatric patients (<15 years) with congenital cholesteatoma.
- Surgical interventions included canal wall-up tympanomastoidectomy or transcanal atticotomy/tympanoplasty.
- Follow-up involved second-look surgery and/or computed tomography (CT) for recurrence detection.
Main Results:
- Residual cholesteatoma was the primary form of recurrence (21%), while retraction cholesteatoma occurred in 6%.
- Advanced Potsic stage and stapes involvement were linked to residual cholesteatoma.
- Young age, male sex, and advanced stage (IV) were associated with retraction cholesteatoma.
Conclusions:
- Computed tomography (CT) is recommended for follow-up of congenital cholesteatoma due to its effectiveness in detecting residual lesions.
- Complete epithelial removal is crucial for preventing residual cholesteatoma, especially in advanced cases.
- Preserving healthy mucosa is important in young, advanced-stage patients to minimize the risk of retraction cholesteatoma.
Objective:
To examine the risk factors of recurrence in pediatric congenital cholesteatoma.
Study Design:
Retrospective chart review.
Setting:
University hospital.
Patients:
Sixty-seven patients having tympanic type of congenital cholesteatoma under 15-years old at surgery.
Interventions:
Canal wall-up tympanomastoidectomy (n = 30) or transcanal atticotomy/tympanoplasty (n = 37) was performed depending on cholesteatoma extension, 16 of which were followed by second-look surgery. Preoperative computed tomography (CT) before second-look surgery or follow-up CT was performed to detect residual recurrence 1 year after the surgery. Cholesteatoma found at the second surgery was also included in the recurrence. All patients had no recurrent cholesteatoma at the last follow-up (median, 61 mo after surgery).
Main Outcome Measures:
Possible predictive factors were compared between the groups.
Results:
Residual cholesteatoma and retraction cholesteatoma occurred in 21 and 6%, respectively. There was no significant difference in age, sex, and type of cholesteatoma (open or closed) between the groups; however, Potsic stage and status of stapes involvement were more advanced in the residual cholesteatoma group. All residual lesions could be detected by follow-up CT or by second-look surgery. All of four retraction cholesteatoma patients were male, young at the surgery and in stage IV.
Conclusion:
Recurrence mostly occurred as residual cholesteatoma, suggesting that CT is recommended as a follow-up tool for congenital cholesteatoma. Advanced lesions had the risk of residual cholesteatoma, suggesting that complete removal of epithelium is important. Although rare, young advanced-stage patients had risk of retraction cholesteatoma and therefore normal mucosa should be preserved as much as possible for these patients.
Related Concept Videos
 01:26
Factors Affecting the Risk of Infection
The integrity and count of the white blood cells help the body resist pathogens and fight infection. When impaired, it reduces the body's resistance to pathogens. The acidic pH levels of the gastrointestinal, genitourinary tracts, and skin...
 01:27
Pneumothorax-II
Clinical Manifestations:
 01:30
Esophageal Strictures-I: Introduction
Etiology
The primary cause of esophageal strictures is long-standing gastroesophageal reflux disease (GERD), accounting for about 70 to 80% of adult cases. Chronic acid reflux can lead to injury and scarring of the esophageal lining, culminating in...