Related Experiment Video
Updated: Feb 21, 2026


Author Spotlight: Evaluating Therapeutic Strategies to Enhance Liver Regeneration
Published on: May 24, 2024
AKI persistence at 48 h predicts mortality in patients with acute on chronic liver failure
Rakhi Maiwall1, Guresh Kumar2, Ankit Bharadwaj2
1Department of Hepatology, Institute of Liver and Biliary Sciences, New Delhi, 110070, India.

Background And Aim:
Management of acute kidney injury (AKI) in cirrhotics has undergone a paradigm change. We evaluated the impact of AKI persistence at 48 h on outcome in patients with acute on chronic liver failure (ACLF).
Methods:
Consecutive patients with ACLF (n = 373) were prospectively followed. AKI was defined as increase in serum creatinine of 0.3 mg/dl or 1.5- to 2-fold from baseline. Persistent AKI was defined as nonresponsive AKI at 48 h with respect to admission serum creatinine.
Results:
AKI at admission was present in 177 (47.5 %) patients. At 48 h, 73 % patients had persistent AKI and 27 % had responsive AKI. High Model for End-Stage Liver Disease (MELD) (≥26) [p, odds ratio (OR), 95 % confidence interval (CI)] [<0.001, 3.65 (2.1-3.67)], systemic inflammatory response syndrome (SIRS) [0.03, 1.6 (1.02-21.6)], and age (≥42 years) [0.03, 1.84 (1.19-2.85)] were significant predictors of AKI persistence. Persistent AKI was associated with significantly higher in-hospital mortality [p < 0.001, hazard ratio (HR) 1.7, 95 % CI 1.32-2.27]. We further found a lower cutoff for serum creatinine of 1.14 mg/dl at 48 h with better sensitivity of 61 %, specificity of 61 %, and likelihood ratio (LR+) of 1.6, correctly classifying 61 %, as against the conventional cutoff of 1.5 mg/dl with sensitivity of 37 %, specificity of 57 %, and LR+ of 3.3, correctly classifying 56 %. This new cutoff also predicted mortality with higher odds (OR 2.4, 95 % CI 1.3-4.8) as compared with the conventional cutoff (OR 2.1, 95 % CI 1.1-4.1).
Conclusion:
AKI persistence at 48 h predicts mortality better than serum creatinine of 1.5 mg/dl in patients with ACLF. Serum creatinine value of 1.14 mg/dl and smaller increases in its value should be considered for risk stratification of patients with ACLF for interventional strategies.


Related Concept Videos
 01:22
Effect of Hepatic Disease on Pharmacokinetics: Pathophysiologic Assessment and Liver Function Test
 01:26
Effect of Hepatic Disease on Pharmacokinetics: Drug Dosing and Hepatic Blood Flow
 01:29
Acute Kidney Injury III: Clinical Manifestations
 01:30
Acute Pancreatitis II: Clinical Manifestations and Management
 01:14
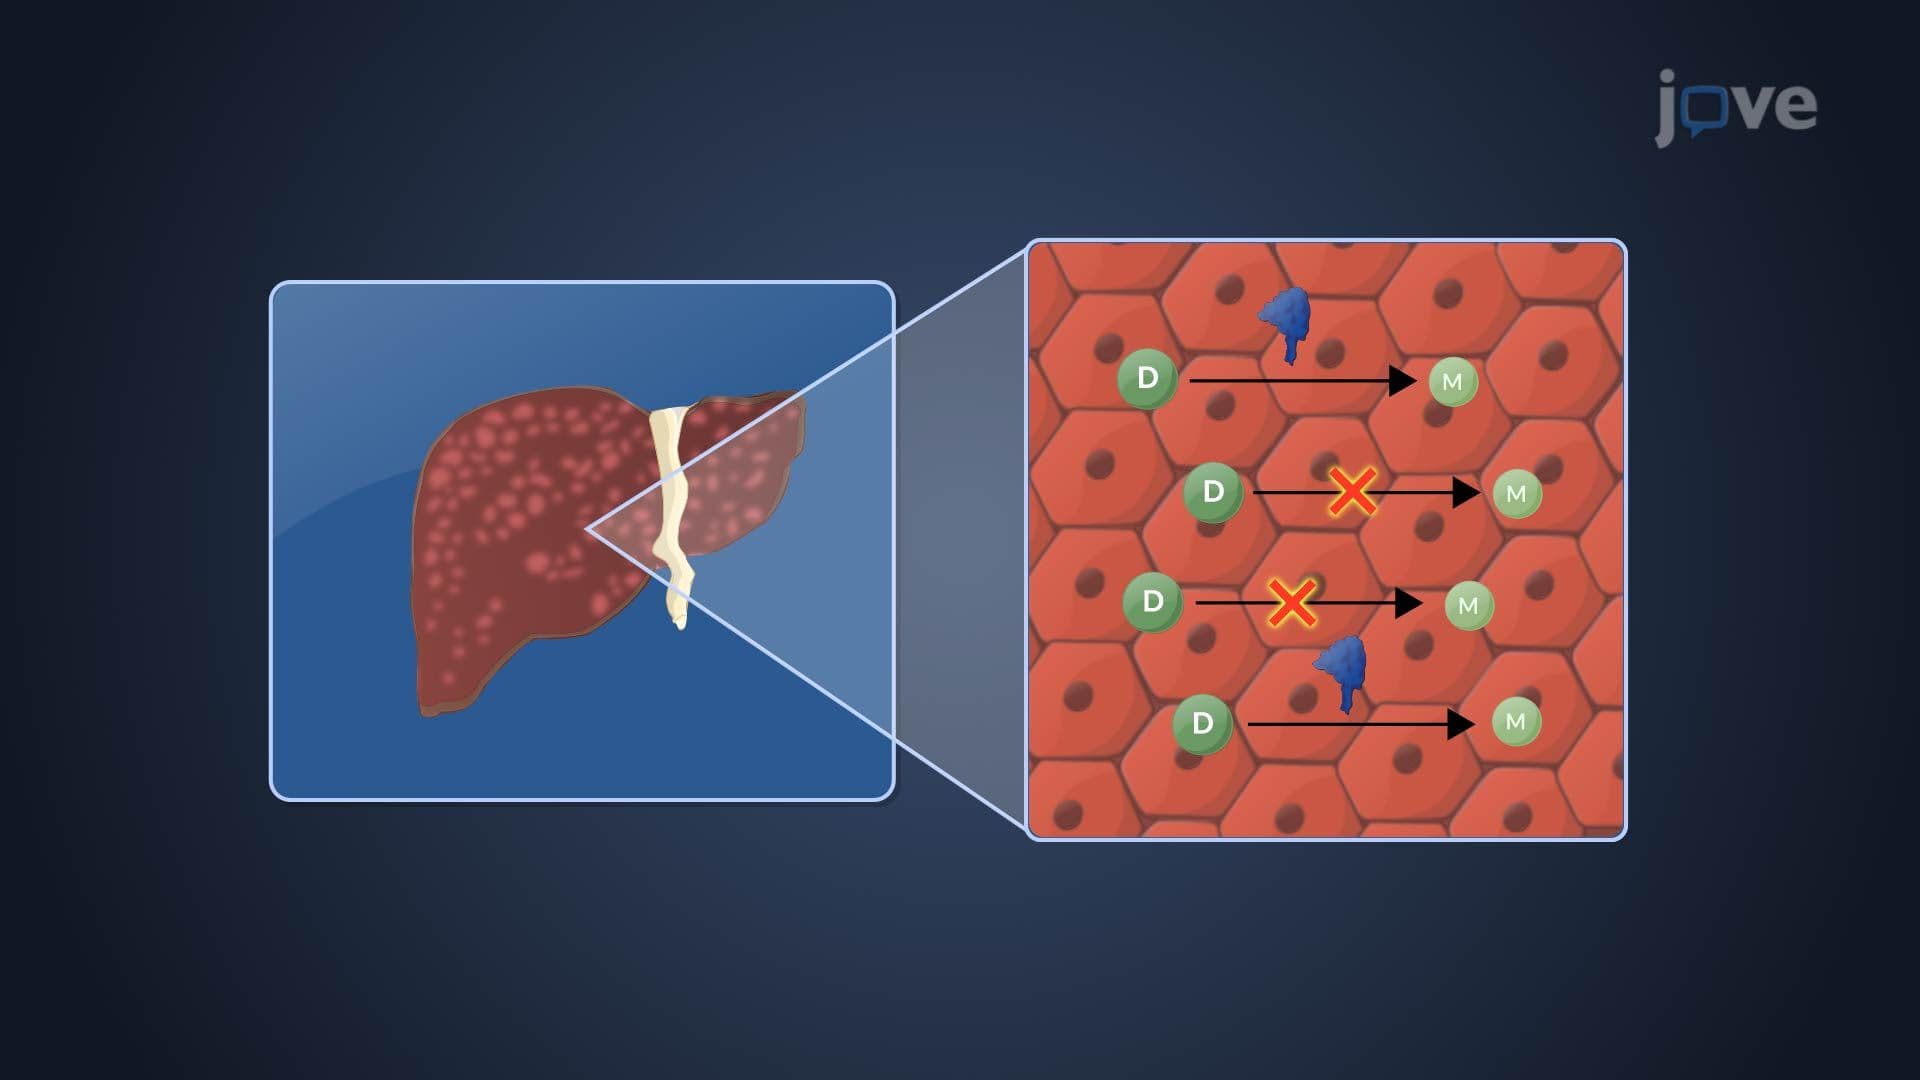
Effect of Hepatic Disease on Pharmacokinetics: Active Drug, Metabolite and Fraction of Metabolized Drug
 01:27
Acute Pancreatitis I: Introduction
Acute pancreatitis is characterized by rapid inflammation of the pancreas, often caused by factors like gallstone blockage or excessive alcohol consumption. Chronic pancreatitis, on the other hand, is a slow, progressive inflammation that may result from long-term alcohol abuse, obstructions in the pancreatic duct, or genetic factors.
The causes of acute pancreatitis include: