Related Experiment Video
Updated: Jul 30, 2026
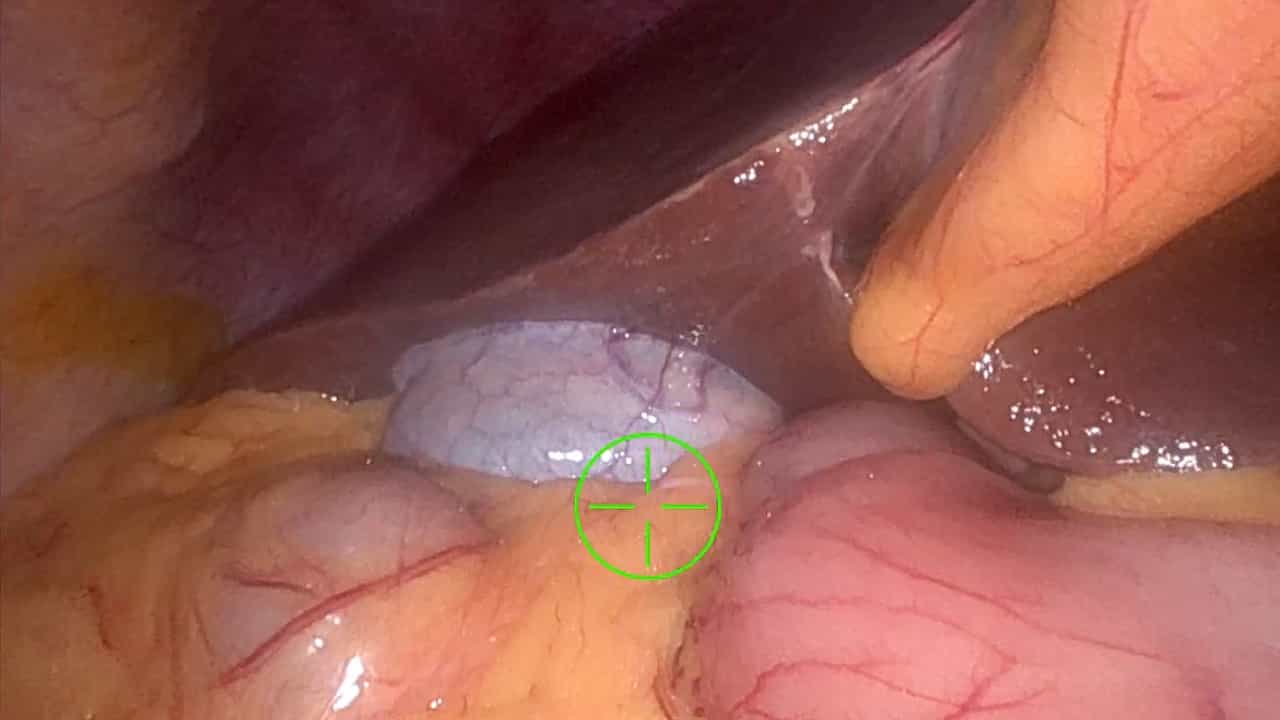
Application of Robot-assisted Pancreaticobiliary Junction Resection in Benign Duodenal Tumors
Published on: December 20, 2024
Intermittent treatment of duodenal ulcer for long term medical management
1District General Hospital, Rotherham, UK.

Abstract:
Most patients with duodenal ulcer relapse but in individuals the events is unpredictable and complications are rare. Two methods of long term treatment have been developed: daily maintenance treatment to prevent relapse; and intermittent treatment, in which individual symptomatic relapses are treated with a short healing course. Pooling the results of three studies on intermittent treatment where cimetidine was used, the number of relapses in one year and the proportion of patients who relapsed were: no relapse, 26%; 1 relapse, 33%; 2 relapses, 24%; greater than or equal to 3 relapses, 17%. Thus, 83% of patients on average have less than or equal to 2 attacks per year, which can be rapidly controlled with a short course of treatment. In comparative trials, relapse on maintenance treatment is much less than on intermittent treatment, as would be expected, but the clinical advantage of the former is relatively small and obtained at a much higher cost in drugs. However, in practice, the two treatments are complementary, not competitive, and patients in whom maintenance treatment (or surgery) is necessary would not be considered for intermittent treatment. Most work on intermittent treatment has been done with histamine H2 receptor antagonists. Theoretically, better results might be achieved by increasing the healing rate with omeprazole or more effectively, by reducing the spontaneous relapse rate by healing with colloidal bismuth. Intermittent treatment is contraindicated in the one-third who are either 'high-risk' patients or those who have aggressive ulcer disease. It is suitable for the two-thirds who meet all the following criteria: age <60 years; no associated serious illness; no previous haemorrhage or perforation; not on regular treatment with non-steroidal anti-inflammatory drugs; symptoms develop gradually (se that treatment can be started before pain worsens); less than or equal 2 relapses per year; ulcer is non-refractory. It is essential to establish an accurate diagnosis before starting therapy. Treatment is given for a month and repeated when typical symptoms recur. Repeat endoscopy is not needed except in special circumstances. For the majority of patients, intermittent treatment is an effective, simple and economical way of providing long term treatment.
Related Concept Videos
 01:16
Treating Helicobacter pylori in Peptic Ulcers: Antimicrobial Therapy
 01:26
Peptic Ulcer Disease IV: Management
The therapeutic approach involves ensuring adequate rest, implementing drug therapy, promoting smoking cessation, making dietary modifications, and emphasizing long-term follow-up care.
Pharmacological management
The prevailing therapy for peptic ulcers involves a combination of managing the patient's current medication...
 01:29
Chronic Pancreatitis II: Collaborative Care
Assessment:
 01:21
Inflammatory Bowel Disease V: Surgical Management
Here are some common surgical interventions for IBD:
 01:25
Peptic Ulcer Disease V: Surgical Management and Nursing Care
Surgical Interventions for Peptic Ulcer Disease
 01:25
Peptic Ulcer Disease III: Clinical Manifestations and Complications