Related Experiment Video
Updated: Feb 19, 2026
Assessment of Antibody-based Drugs Effects on Murine Bone Marrow and Peritoneal Macrophage Activation
Published on: December 26, 2017
Low rate of infectious complications following immunoadsorption therapy without regular substitution of intravenous
Sergey Tselmin1, Ulrich Julius1, Stefan R Bornstein1
1Extracorporeal Treatment and Lipoprotein Apheresis Center, Department of Internal Medicine III, University Hospital Carl Gustav Carus at the Technische Universität Dresden, Fetscherstr. 74, 01307 Dresden, Germany.

Introduction:
Immunoadsorption (IA) is increasingly used instead of plasma exchange due to lower risk of side effects and a higher selectivity. As a consequence of the reduction of immunoglobulins (Ig), the rate of infectious complications might increase in those patients. We therefore aimed to investigate the infection rate following IA without intravenous IG (IVIG) substitution in our apheresis center, where patients do not receive IVIG on a regular basis.
Material And Methods:
We conducted a retrospective analysis of the IA treatments performed between 2010 and 2015 without IVIG substitution and collected data on patient age, diagnosis, number of IA treatments, serum levels of Ig, total protein, albumin, C-reactive protein (CRP) and infectious complications that occurred within 2 months after the IA treatment cycle.
Results:
A total number of 52 patients (27 females) received at least 5 IA sessions using the following adsorbers: TheraSorb™-Ig (n = 3), TheraSorb™-Ig flex (n = 44), TheraSorb™ Ig pro (n = 1) and TheraSorb™-IgE (n = 5). The median number of treatment sessions was 8.8 [range 5-16], the median IgG reduction was 82 [11-99] %. Serum albumin was decreased by 8%. The median CRP levels remained normal until the end of therapy and within 2 months after that (3.10 and 4.30 mg/L respectively). Only 4 patients had infections (7.7%). Three of them received additional immunosuppressive therapy.
Conclusions:
Immunoadsorption leads to a significant reduction of IgG. CRP as inflammatory marker is not affected. Even without substitution of IVIG the complication rate directly linked with IA is low and questionable.
More Related Videos
 07:13
Digital Home-Monitoring of Patients after Kidney Transplantation: The MACCS Platform
Published on: April 12, 2021
 08:04
Development of an IFN-γ ELISpot Assay to Assess Varicella-Zoster Virus-specific Cell-mediated Immunity Following Umbilical Cord Blood Transplantation
Published on: July 9, 2014
Related Concept Videos
 01:25
Immunodeficiency Diseases
There are three main causes of immunodeficiency...
 01:24
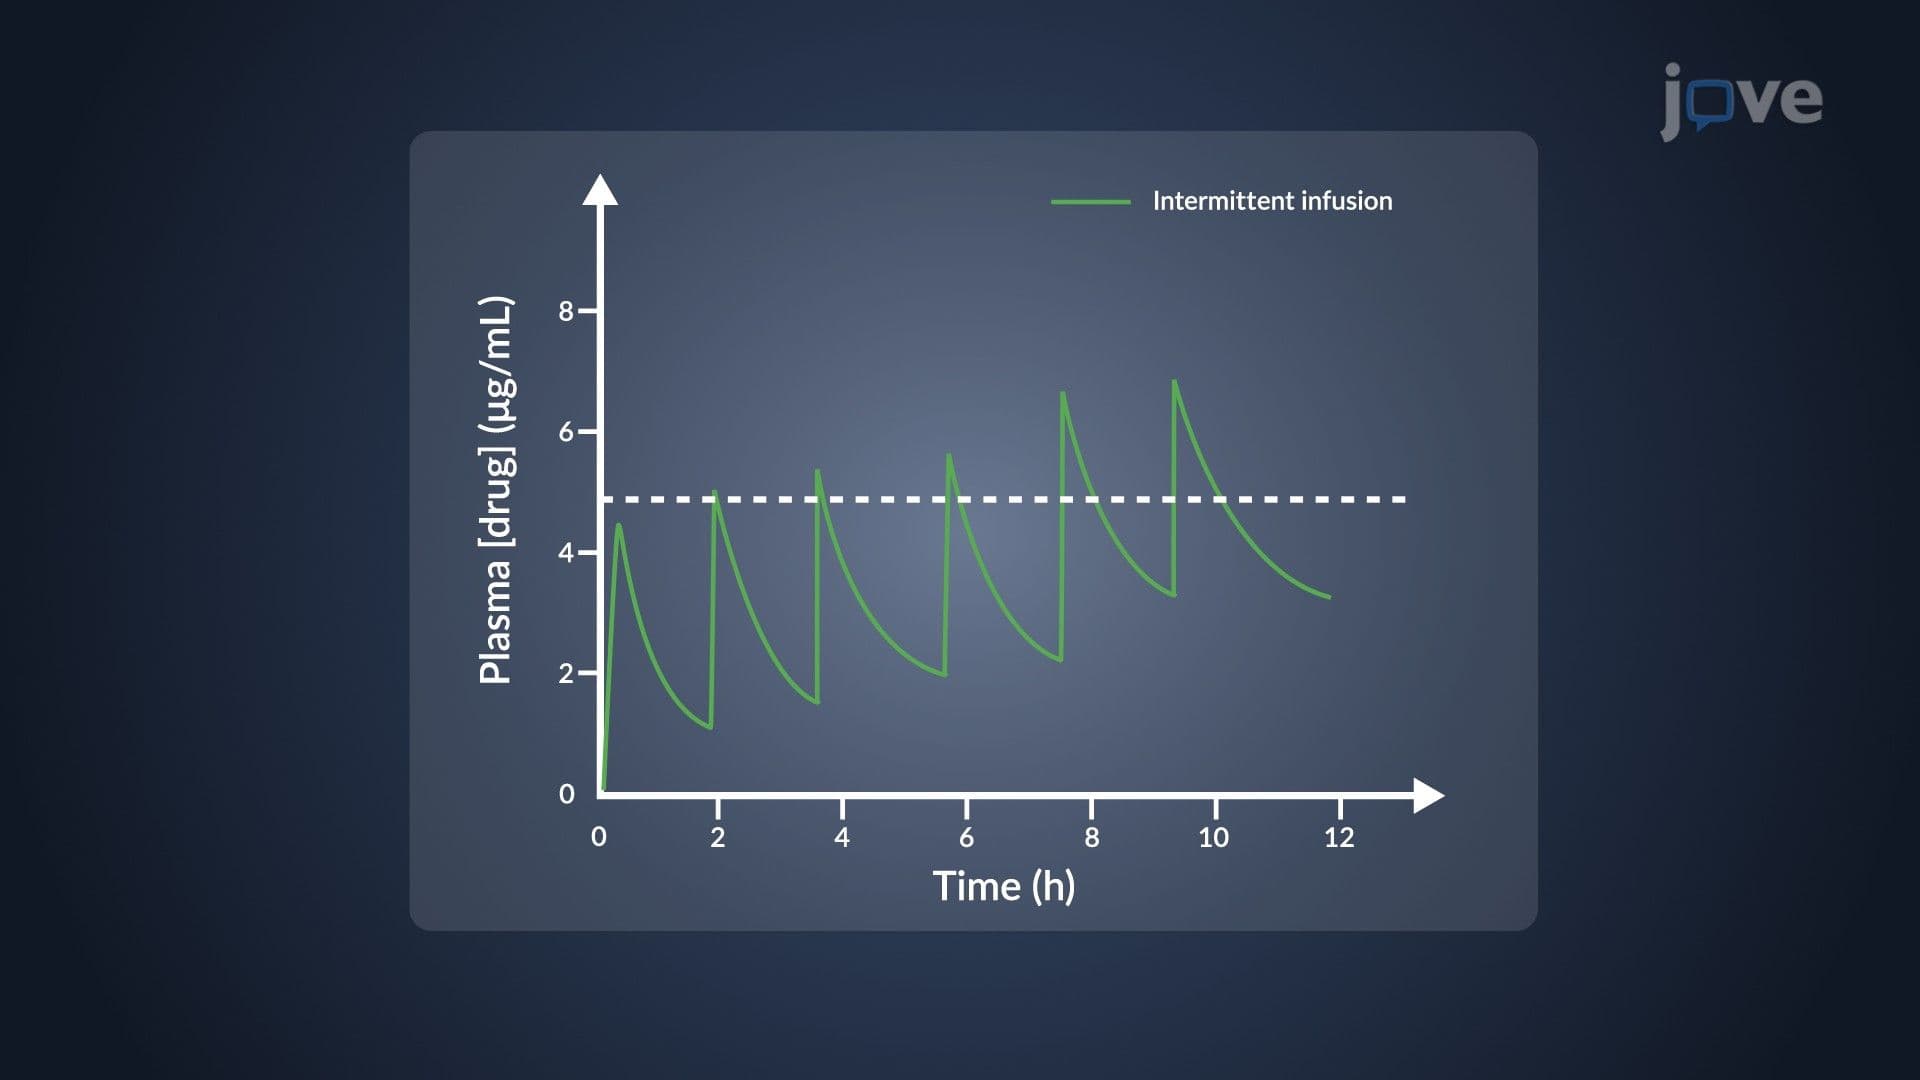
Drug Accumulation During Multiple Dosing: Intermittent IV Infusions
 01:36
Humoral Immune Responses
 01:29
Pulmonary Tuberculosis I
Causative Organism
The primary infectious agent causing tuberculosis is Mycobacterium tuberculosis, a slow-growing, acid-fast, aerobic rod that exhibits sensitivity to heat and ultraviolet light. Instances of Mycobacterium bovis and Mycobacterium avium contributing to the development of TB infection are rare.
Mode of...
 01:22
Development of Immunocompetence
The initial cells that migrate from the fetal thymus settle within the skin and epithelial tissues lining the mouth, digestive tract, and in females, the uterus and vagina. These cells, including skin-based dendritic cells, serve as antigen-presenting cells, playing a key role in T cell activation.
Subsequent T...
 01:30
Acute Kidney Injury IV: Diagnostic Studies and Prevention