Related Experiment Video
Updated: Feb 19, 2026
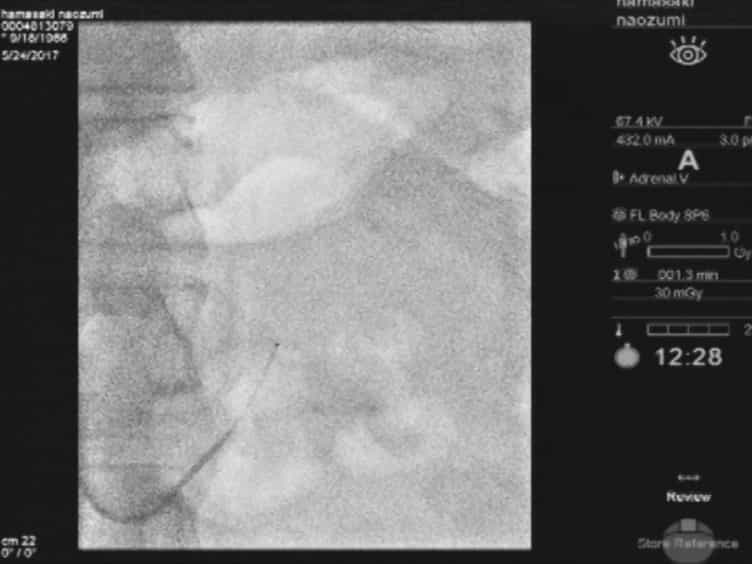
A Novel Method: Super-selective Adrenal Venous Sampling
Published on: September 15, 2017
Contralateral suppression of aldosterone at adrenal venous sampling predicts hyperkalemia following adrenalectomy for
Omair A Shariq1, Irina Bancos2, Patricia A Cronin2
1Department of Surgery, Mayo Clinic, Rochester, MN.

Background:
We aimed to determine whether a greater degree of contralateral suppression of aldosterone secretion at adrenal venous sampling predicted the development of postoperative hyperkalemia after unilateral adrenalectomy for primary aldosteronism.
Methods:
A retrospective analysis of patients undergoing unilateral adrenalectomy for primary aldosteronism between 2004-2015 was performed. Clinical and biochemical parameters of patients who developed hyperkalemia (≥5.2 mmol/L) after unilateral adreanlectomy were compared with those who remained normokalemic. The contralateral suppression index was defined as the aldosterone-to-cortisol ratio from the nondominant adrenal vein divided by the aldosterone-to-cortisol ratio from the external iliac vein.
Results:
Of 192 patients who met criteria for inclusion, 12 (6.3%) developed hyperkalemia (median serum potassium 5.5 mmol/L, range 5.2-6.2 mmol/L), with a median time to onset of 13.5 days (range 7-55 days). Five patients had transiently increased serum potassium concentrations that normalized spontaneously. Four patients received mineralocorticoid replacement therapy with fludrocortisone. On univariate analysis, hyperkalemic patients had slightly greater preoperative serum creatinine levels (1.2 vs 1.0 mg/dL, P = .01), higher postoperative creatinine (1.3 vs 1.0 mg/dL, P = .02), lesser median contralateral suppression index (0.14 vs 0.27, P = .03), and larger adenomas (1.9 vs 1.4 cm, P = .02). On multivariable logistic regression, the contralateral suppression index remained the only significant predictor of postoperative hyperkalemia (P = .04) with an optimal cut-off of <0.47.
Conclusion:
Hyperkalemia after unilateral adrenalectomy for primary aldosteronism is uncommon and usually transient, but may require mineralocorticoid supplementation. Patients with a contralateral suppression index of <0.47 require meticulous follow-up and monitoring of serum potassium concentrations after unilateral adrenalectomy.


Related Concept Videos
 01:27
Adrenal Gland Disorders
Adrenal insufficiency, characterized by insufficient cortisol and aldosterone production, leads to conditions like Addison's disease. This disorder, affecting the adrenal cortex, exhibits symptoms such as skin bronzing, dehydration, low blood pressure, fatigue, and weight loss. Congenital adrenal hyperplasia, a genetic ailment causing...
 01:28
Antihypertensive Drugs: Potassium-Sparing Diuretics
 01:26
Regulation of Sodium and Potassium
Sodium Regulation
Sodium ions make up approximately 90% of extracellular cations, with a normal blood plasma concentration of 136–148 mEq/L. A decrease in blood volume and pressure triggers the release of renin from granular cells in the juxtaglomerular complex (JGC), primarily...
 01:22
Adrenergic Antagonists: Pharmacological Actions of ɑ-Receptor Blockers
α1-blockers: These drugs inhibit α1-adrenoceptors on smooth muscle cells, resulting in vasodilation. This vasodilation lowers blood pressure, making α1-blockers valuable in treating hypertension. Additionally,...
 01:17
Anatomy of the Adrenal Glands
These glands possess a distinctive yellow tinge due to the stored cholesterol and fatty acids required for hormone synthesis. They are encased in a fibrous capsule and cushioned by fat.
The adrenal gland comprises two distinct...
 01:31
Hormones of the Adrenal Glands
The adrenal cortex, a powerhouse of hormone synthesis, generates over two dozen corticosteroid hormones. The zona glomerulosa produces mineralocorticoids, exemplified by aldosterone, influencing the electrolyte composition of body fluids. The synthesis of glucocorticoids such as cortisol and...