Related Experiment Video
Updated: Feb 17, 2026
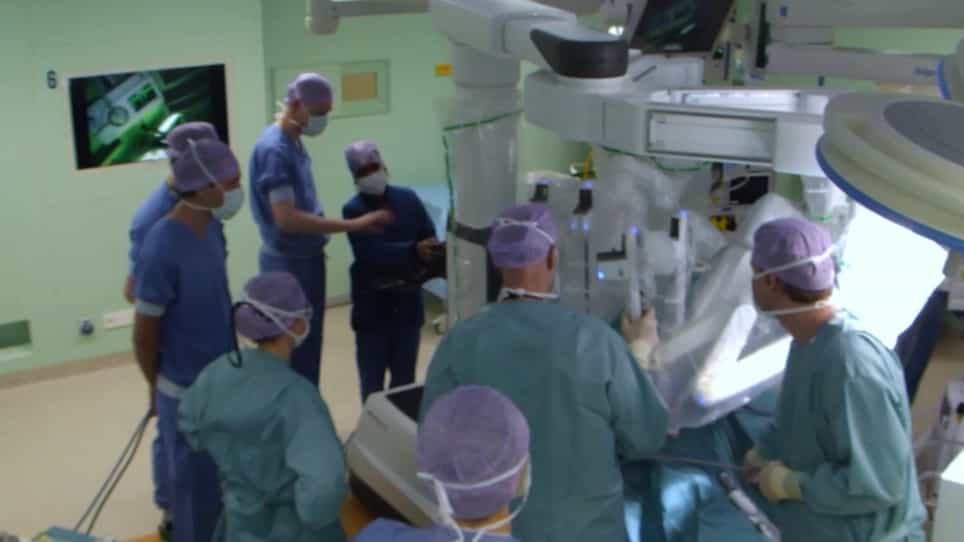

Robotic Enucleation of an Intra-Pancreatic Insulinoma in the Pancreatic Head
Published on: January 3, 2020
Multidisciplinary management of refractory insulinomas
Emily Brown1, Daniel Watkin1, Jonathan Evans2
1Obesity and Endocrinology Research Group, University Hospital Aintree, University of Liverpool, Liverpool, UK.

Abstract:
Insulinomas are predominantly benign (~90%), pancreatic neuroendocrine tumours characterized by hyperinsulinaemic hypoglycaemia. They usually present as a small (<2 cm), well-demarcated, solitary nodule that can arise in any part of the organ. Treatment for sporadic insulinomas is generally aimed at curative surgical resection with special consideration in genetic syndromes. Patients with significant hypoglycaemia can pose a difficult management challenge. In isolated cases where the patient is not medically fit for surgery or with metastatic spread, other treatment options are employed. Medical therapy with diazoxide or somatostatin analogues is commonly used first line for symptom control, albeit with variable efficacy. Other medical options are emerging, including newer targeted biological therapies, including everolimus (an mTOR inhibitor), sunitinib (a tyrosine kinase inhibitor) and pasireotide, a multisomatostatin receptor ligand. Pasireotide and everolimus both cause hyperglycaemia by physiological mechanisms synergistic with its antitumour/antiproliferative effects. Minimally invasive treatment modalities such as ethanol ablation are available in selected cases (particularly in patients unfit for surgery), peptide receptor radionuclide therapy (PRRT) can effectively control tumour growth or provide symptomatic benefit in metastatic disease, while cytotoxic chemotherapy can be used in patients with higher-grade tumours. This review considers the developments in the medical and other nonsurgical management options for cases refractory to standard medical management. Early referral to a dedicated neuroendocrine multidisciplinary team is critical considering the array of medical, oncological, interventional radiological and nuclear medical options. We discuss the evolving armamentarium for insulinomas when standard medical therapy fails.


Related Concept Videos
 01:15
Diabetes: Management and Pharmacotherapy
Insulin remains the cornerstone of treatment for most patients with type 1 and many...
 01:29
Chronic Pancreatitis II: Collaborative Care
Assessment:
 01:16
Insulin: Dosing Regimen and Adverse Effects
The basal dose constitutes about 40%-50% of the total daily dose, with the rest as premeal insulin. The mealtime insulin dose should mirror...
 01:30
Acute Pancreatitis II: Clinical Manifestations and Management
 01:22
Diabetes Mellitus: Overview and Type I Subtype
Type 1 diabetes is an autoimmune disease in which the immune system mistakenly attacks and destroys the insulin-producing beta cells in the pancreas. As a result, the body is unable to produce sufficient insulin, and individuals with...
 01:26
Peptic Ulcer Disease IV: Management
The therapeutic approach involves ensuring adequate rest, implementing drug therapy, promoting smoking cessation, making dietary modifications, and emphasizing long-term follow-up care.
Pharmacological management
The prevailing therapy for peptic ulcers involves a combination of managing the patient's current...