Related Experiment Video
Updated: Feb 16, 2026
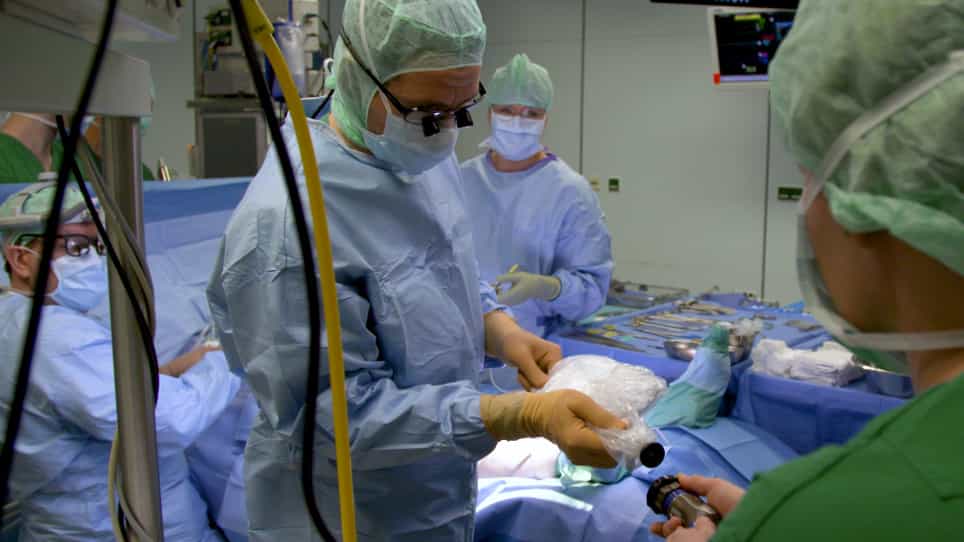
Synergizing Antegrade Endoscopic with Bridging Vein Harvesting for Improvement of Great Saphenous Vein Graft Quality from the Lower Leg
Published on: November 19, 2019
[Vein morphology after endovenous laser coagulation at different power and similar linear density of energy]
A A Fokin1, D A Borsuk2, E L Kazachkov3
1Department of Surgery of the South Ural State Medical University, Chelyabinsk, Russia.

Abstract:
The purpose of the study was to assess the depth of damage to the venous wall after endovenous laser coagulation (EVLC) at different power of the unit - 5, 7 and 10 W and similar linear density of energy (LDE) - approximately 70 J/cm. Our prospective comparative morphological study with blinding included a total of 30 patients subjected to EVLC of the great saphenous vein using the unit with a wavelength of 1,470 nm and radial light guides with automatic traction. The patients were divided into three groups, each comprising 10 patients. The unit's power (W) during EVLC and velocity of light guide traction (mm/s) in group one amounted to 5 and 0.7 (LDE - 71.4 J/cm), in group two to 7 and 1.0 (LDE - 70 J/cm) and in group tree to 10 and 1.5 (LDE - 66.7 J/cm), respectively. The coagulated veins were then procured from mini approaches and subjected to three sections made at a distance of 2 mm from each other. Specimens were stained with haematoxylin-eosin and picrofuxin according to the van Gieson technique. Then, in four places of each section (at 3, 6, 9 and 12 hours) we assessed the depth of the damage to the venous wall and calculated the average percentage of alteration - the ratio of the depth of the lesion to the venous wall thickness. The average depth of damage to the venous wall (μm) amounted in the first group to 122.9 ?m, in the second group to 182.9 μm, and in the third group to 267 μmm. The index of alteration (%) averagely amounted: in group one to 25.7, in group two to 37.9 and in group three (at a power of 10 W) to 55.5 (p=0.0001 when comparing each of the groups (the Kruskal-Wallis test)). Hence, despite an inconsiderable decrease of the LDE from the first to the third group, as power increased, the depth and percentage of damage to venous walls increased statistically significantly. It follows from the above-mentioned that: 1) an increase in power (from 5 to 10 W) of the unit during EVLC at comparable LDE (approximately 70 J/cm) leads to a deeper damage of the venous wall; 2) it is necessary to carry out a clinical study aimed at comparing different modes of coagulation, with the assessment of the frequency of recanalization and the level of pain syndrome.

Related Concept Videos
 01:26
Varicose Veins II: Diagnostic Studies and Interprofessional Care
 01:26
Varicose Veins I: Introduction
 01:15
Veins of Lower Limbs
Formed by the union of the medial and lateral plantar veins, the posterior tibial vein, rising through the calf muscle, assimilates the fibular vein. The anterior tibial vein, a superior extension of the foot's dorsalis pedis vein, merges with the posterior tibial vein at the...
 01:20
Venous Thrombosis II: Clinical Manifestations and Diagnostic Studies
 01:17
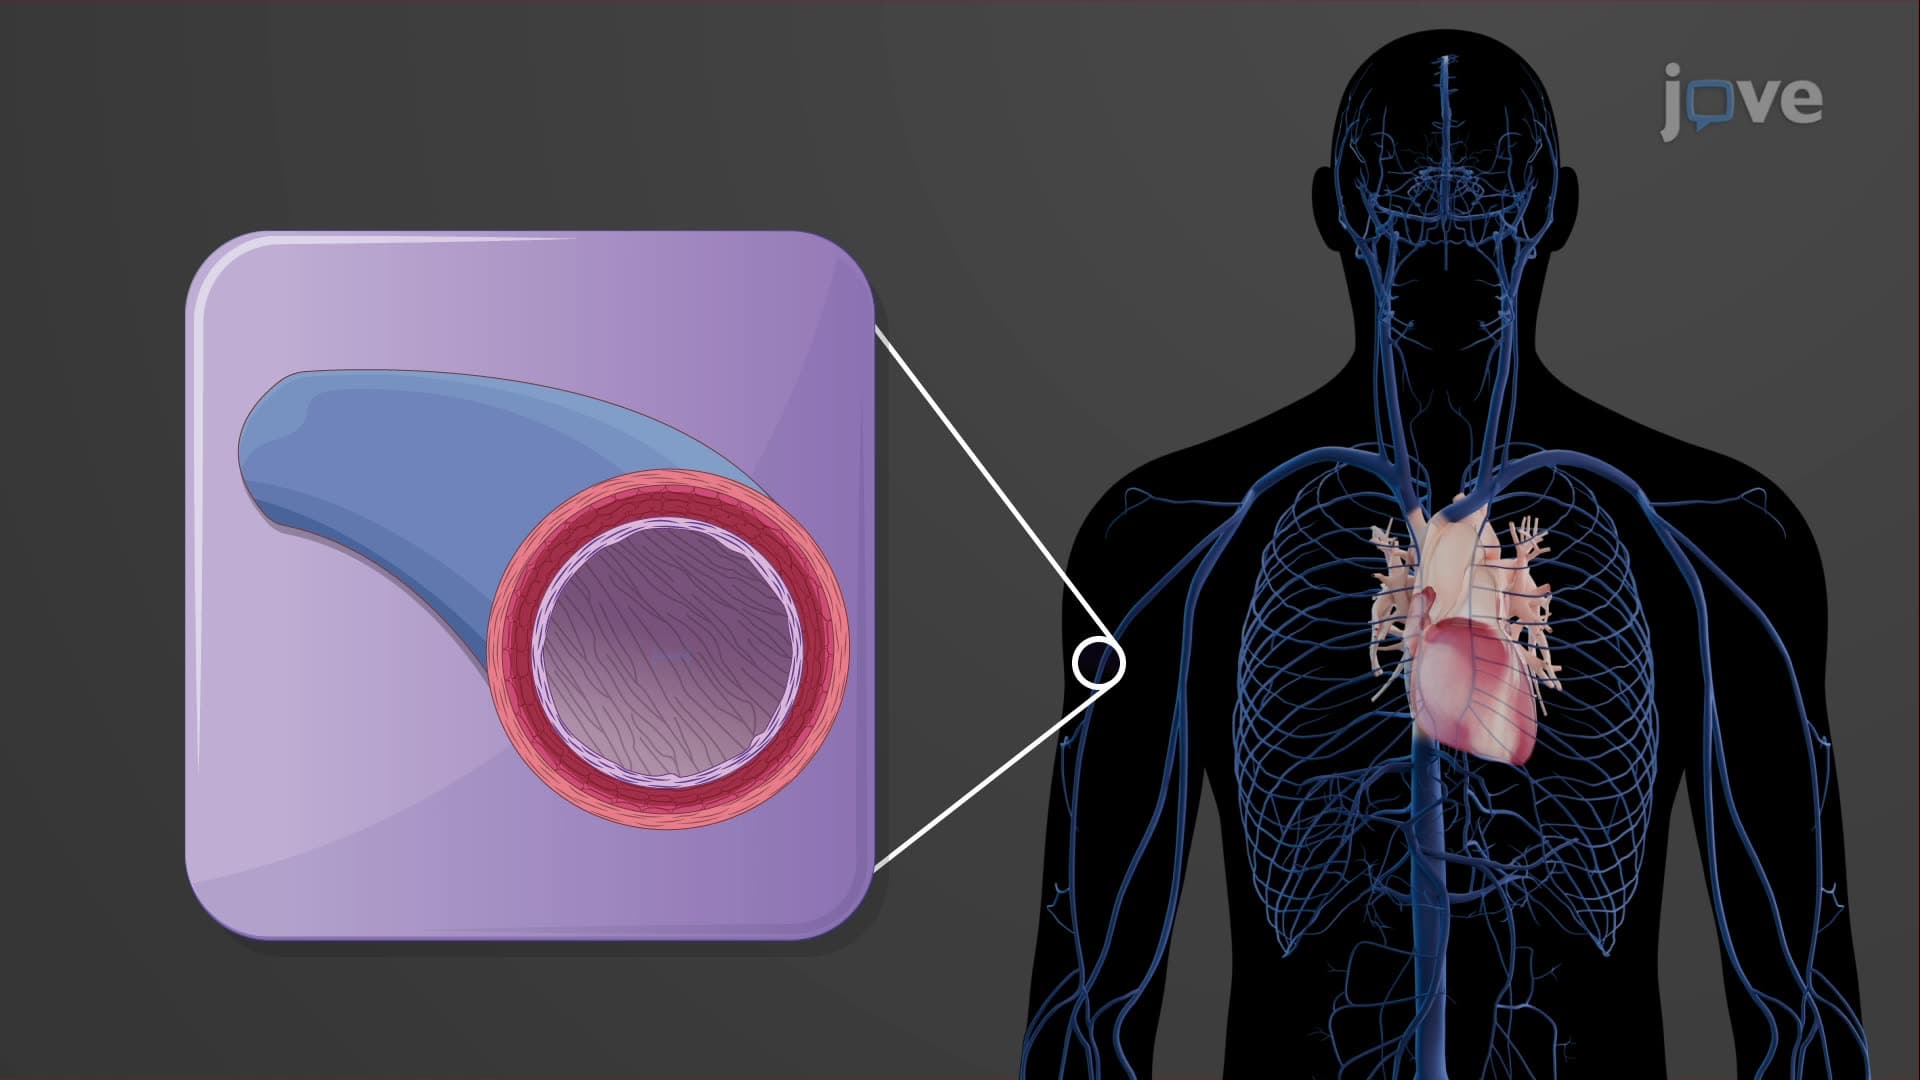
Veins
Structure of Veins:
The structure of veins is specifically designed to assist in the low-pressure transportation of...
 01:17
Veins of Upper Limbs
The deep venous system is primarily composed of the ulnar and radial veins. The ulnar vein, which drains the fingers through the superficial palmar venous arches, and the radial vein, which serves the palms via the deep palmar...