Related Experiment Video
Updated: Feb 16, 2026

Assessment of Perigenital Sensitivity and Prostatic Mast Cell Activation in a Mouse Model of Neonatal Maternal Separation
Published on: August 13, 2015
Progress towards achieving and maintaining maternal and neonatal tetanus elimination in the African region
Alison Delano Ridpath1, Heather Melissa Scobie1, Messeret Eshetu Shibeshi2
1Centers for Disease Control and Prevention, Global Immunization Division, Atlanta, GA, USA.

Despite the availability of effective tetanus prevention strategies, as of 2016, Maternal and Neonatal Tetanus Elimination (MNTE) has not yet been achieved in 18 countries globally. In this paper, we review the status of MNTE in the World Health Organization African Region (AFR),and provide recommendations for achieving and maintaining MNTE in AFR. As of November 2016, 37 (79%) AFR countries have achieved MNTE, with 10 (21%) countries remaining. DTP3 coverage increased from 52% in 2000 to 76% in 2015. In 2015, coverage with at least 2 doses of tetanus containing vaccine (TT2+) and proportion of newborns protected at birth (PAB) were 69% and 77%, compared with 44% and 62% in 2000, respectively. Since 1999, over 79 million women of reproductive age (WRA) have been vaccinated with TT2+ through supplementary immunization activities (SIAs). Despite the progress, only 54% of births were attended by skilled birth attendants (SBAs), 5 (11%) countries provided the 3 WHO-recommended booster doses to both sexes, and about 5.5 million WRA still need to be reached with SIAs. Coverage disparities still exist between countries that have achieved MNTE and those that have not. In 2015, coverage with DTP3 and PAB were higher in MNTE countries compared with those yet to achieve MNTE: 84% vs. 68% and 86% vs. 69%, respectively. Challenges to achieving MNTE in the remaining AFR countries include weak health systems, competing priorities, insufficient funding, insecurity, and sub-optimal neonatal tetanus (NT) surveillance. To achieve and maintain MNTE in AFR, increasing SBAs and tetanus vaccination coverage, integrating tetanus vaccination with other opportunities (e.g., polio and measles campaigns, mother and child health days), and providing appropriately spaced booster doses are needed. Strengthening NT surveillance and conducting serosurveys would ensure appropriate targeting of MNTE activities and high-quality information for validating the achievement and maintenance of elimination.
Despite the availability of effective tetanus prevention strategies, as of 2016, Maternal and Neonatal Tetanus Elimination (MNTE) has not yet been achieved in 18 countries globally. In this paper, we review the status of MNTE in the World Health Organization African Region (AFR),and provide recommendations for achieving and maintaining MNTE in AFR. As of November 2016, 37 (79%) AFR countries have achieved MNTE, with 10 (21%) countries remaining. DTP3 coverage increased from 52% in 2000 to 76% in 2015. In 2015, coverage with at least 2 doses of tetanus containing vaccine (TT2+) and proportion of newborns protected at birth (PAB) were 69% and 77%, compared with 44% and 62% in 2000, respectively. Since 1999, over 79 million women of reproductive age (WRA) have been vaccinated with TT2+ through supplementary immunization activities (SIAs). Despite the progress, only 54% of births were attended by skilled birth attendants (SBAs), 5 (11%) countries provided the 3 WHO-recommended booster doses to both sexes, and about 5.5 million WRA still need to be reached with SIAs. Coverage disparities still exist between countries that have achieved MNTE and those that have not. In 2015, coverage with DTP3 and PAB were higher in MNTE countries compared with those yet to achieve MNTE: 84% vs. 68% and 86% vs. 69%, respectively. Challenges to achieving MNTE in the remaining AFR countries include weak health systems, competing priorities, insufficient funding, insecurity, and sub-optimal neonatal tetanus (NT) surveillance. To achieve and maintain MNTE in AFR, increasing SBAs and tetanus vaccination coverage, integrating tetanus vaccination with other opportunities (e.g., polio and measles campaigns, mother and child health days), and providing appropriately spaced booster doses are needed. Strengthening NT surveillance and conducting serosurveys would ensure appropriate targeting of MNTE activities and high-quality information for validating the achievement and maintenance of elimination.

Related Concept Videos
 02:40
The Eukaryotic Promoter Region
 01:03
IR Frequency Region: Fingerprint Region
 01:19
Design Example: Maintaining Level of an Embankment
 01:05
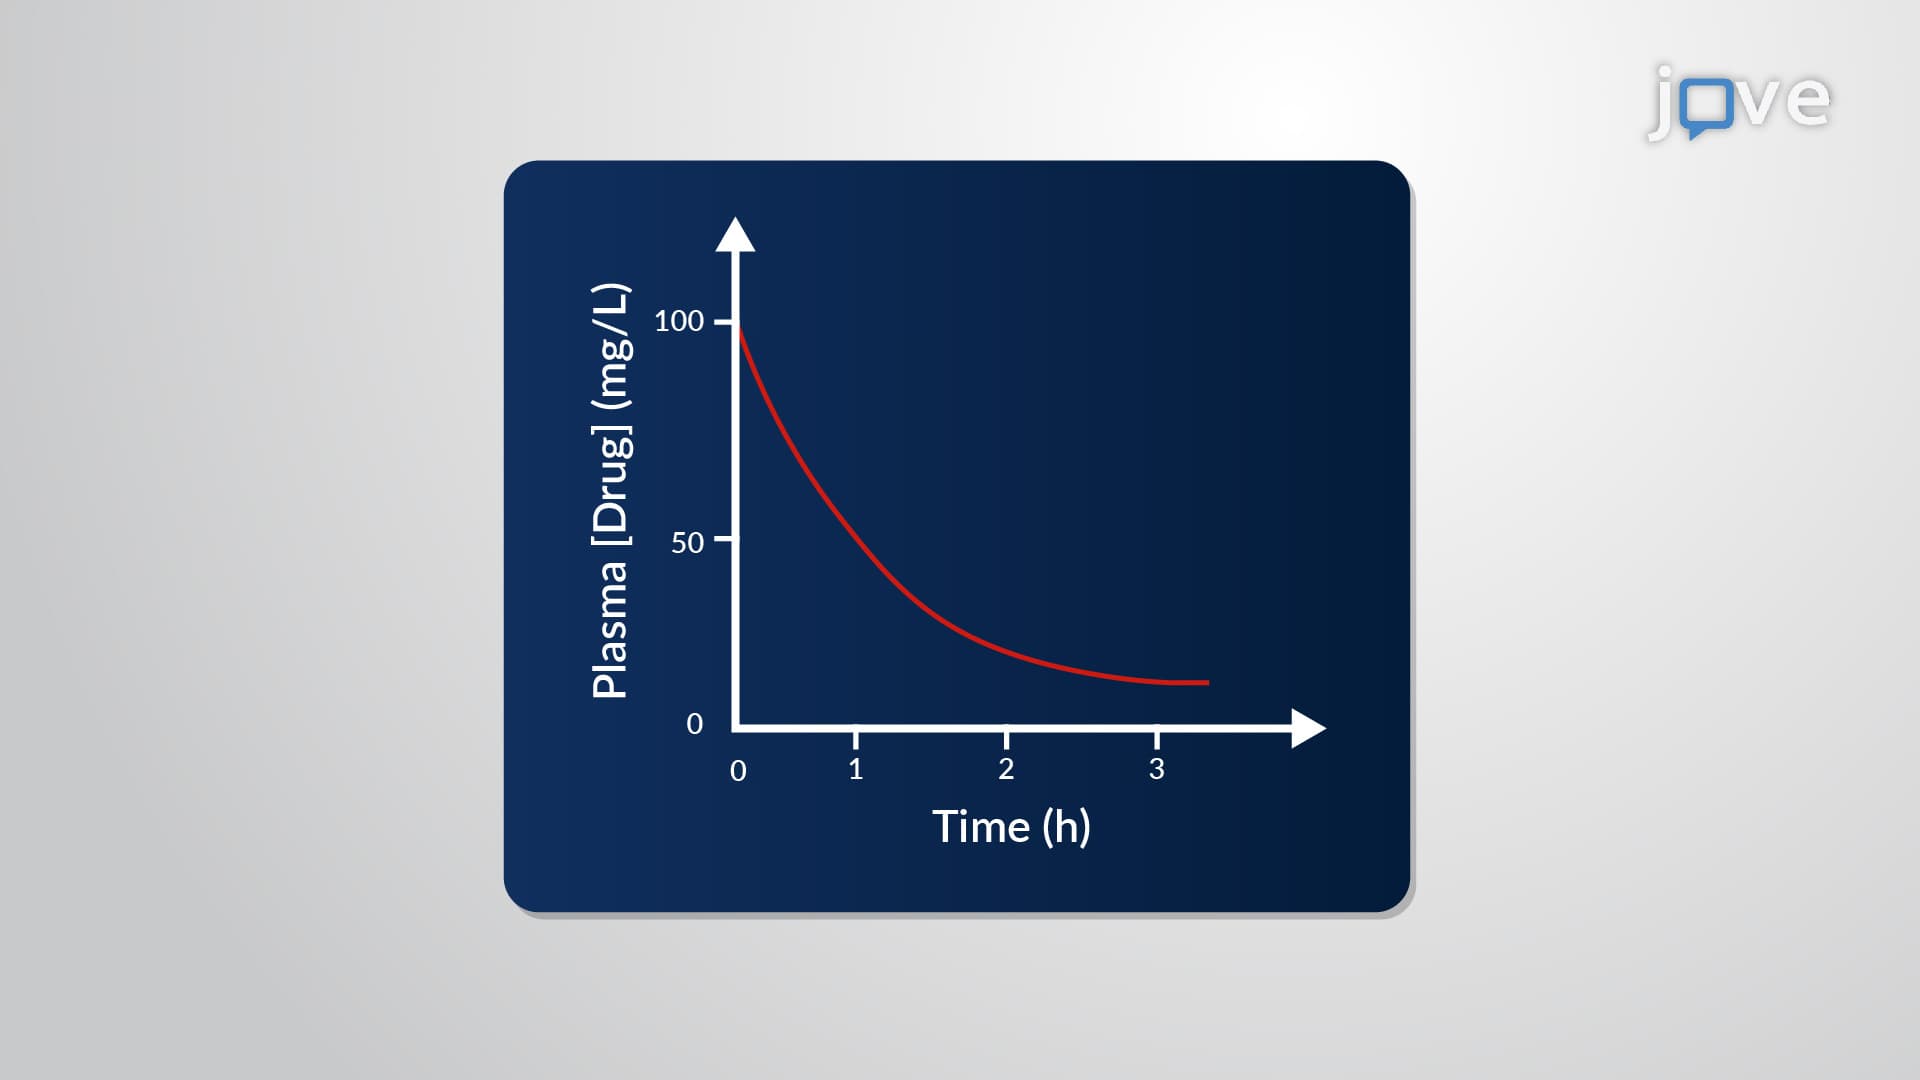
Elimination Kinetics: First-Order and Zero-Order
Drug clearance depends on the rate of drug elimination and its plasma concentration. Another important parameter is a drug's half-life, which is the time required for its concentration to decrease by half. In most cases, drug clearance follows first-order...
 02:25
Elimination Reactions
 02:07
Tumor Progression
Colon cancer is one of the best-documented examples of tumor progression. Early mutation in the APC gene in colon cells causes a small growth on the colon wall called a polyp. With time, this polyp grows into a benign, pre-cancerous tumor. Further...