Related Experiment Video
Updated: Feb 16, 2026


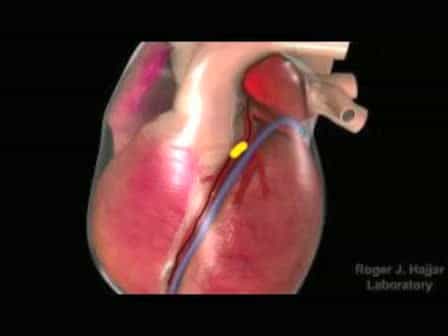
A New Single Chamber Implantable Defibrillator with Atrial Sensing: A Practical Demonstration of Sensing and Ease of Implantation
Published on: February 28, 2012
Long-Term Survival With Implantable Cardioverter-Defibrillator in Different Symptomatic Functional Classes of Heart
Yitschak Biton1, Spencer Rosero2, Arthur Moss2
1Division of Cardiology, Heart Research Follow-Up Program, Department of Medicine, University of Rochester Medical Center, Rochester, New York; Heart Institute, Sheba Medical Center, Ramat Gan, and Sackler School of Medicine, Tel Aviv University, Tel Aviv, Israel.

Insights
Primary implantable cardioverter-defibrillator (ICD) therapy offers significant long-term survival benefits for patients with reduced ejection fraction after myocardial infarction. This benefit persists regardless of heart failure symptoms, supporting broader ICD use in this population.
Area of Science:
- Cardiology
- Medical Devices
- Clinical Practice Guidelines
Background:
- Current guidelines differ on primary prevention implantable cardioverter-defibrillator (ICD) use for patients with severely reduced left ventricular ejection fraction (LVEF ≤30%).
- American guidelines recommend ICD for LVEF ≤30% irrespective of heart failure (HF) symptoms.
- European guidelines restrict ICD indication to symptomatic HF (NYHA class ≥II).
Purpose of the Study:
- To evaluate the long-term survival advantage of primary ICD therapy in post-myocardial infarction patients with LVEF ≤30%.
- To compare ICD effectiveness across different New York Heart Association (NYHA) functional classes (I, II, III) in the MADIT-II trial.
- To determine if HF symptoms influence the mortality benefit of ICD therapy.
Main Methods:
- Analysis of 1,164 patients from the Multicenter Automatic Defibrillator Implantation Trial II (MADIT-II) with LVEF ≤30%.
- Patients were stratified by baseline NYHA class (I, II, III).
- Multivariate Cox proportional hazards regression analyzed 8-year mortality risk reduction with ICD vs. non-ICD therapy.
Main Results:
- At 8 years, cumulative mortality in the non-ICD arm was 57% for NYHA I, 57% for NYHA II, and 76% for NYHA III.
- ICD therapy demonstrated a consistent, significant mortality risk reduction across all evaluated NYHA classes (NYHA I: HR 0.63; NYHA II: HR 0.68; NYHA III: HR 0.68).
- No significant interaction was found between NYHA class and treatment arm, indicating similar ICD benefit regardless of HF symptom severity.
Conclusions:
- Primary ICD therapy provides a consistent long-term survival benefit for patients with previous myocardial infarction and severe left ventricular dysfunction.
- The mortality benefit of ICDs in this population is independent of the presence or severity of heart failure symptoms.
- Findings support the American guideline recommendation for primary ICD use in patients with LVEF ≤30% regardless of HF symptoms.
Abstract:
The ACC/AHA/HRS (American College of Cardiology/American Heart Association Task Force on Clinical Practice Guidelines and the Heart Rhythm Society) guidelines recommend implantable cardioverter-defibrillator (ICD) therapy primary prevention in all patients with severely reduced left ventricular ejection fraction (≤30%) regardless of New York Heart Association (NYHA) functional class, whereas recent European guidelines limit the indication to those with symptomatic heart failure (NYHA ≥ II). We therefore aimed to evaluate the long-term survival benefit of primary ICD therapy among postmyocardial infarction patients with and without heart failure (HF) symptoms who were enrolled in MADIT-II (Multicenter Automatic Defibrillator Implantation Trial II). We classified 1,164 MADIT-II patient groups according to the baseline NYHA class (NYHA I [n = 442], NYHA II [n = 425], and NYHA III [n = 297]); patients with NYHA IV were excluded. Multivariate Cox proportional hazards regression modeling was performed to compare the mortality reduction with ICD versus non-ICD therapy during 8 years of follow-up between the 3 NYHA groups. The median (interquartile range) follow-up time was 7.6 (3.5 to 9) years. At 8 years of follow-up, the cumulative probability of mortality in the non-ICD treatment arm was 57% for NYHA I, 57% for NYHA II, and 76% for NYHA III (p <0.001). Multivariate models demonstrated similar long-term mortality risk reduction with ICD compared with the non-ICD treatment arm regardless of HF symptoms: NYHA I (HR = 0.63, 0.46 to 0.85, p = 0.003), NYHA II (HR = 0.68, 0.50 to 0.93, p = 0.017), and NYHA III (HR = 0.68, 0.50 to 0.94, p = 0.018); p for NYHA class by treatment arm interaction >0.10. In conclusion, primary ICD therapy provides consistent long-term survival benefit among patients with previous myocardial infarction and severe left ventricular dysfunction, regardless of HF symptoms.

Related Concept Videos
 01:29
Heart Failure II: Pathophysiology
 01:17
Pathophysiology of Heart Failure
 01:27
Heart Failure I: Introduction
 01:22
Heart Failure VI: Adjunct Therapies
 01:22
Heart Failure Drugs: Diuretics
 01:30
Heart Failure V: Medical Management