Related Experiment Video
Updated: Feb 15, 2026


Preparation and Evaluation of 99mTc-labeled Tridentate Chelates for Pre-targeting Using Bioorthogonal Chemistry
Published on: February 4, 2017
Technetium-99m-dimercaptosuccinic acid renal scintigraphy can guide clinical management in congenital hydronephrosis
Biljana Bazić-Đorović1, Marija Radulović, Marija Šišić
1Institute of Nuclear Medicine, Military Medical Academy, Faculty of Medicine of the Military Medical Academy, University of Defense, 11000 Belgrade, Serbia. ajdinovicboris@gmail.com.

Objective:
The purpose of this study was to evaluate damage of the kidney with technetium-99m-dimercaptosuccinic acid (99mTc-DMSA) scintigraphy in children with congenital hydronephrosis (CH) and the influence of other postnatal associated diagnoses on abnormal 99mTc-DMSA findings.
Subjects And Methods:
99mTc-DMSA scintigraphy in 54 children (17 girls and 37 boys), aged from 2 months to 5 years (median 11 months) with 66 congenital hydronephrotic renal units (RU) (42 unilateral hydronephrosis-29 boys and 13 girls; 12 bilateral hydronephrosis-8 boys and 4 girls) was performed. Male/female ratio was 2,2:1, unilateral/bilateral hydronephrosis ratio was 4:1. Hydronephrosis classified into three groups according to ultrasound measurement of the antero-posterior pelvic diameter APD): mild (APD 5-9.9mm) was present in 13/66RU, moderate (APD 10-14.9mm) in 25/66RU, and severe (APD≥15mm) in 28/66RU. Simple hydronephrosis was present in 15RU, and the postnatal associated clinical diagnosis were vesicoureteric reflux (VUR) in 21, pelviureteric junction (PUJ) obstruction in 7, pyelon et ureter duplex in 11, megaureter in 11 and posterior urethra valves in 1RU, respectively. Static renal scintigraphy was performed 2 to 3 hours after intravenous (iv) injection of 99mTc-DMSA using a dose of 50μCi/kg (1.85MBq/kg; minimal dose: 300μCi). Four views (posterior, left and right posterior oblique and anterior) were obtained with a head gamma camera "Orbiter" filtered with high resolution parallel whole collimator. All images were stored in an Pegasys computer with a matrix size of 256×256. The relative kidney uptake (RKU) between the left and right kidney was calculated as an average number counts from anterior and posterior view. Renal pathology was defined as inhomogenous or focal/multifocal uptake defects of radiopharmaceutical in hydronephrotic kidney or as split renal uptake of <40%, and poor kidney function was defined as split renal uptake <10%. Descriptive and analytical statistics (SPSS version 20.0) was performed. Analytical statistics implied the non-parametric Mann-Whitney test for determination of statistically significant difference between the normal and pathological findings on 99mTc-DMS scan. The default level of significance was P<.05.
Results:
Our 99mTc-DMSA scintigraphy findings in children with ANH were: decreased or enlarged kidney with inhomogeneous kidney uptake radiopharmaceutical in 22, irregular shape kidney with inhomogeneous accumulation of radiopharmaceutical in 3, connected (fused) kidney in 1 patient, and poorly or nonvisual kidney in 14RU respectively (total 40/66RU with pathological 99mTc-DMSA finding, 60,6%). Relative accumulation in hydronephrotic kidney was less or equal to 40% in 17RU, less than 10% in 14RU and inhomogeneous radiopharmaceutical uptake with relative accumulation over 40% was detected in 9RU. Regular kidney morphology with homogeneous accumulation of radiopharmaceutical (normal DMSA scintigraphy finding) were found in 26/66RU (39,4%). Statistically significant correlation between the degree of the hydronephrosis (APD) and 99mTc-DMSA scan findings (P<0.001) and between the degree of the VUR and DMSA scan finding (P=0.002) was established. In our study, other associated diagnosis were not statistically correlated with pathological findings on 99mTc-DMSA scan due to low number of patients.
Conclusion:
On the basis of these results (60% pathological findings) we recommend DMSA scintigraphy in the evaluation renal pathology in children with congenital hydronephrosis. Greater number of patients is needed for the estimation of the associated diagnosis (other than VUR) influence on the renal parenchymal damage in children with CH.


Related Concept Videos
 01:28
Esophageal Perforation-II: Clinical Manifestations and Management
Clinical Manifestations:
 01:21
Barrett Esophagus-II: Clinical Manifestations and Management
To diagnose Barrett's esophagus, healthcare providers often recommend an endoscopy for those showing symptoms of acid reflux. The procedure...
 01:28
Esophageal Varices-II: Clinical Features and Management
In the initial assessment, a thorough review of the patient's medical history is vital to identify risk factors such as liver disease, alcohol...
 01:23
Gastritis III: Clinical Manifestations and Management
Clinical manifestations of acute gastritis
The patient with acute gastritis may have a rapid onset of symptoms, such as epigastric pain or discomfort, dyspepsia, anorexia, hiccups, or nausea and vomiting, which can last from a few hours to a few days. Erosive or hemorrhagic gastritis may cause bleeding, which may manifest as blood in vomit or as...
 01:29
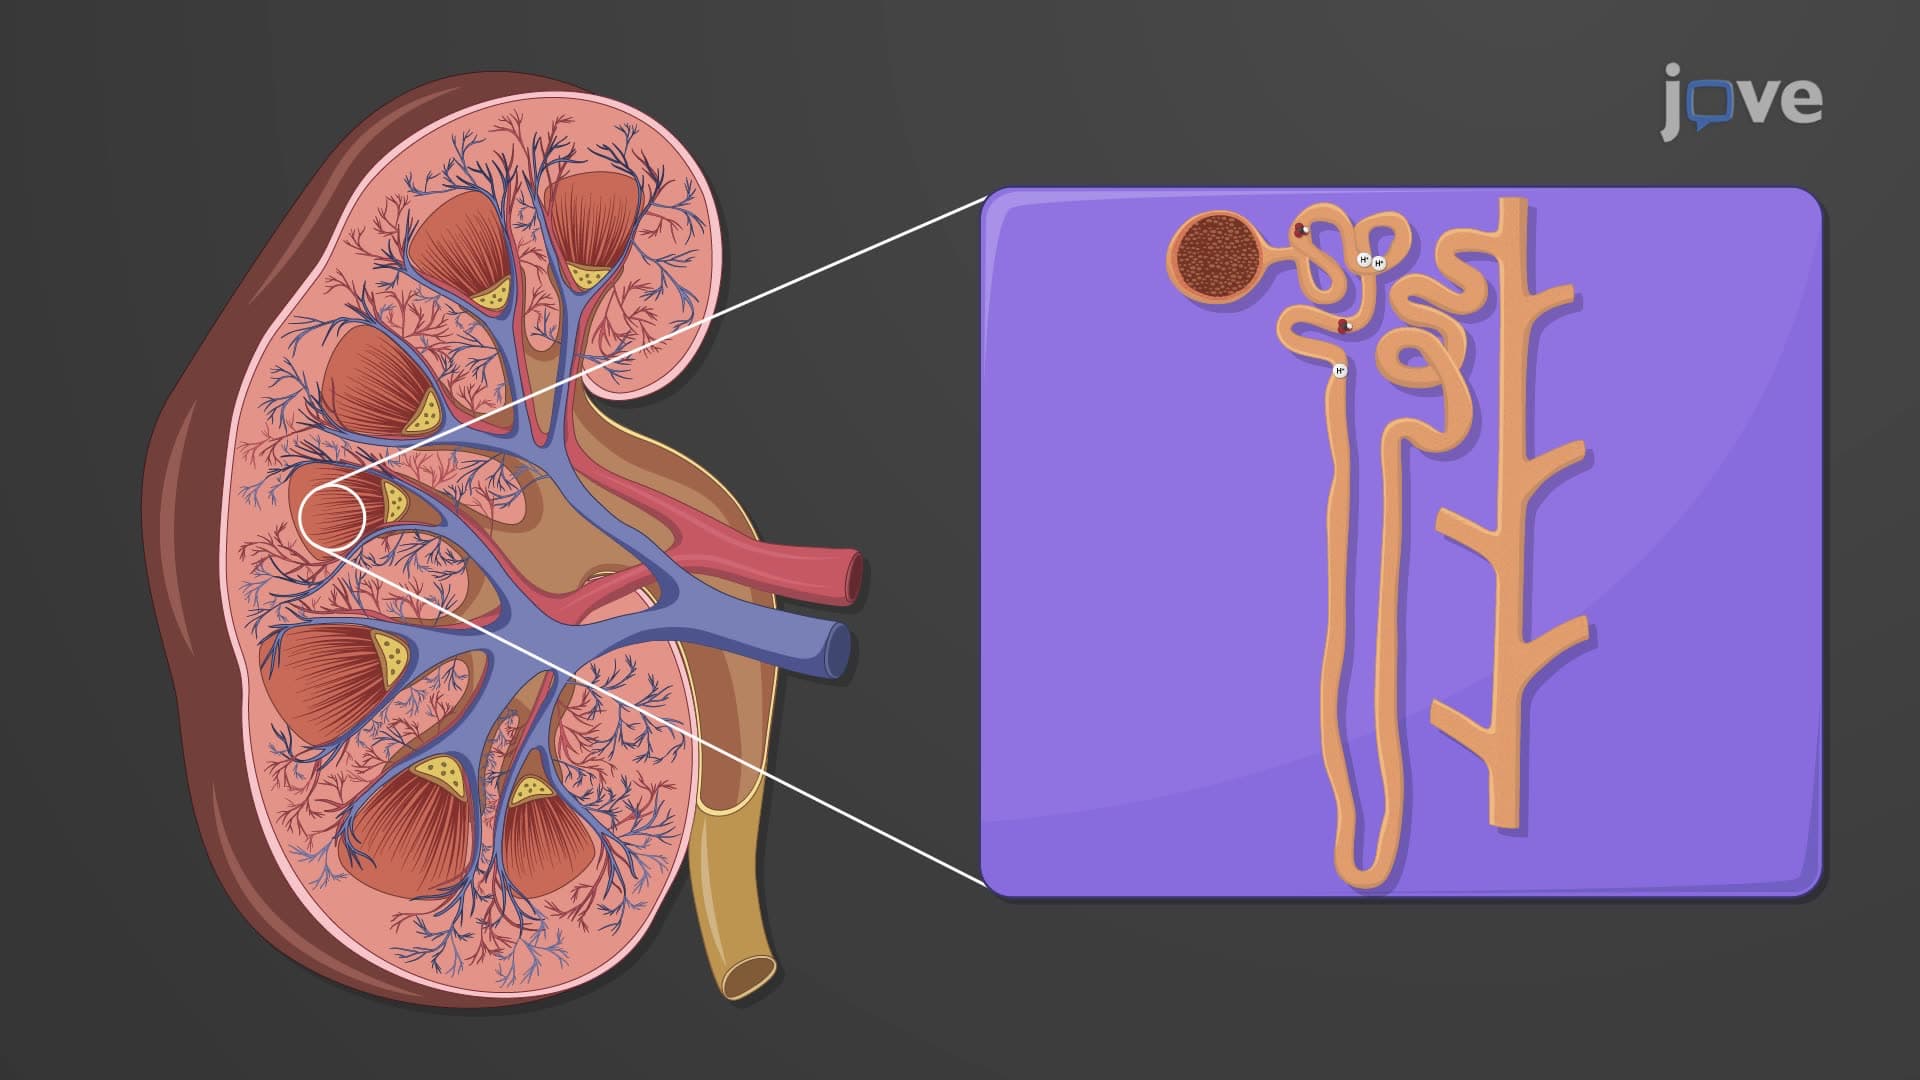
Renal Regulation of Acid-Base Balance
In the kidneys, cells within the proximal convoluted tubules (PCT) and the collecting ducts secrete hydrogen ions (H+) into the tubular fluid. Specifically, in the PCT, Na+/H+ antiporters secrete H+ while reabsorbing Na+.
However, the intercalated cells in...
 01:26
Esophageal Strictures-II: Clinical Features and Management
Healthcare providers should gather a comprehensive medical history and conduct a physical examination for diagnosis. If esophageal stricture is...